Developing Authenticity Through Values-Guided Behavioural Experiments

Daniel Mireaย (16 September, 2026)
|ย The NeuroAffective-CBTยฎ Journal |ย 

Companion article: This article develops the clinical illustration and conceptual pathway introduced in Beyond โ€˜Fake It Till You Make Itโ€™: The Pendulum-Effect, Embodied Rehearsal and the Development of the Integrated-Self. Whereas the earlier article examined how embodied rehearsal can make an inhibited response increasingly available, the present article explores how values-guided behavioural experiments may support the development of preferences, boundaries, authorship and authentic living.


Abstract

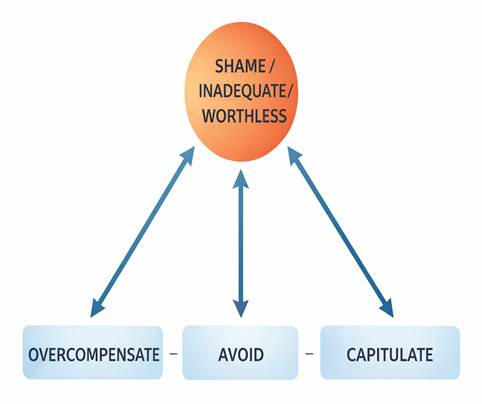
Authenticity is sometimes understood as the expression of a stable inner identity that must be discovered before it can be lived. Conversely, behavioural change may be presented as โ€œacting as ifโ€: imitating confidence or concealing distress until a preferred identity becomes convincing. Both positions are incomplete. The first risks treating familiar protective responses as evidence of an essential self; the second risks encouraging performance, masking and emotional invalidation. This conceptual article proposes that authenticity can be both discovered and developed through values-guided behavioural experiments. It argues that shame-organised protective responses are repeatedly enacted through attention, posture, voice, affect, behaviour and relationship. Within the NeuroAffective-CBTยฎ (NA-CBT) Pendulum-Effect Formulation, overcompensation, avoidance and capitulation are understood as interconnected protective positions organised around a shared affective threat. In the form examined here, that threat is internalised shame. Repeated enactment can make a restricted protective repertoire feel natural, personal and true.

Building upon an earlier NA-CBT account of embodied rehearsal and the development of the Integrated-Self, the present article examines the implications of this process for authenticity. It draws upon Stanislavskiโ€™s pursuit of truthful action under imagined circumstances, Vygotskyโ€™s socially situated account of the actorโ€™s emotion, Morenoโ€™s use of role and enactment in psychodrama, contextual accounts of values, and contemporary research on mental imagery. It describes how the therapeutic relationship and everyday life can become contexts in which clients recognise Pendulum movements and test alternatives to proving, hiding or surrendering. Through imagery, embodied rehearsal, graded action, reflection, recovery and repetition, unfamiliar responses may become increasingly available within the Integrated-Self. Repeated values-guided experiments may do more than make an inhibited response behaviourally available: they may help clients differentiate values, discover preferences and boundaries, and recognise authorship of unfamiliar but genuinely chosen actions. Authenticity is therefore conceptualised neither as an unchanging essence waiting to be uncovered nor as a persona installed through performance. It develops through an iterative relationship among felt experience, values, chosen action, relational feedback and autobiographical meaning.

Keywords: authenticity; values; behavioural experiments; embodied rehearsal; mental imagery; shame; Pendulum-Effect Formulation; Integrated-Self; NeuroAffective-CBTยฎ

Introduction: Can Authenticity Develop Through Action?

โ€œAnnaโ€ is a fictionalised composite constructed from several clinically similar cases. Identifying details, circumstances and sequences of events have been altered and combined to protect confidentiality. She had long experienced anxiety in social and interpersonal situations, although her difficulties did not fully meet the diagnostic criteria for social anxiety disorder.

When Anna entered therapy, she said that she wanted to become more confident. What she meant was that she wanted anxiety to disappear before she acted. She imagined that confident people spoke because they felt certain, while she remained silent because something essential was missing within her.

Her first behavioural experiment was deliberately modest. She was not asked to dominate a meeting, deliver a flawless presentation or behave as though she felt no anxiety. She prepared one genuine question and agreed to raise it within the first ten minutes.

When Anna imagined herself speaking, her shoulders lifted, her jaw tightened and she felt an urge to delay. She oriented towards the imagined room, felt the support of the chair and allowed a slower exhalation. She then rehearsed the question aloud. At first, her voice was quiet and apologetic, and she surrounded the question with explanations designed to protect her from being wrong. Gradually, she practised saying the same words more simply. She was not pretending to be another person. She was using her own voice to attempt a response that her established protective system rarely permitted.

At the meeting, Annaโ€™s chest tightened and the familiar instruction returned: Wait until you are completely certain. This time, she asked the question. Nobody applauded, and she did not feel suddenly transformed. The question was answered and the meeting continued.

That ordinary continuation mattered. Anna had spoken while activated; her body mobilised and then began to recover. Her prediction of humiliation had not occurred, but neither had she proved that criticism would never happen. She learned something more credible: uncertainty did not make participation impossible. The anxiety was real, the bodily activation was real and the old prediction was still present. The action was also real.

Do not fake the feeling. Practise the action, remain connected to the body, observe what happens and allow the experience to revise what seems possible.

Annaโ€™s first experiment was introduced in an earlier article examining how embodied rehearsal, graded action, reflection and repetition may allow a previously inhibited response to become increasingly available within the Integrated-Self (Mirea, 2026). That article focused principally on the movement from a shame-organised protective pattern towards embodied possibility. Anna discovered that she could participate while anxiety and self-doubt remained present.

Her question at the meeting, however, was not an isolated success or the conclusion of the therapeutic process. It became the beginning of a broader inquiry into how she related to her work, her therapy and herself. If she no longer allowed the need to prove her competence, avoid exposure or surrender to self-attack to organise every decision, what would she genuinely value? What preferences, boundaries and ways of relating might become visible? Could an action that initially felt unfamiliar nevertheless be recognised as authentically her own?

The present article continues Annaโ€™s clinical illustration and develops the implications of this process for authenticity. Its central question is no longer only how a different response becomes possible, but what a person may discover and develop by repeatedly acting in relation to what matters. As Anna experimented with participation, honesty and self-respect across work and therapy, her values became more differentiated, previously obscured preferences and boundaries became increasingly available, and unfamiliar actions could gradually be recognised as her own.

The theoretical progression is therefore from embodied possibility towards values-guided authorship and authentic living. Imagery and rehearsal make a different response conceivable and enactable. Graded behavioural experiments test that response within the therapeutic relationship and everyday life. Reflection helps the person evaluate what the experience reveals about their values, preferences and capacities. Authorship connects the chosen action with a developing autobiographical understanding of self. Authenticity, from this perspective, is neither uncovered as a finished identity nor installed through repeated performance. It is discovered and developed through the continuing relationship among felt experience, values, chosen action, relational feedback and meaning.

People frequently postpone action until an internal state grants permission: When I feel confident, I will speak. When I stop feeling ashamed, I will allow myself to be visible. When I know who I really am, I will begin to live authentically. This expectation appears reasonable, yet it can maintain the very pattern the person hopes to escape. Confidence remains unavailable because participation is repeatedly postponed. Personal preferences remain unclear because approval is continually prioritised. Identity feels fixed because only a narrow protective repertoire is enacted.

The familiar instruction to โ€œfake it till you make itโ€ reverses this sequence by placing action before feeling. Its intuition is clinically useful, but its language is misleading. It suggests that change requires a counterfeit performance: the person should conceal anxiety, imitate a socially valued identity and continue until the performance becomes subjectively convincing. For clients whose difficulties already involve masking, compliance, perfectionistic performance or disconnection from their needs, such an instruction may reproduce the problem rather than resolve it.

A more useful starting point is that the person is already repeatedly enacting a way of being. Internalised shame is not maintained by belief alone. It is enacted through where attention is directed, how the body mobilises or withdraws, which words are spoken or withheld, how relationships are approached, and how the person interprets and treats themselves afterwards. Over time, these responses may become sufficiently familiar to be mistaken for identity.

The distinction between familiarity and authenticity is therefore crucial. A response does not necessarily express an authentic self simply because it feels natural or longstanding. Someone who has spent years accommodating other people may experience a reasonable boundary as artificial. A person organised around perfectionism may experience ordinary participation as careless. Someone accustomed to silence may describe speaking clearly as โ€œnot meโ€. These reactions do not prove that the unfamiliar response is fraudulent. They may show that the existing protective response has been rehearsed for longer.

The Pendulum-Effect Formulation identifies protective movement around a shared affective threat. The present article focuses specifically on movements organised around internalised shame, although other affective threats may organise comparable protective patterns. Within a shame-organised pattern, a person may move among three broad protective positions: Overcompensation, through which the shame-based account is disproved by achievement, control, perfectionism or approval; Avoidance, through which anticipated exposure is prevented; and Capitulation, through which the shame-based account is accepted as though it were established fact.

These positions may appear contradictory, but they can belong to the same protective system. The person may overperform until certainty or approval can no longer be secured, withdraw to escape anticipated exposure, and then attack or abandon the self for having withdrawn. Each response protects against or regulates the same affective threat while also restricting the personโ€™s available ways of acting and relating.

If protective Pendulum movements are already being repeatedly enacted, psychotherapy can redirect rather than invent the human capacity for rehearsal. The person can begin to imagine and embody responses organised around emerging values rather than shame. These responses are tested within the therapeutic relationship and everyday life, reflected upon, adapted and repeated. New emotions, preferences, boundaries and forms of relationship may emerge through this process.

The person does not simply behave differently because they have discovered a finished authentic self. Nor do they manufacture an identity by repeatedly performing a preferred character. Instead, they participate in developing a more authentic way of living through what they choose, enact, experience and make meaning of. Authenticity remains responsive to context: a chosen boundary may be authentic, but so may proportionate openness; participation may express a value, but so may deliberate withdrawal from an unsafe situation. Function and authorship matter more than appearance alone.

A behavioural experiment commonly tests a belief or prediction through planned experience rather than discussion alone (Greenberger and Padesky, 2016). A values-guided behavioural experiment is not designed merely to determine whether a feared prediction is accurate. It also explores what becomes possible when a value is permitted to influence action alongside fear, shame or self-doubt.

The person identifies the protective prediction, attempts a specific values-consistent response, observes its bodily, emotional and relational consequences, and reflects upon what the experience reveals about their capacities, preferences and ways of relating. The action may be retained, modified or rejected. The purpose is not to confirm a predetermined ideal but to generate information that could not become fully available while the person remained organised around proving, hiding or surrendering.

In this sense, the experiment tests not only what will happen in the situation, but what the person may become able to recognise, tolerate and choose. Through repetition across different contexts, a response that initially feels unfamiliar may become increasingly available. Through reflection and authorship, the person may also begin to recognise: This was not merely a role I performed. It was something I chose and was capable of doing.

The central proposition of this article is therefore:

Overcompensation, Avoidance and Capitulation repeatedly enact the predictions of internalised shame and can make those predictions feel personal and true.

Values-guided behavioural experiments use imagery, embodied rehearsal, relational testing and everyday action to explore alternative responses without requiring fear, shame or uncertainty to disappear first.

Through reflection, adaptation and repetition, these responses may become increasingly available within the Integrated-Self, while helping the person differentiate values, discover preferences and boundaries, recognise authorship and develop what an authentic life means for them.

Acting Truthfully Under Imagined Circumstances

The apparent contradiction between rehearsal and authenticity has a long history in the theatre. Acting can be treated as imitation: the performer reproduces recognisable external signs of emotion while remaining experientially separate from the role. Yet the tradition associated with Konstantin Stanislavski sought something more demanding than the reproduction of emotional appearance. His system was concerned with truthful, purposeful action within the given circumstances of the drama. The actor knows that the setting is constructed, but does not therefore approach every response as false. Through attention, imagination, objectives, physical action and repeated rehearsal, the performer develops conditions under which the role can be experienced and enacted with psychological credibility (Stanislavski, 2008, 2009).

Stanislavskiโ€™s โ€œmagic ifโ€ is especially relevant. The question is not simply, How would this character look? It is closer to, What would I do if I were living within these circumstances? The โ€œifโ€ creates an imaginative bridge without requiring the actor to confuse theatre with ordinary life. It connects possibility with action. The actor works neither by waiting passively for spontaneous inspiration nor by mechanically displaying an emotional stereotype. Rehearsal creates a structured route through which attention, intention, movement and feeling may become organised around the dramatic situation.

This does not mean that psychotherapy is theatre or that clients should perform invented characters. The parallel is more precise. Both fields challenge the assumption that authenticity must arrive fully formed before disciplined action begins. An actor may approach truthful performance through rehearsal; a client may approach a more authentic life by rehearsing actions that express values and inhibited capacities before those actions feel familiar. Indeed, their initial unfamiliarity does not make them fraudulent; it may simply reflect how much longer the existing protective response has been rehearsed.

At the same time, Stanislavskiโ€™s work warns against a shallow understanding of acting as if. The aim is not to paste the outward signs of confidence over an unchanged relationship with shame. In therapeutic rehearsal, the action requires an internal and relational purpose. The client is not instructed to appear assertive, warm or independent. They are invited to explore what they would do if a chosen valueโ€”self-respect, honesty, connection, curiosity or courageโ€”were allowed to influence the situation alongside fear.

Emotion, Role and Social Meaning

Lev Vygotskyโ€™s discussion of the psychology of the actor complicates any simple division between genuine and performed emotion. Engaging with Stanislavskiโ€™s system and Diderotโ€™s paradox of the actor, Vygotsky asked whether an actor must personally experience the feelings represented on stage or whether those feelings are produced through the organisation of performance. He rejected an account of the actorโ€™s emotion as a purely private or biological event. The experience is shaped by role, dramatic action, historical tradition, social meaning and the relationship with an audience (Vygotsky, 1999; original work published 1932).

Vygotsky did not provide a modern psychotherapy protocol for values or embodied rehearsal. His relevance lies elsewhere. He placed emotion within a culturally and socially organised activity. The actorโ€™s feeling cannot be understood simply by isolating an internal state from the role being enacted and the meanings surrounding it. This position helps resist two opposite errors in psychotherapy. The first is to treat an emotion as an unmediated revelation of identity: I feel inadequate, therefore inadequacy is who I am. The second is to treat emotion as irrelevant so long as an acceptable behaviour can be performed. In both acting and therapy, the relationship among feeling, action, meaning and context matters.

Values also acquire substance within social and practical life. They are shaped and negotiated within family, cultural, relational and material contexts rather than chosen by an isolated individual. Honesty, care, creativity or self-respect are not merely words selected from a list. They become meaningful through situated choices: what the person says when disagreement risks rejection; whether care includes boundaries; whether belonging requires self-erasure; and whether fear is permitted to coexist with participation. A value is not demonstrated by verbal endorsement alone. It becomes visible in patterns of action and relationship.

From this perspective, acting as if does not ask the client to experience a prescribed emotion. It asks whether a different action can be organised within the current emotional and relational conditions. The client may still feel fear, shame or doubt. The question is whether those experiences must control the entire response.

Role, Enactment and Surplus Reality

J. L. Moreno carried action and role directly into psychotherapy. In psychodrama, clients do not only describe conflicts, memories and relationships. They enter a structured dramatic space in which these experiences and possible responses can be enacted. Role reversal, doubling, mirroring and role training allow different perspectives and behavioural positions to be attempted, witnessed and reflected upon (Moreno, 1946; Cruz et al., 2018).

Morenoโ€™s role theory is particularly relevant to authenticity. He proposed that the self emerges through the roles a person develops and performs, describing role as a bridge between psychiatry, psychology and sociology (Moreno, 1946, 1961). Development, from this perspective, need not mean excavating one fixed identity concealed beneath behaviour. It may involve expanding the role repertoire and increasing spontaneity: the capacity to produce a sufficiently new response to an old situation, or an adequate response to a new one (Moreno, 1947, 1955).

This expansion does not require a person to become somebody else. A new role may offer temporary access to an inhibited capacity. Someone organised around compliance may rehearse disagreement. Someone governed by shame may practise being visible without performing perfection. Someone who anticipates helplessness may speak from a position of agency. Initially, the words can feel borrowed or artificial. Nevertheless, it is the clientโ€™s body producing the voice, tolerating the visibility and remaining in relationship.

Morenoโ€™s concept of surplus reality extends this possibility. The psychodramatic space permits enactment of what did not happen, has not yet happened or could not safely be expressed in everyday life (Moreno, 1965). A boundary may finally be spoken; an unacknowledged need may be voiced; a future encounter may be rehearsed. The enactment is not equivalent to lived reality, but it can provide an experiential bridge between what the person currently predicts and what they may gradually become able to tolerate and perform.

The fictional or protected frame may also reduce immediate self-surveillance. A client can first try a sentence โ€œin roleโ€, or speak from a chair representing a possible future position. Yet therapeutic consolidation eventually asks: What did you doโ€”not merely what did the role do? The purpose is not to credit a temporary character with the action, but to help the person recognise authorship of a capacity that was previously excluded from their self-understanding.

Contemporary drama-based interventions employ related processes, including role, narrative, enactment, distancing and witnessed performance. Reviews report promising findings while also identifying substantial variation in populations, interventions, methods and study quality (Berghs et al., 2022; Jiang et al., 2023). These findings justify careful clinical exploration; they do not establish that enactment reliably installs safety, authenticity or a new identity.

Mental Imagery in Values-Guided Experiments

Imagery adds an important psychological bridge between verbal intention and lived enactment. Mental imagery can evoke emotion more strongly than purely verbal representation and can simulate perceptual and experiential aspects of events (Holmes and Mathews, 2010; Ji et al., 2016). Prospective imagery can also influence anticipation, motivation and behavioural engagement, although effects depend upon the task, population and way imagery is used (Ji, Geiles and Saulsman, 2021; Cole et al., 2021).

This makes imagery clinically powerful but not inherently therapeutic. A shame-organised future image may function as a rehearsal of failure: the person sees faces turning towards them, hears their own voice falter, anticipates contempt and experiences bodily mobilisation before entering the room. Repetition may increase the subjective availability of the feared sequence. The image is treated as foresight rather than as a prediction shaped by prior learning.

Therapeutic imagery does not merely replace this scene with effortless success. An idealised image in which anxiety disappears and everyone responds warmly may be emotionally appealing but provide little preparation for the actual task. A more useful exercise activates the anticipated situation within tolerable limits and introduces a values-consistent response while preserving uncertainty.

The client might imagine entering a meeting and noticing the first signs of bodily bracing. They identify the urge to overexplain, remain silent or agree automatically. The image is slowed sufficiently to make choice possible. They then rehearse a concise contribution, feel their feet on the floor, direct attention towards the conversation and imagine remaining present while uncertainty continues. The sequence includes not only the desired action but recovery: how the person breathes after speaking, tolerates an ambiguous expression, responds to disagreement and prevents the event from becoming fuel for later self-attack.

Imagery therefore contributes at least four functions:

  1. It makes the shame-based prediction observable rather than unquestioned.
  2. It evokes sufficient affective and bodily involvement for rehearsal to be meaningful
  3. It permits alternative actions and responses to difficulty to be explored before real-world testing.
  4. It helps translate an abstract value into a situated pattern of attention, voice, movement and relationship.

The aim is not to imagine a completed ideal identity and perform it into existence. It is to create a provisional model of possible action, embody it sufficiently to increase the likelihood that it cn be accessed, test it, and revise it in response to experience.

The Pendulum-Effect Formulation: How Shame Narrows What Feels Possible

The Pendulum-Effect Formulation identifies a recurring movement among overcompensation, avoidance and capitulation around a shared affective threat. Shame is especially important because it readily becomes an account of the whole self. The person moves from:

 โ€˜I feel exposedโ€™ to โ€˜I am inadequateโ€™

โ€˜I made a mistakeโ€™ to โ€˜I am a failureโ€™

โ€˜This relationship feels uncertainโ€™ to โ€˜I am unlovableโ€™

Overcompensation attempts to disprove that conclusion. The person works excessively, controls detail, becomes indispensable, seeks reassurance, performs confidence or monitors other people for evidence of approval. Avoidance prevents the anticipated exposure by withholding opinions, declining contact, delaying action, concealing need or leaving situations. Capitulation accepts the shame-based conclusion through helplessness, self-attack, submissiveness or withdrawal from valued activity.

These positions are repeatedly embodied. Overcompensation may appear as urgency, muscular tension, restricted breathing, relentless speech and vigilant attention to other peopleโ€™s reactions. Avoidance may involve constricted movement, reduced voice, averted gaze and narrowed participation. Capitulation may be accompanied by heaviness, reduced agency and repetitive self-condemning language. The body does not merely display a belief that has already been formed elsewhere. Bodily state, attention, prediction, affect, behaviour and relationship participate in the experience from which the shame-based identity feels true (Barsalou, 2008; Niedenthal, 2007).

The Pendulum is also relationally self-reinforcing. A person who overfunctions may attract dependence while remaining unknown. Someone who conceals disagreement may experience relationships as superficially peaceful but internally unsafe. A person who withdraws before others can respond receives little information about whether contact, difference or repair were possible. Capitulation then interprets the resulting loneliness, exhaustion or resentment as evidence of defectiveness.

The issue is therefore not simply that the person possesses an inaccurate core belief. They repeatedly encounter themselves while proving, hiding or surrendering. These enacted experiences become autobiographical evidence for the identity they were originally designed to protect against.

The Pendulum positions can be summarised through three shame-organised instructions:

  • Overcompensation: I must prove my worth.
  • Avoidance: My presence, needs or imperfection must remain hidden.
  • Capitulation: The shame-based account of me is true, and I have no effective choice.

Therapeutic change does not add a fourth Pendulum position. It develops a more flexible alternative to automatic Pendulum control:

I can remain present, relate honestly and act according to what matters without having to prove, hide or abandon myself.

The Therapeutic Relationship as the First Site of Experimentation

The therapy room is not merely a protected place in which the client prepares for relationships elsewhere. It is itself a real relationship in which the Pendulum may become visible.

A client moving towards overcompensation may try to become the ideal client: completing every task perfectly, intellectualising their experience, presenting sophisticated explanations or assuring the therapist that treatment is working. Another may monitor the therapistโ€™s face and rapidly revise what they say. Avoidance may appear through silence, changing the subject, minimising need, withholding disagreement, arriving late or becoming emotionally absent. Capitulation may involve automatic agreement, treating the therapist as unquestionably right, relinquishing agency or interpreting therapeutic difficulty as proof of being beyond help.

These responses should not be confronted as resistance or dishonesty. They can be recognised as relationally intelligent adaptations with histories and protective purposes. The therapeutic question becomes: What does this movement anticipate, prevent, disprove or make certain between us?

Once recognised, the relationship offers an immediate opportunity for a different response. The client may rehearse telling the therapist that a formulation does not fit, that an intervention felt unhelpful, that they are disappointed, or that they need more time. They may allow a silence without filling it through performance. They may receive care without becoming compliant, or express a boundary without withdrawing from the relationship.

Authenticity here does not mean unrestricted disclosure or saying everything one feels. It means that the client can increasingly remain in contact with experience, values and agency while responding to the actual relationship. A boundary can be authentic; so can chosen privacy. Connection can be authentic; so can proportionate distance. The relevant distinction is not between participation and withdrawal in themselves, but between chosen action and action automatically organised by shame.

This therapeutic enactment provides several forms of learning. The client discovers that difference need not automatically destroy connection, that embarrassment can be survived, that misunderstanding may be repaired and that a relationship can contain two perspectives. Equally, the therapistโ€™s response may reveal that the clientโ€™s concern is valid. The aim is not to force every experiment into a reassuring conclusion. Authenticity requires contact with reality, including disappointment, limitation and the need for protection.

Values as Directions That Become Known Through Living

Values provide an organising alternative to the Pendulum, but they should not become another perfectionistic standard. Within contextual behavioural traditions, values are commonly understood as chosen qualities or directions of action rather than outcomes that can be permanently completed (Hayes, Strosahl and Wilson, 2012). In the present formulation, values help answer a specific question: If shame did not make the entire decision, what way of relating would matter here?

The answer may involve honesty, connection, curiosity, courage, care, creativity, self-respect or justice. Yet values are not always fully accessible before action. A person whose preferences have been organised around approval may genuinely not know what they like. Someone who has survived through compliance may struggle to distinguish care from self-erasure. Values clarification therefore cannot be confined to selecting admirable words.

Values become differentiated through lived experiments. The person notices which actions produce vitality, integrity, grief, relief, resentment or connection. They discover that a presumed value was inherited from a family or social role, while an overlooked interest becomes personally meaningful. New likes and dislikes emerge. Boundaries become more specific. The person learns not only what they wish to approach but what they no longer consent to organise their life around.

This is why authenticity is both discovered and developed. It is discovered because the person attends more carefully to felt experience, history, need and desire. It is developed because preferences and capacities change through action, relationship and reflection. The emerging self is neither arbitrary nor predetermined.

Values-consistent action is not always the outward opposite of the Pendulum behaviour. Leaving a dangerous relationship may resemble avoidance while expressing self-protection. Working intensely on a meaningful task may resemble overcompensation while expressing creativity or commitment. Yielding in an unimportant disagreement may resemble capitulation while reflecting generosity or proportion. Function, context and choice matter more than appearance.

The relevant alternative is therefore not necessarily the visible opposite of the existing behaviour, but action that differs from the function of the shame-based strategy. The person does not automatically obey the command to prove, hide or surrender. They choose a response proportionate to present reality and connected to what matters.

A Clinical Illustration: From Protective Performance to Values-Guided Participation

โ€œAnnaโ€ is a fictionalised composite constructed from several clinically similar cases. Identifying details, circumstances and sequences of events have been altered and combined to protect confidentiality. She had long experienced anxiety in social and interpersonal situations, although her difficulties did not fully meet the diagnostic criteria for social anxiety disorder. Her question at the meeting was not an isolated success. It marked the beginning of a broader inquiry into how she related to her work, her therapy and herself.

In anticipation of shame, Anna moved towards overcompensation. She prepared excessively, mentally rehearsed every sentence and attempted to eliminate the possibility of error. She volunteered for additional work so that her value would be unquestionable and monitored other peopleโ€™s expressions for evidence that she had performed well. When certainty or approval could not be secured, she moved towards avoidance: delaying a contribution, weakening what she wanted to say or remaining silent. Afterwards she capitulated, attacking herself and treating her silence or imperfection as proof that she was weak and incapable.

These apparently contradictory responses belonged to the same protective system. Overcompensation attempted to disprove the shame-based account; avoidance prevented its anticipated exposure; capitulation surrendered to it as though it were established fact. Anna also recognised their bodily organisation: urgency, muscular tension and rapid internal rehearsal while proving; constriction and reduced voice while hiding; heaviness and diminished agency while surrendering.

The pattern entered therapy. Anna prepared detailed accounts, searched for the โ€œrightโ€ insight and worried about disappointing the therapist. When an interpretation did not fit, she often nodded rather than disagreeing. Therapy could therefore become another place in which she performed competence while remaining partly unknown.

Anna began with two provisional values: honesty and participation. They were provisional because she did not yet know precisely what they would require or what further preferences they might reveal. A recurring therapeutic question was:

If shame and self-doubt did not have the final say, how would I want to relate in this moment?

In imagery, Anna pictured telling the therapist that a recent exercise had felt too structured. Her first imagined sequence ended with the therapist becoming defensive and Anna apologising. The scene was slowed. She noticed the urge to protect the therapist, allowed a longer exhalation and rehearsed one sentence: โ€œI understood the purpose, but I felt less connected to you while we were doing it.โ€ She imagined curiosity, misunderstanding and partial disagreement, and practised remaining present rather than overexplaining, withdrawing or conceding that her experience was wrong.

Anna then said the sentence in the session. The therapist acknowledged the disconnection and invited further discussion. More important than reassurance was Annaโ€™s discovery that she could express a difference, remain physiologically activated and continue relating. She had not performed confidence. She had enacted honesty while uncertain, and the therapeutic relationship had become a real site of rehearsal and revision.

Her subsequent daily experiments developed from the first meeting question. In a later discussion, she expressed a preference about the direction of a project without assembling an exhaustive defence. On another occasion, she declined an additional task rather than using indispensability to secure her position. Neither action felt natural at first. Both were consistent with participation that did not require self-abandonment.

The results were mixed. One colleague welcomed her view; another disagreed. Her boundary was accepted, although she spent part of the evening wanting to reverse it. Reflection focused not only on whether other people approved but on what Anna noticed about herself. She felt interested when collaboration allowed ideas to be developed openly, depleted by status-driven competition and resentful when care became compulsory availability. These reactions were not treated as unquestionable instructions, but as information that chronic approval-seeking had previously obscured.

Across subsequent experiments, Annaโ€™s values became more specific. โ€œHonestyโ€ came to include not pretending agreement. โ€œParticipationโ€ meant contributing without performing perfection and allowing others to carry responsibility. Self-respect came to include recoverable limits. She discovered satisfaction in mentoring less experienced colleagues and less interest than she had assumed in advancement organised around visibility and competition. New likes, dislikes, emotions and boundaries did not appear because a finished authentic self had finally been uncovered. They emerged as Anna created enough behavioural and relational space to encounter them.

Anna continued to move towards all three Pendulum positions. Integration did not mean their disappearance, nor did a functionally alternative response require her to occupy the other extreme. She was not asked to replace silence with dominance, compliance with reflexive disagreement or overwork with disengagement. The developing alternative was flexible participation: neither proving, hiding nor surrendering.

Her emerging self-understanding was not, I am finally confident and authentic. It was more credible:

I can notice the urge to prove, hide or surrender and still choose how I want to participate.

A Values-Guided Cycle of Behavioural Experimentation

The therapeutic process is better understood as an iterative cycle than as a fixed sequence applied identically to every client. It begins by recognising a movement towards overcompensation, avoidance or capitulation and identifying the affective threat, prediction, bodily organisation, attentional pattern and relational function involved. The therapist and client then clarify an emerging value without converting it into an idealised identity: I want to relate with honesty is more workable than I must become a completely authentic person.

Present-tense, multisensory imagery can bring the anticipated situation and its difficulties into tolerable contact. The image includes the Pendulum impulse, the values-consistent response, uncertain outcomes and the possibility of recovery rather than scripting compulsory success. The value is translated into one observable responseโ€”a sentence, boundary, request, pause or form of participationโ€”and rehearsed through voice, posture, movement and attention. Regulation supports sufficient capacity for learning; it does not require complete calm.

Where relevant, the response can first be enacted within the therapeutic relationship through honesty, disagreement, need, boundary or repair. Because the relationship has real consequences, this encounter cannot be reduced to role-play. The response is then tested in a graded situation in everyday life: one that matters enough to activate the established prediction while remaining sufficiently manageable for observation and recovery.

Reflection compares what was predicted with what occurred, while also attending to bodily recovery, relational consequences, emerging preferences and unexpected meanings. Elements of the response can be retained, modified or rejected. Repetition across settings may increase the capacityโ€™s availability, provided that experimentation remains responsive rather than becoming another rigid rule.

The cycle culminates provisionally in authorship. Here, authorship means recognising a response as something the person has chosen, enacted and incorporated into an evolving understanding of themselves, rather than merely something performed in response to therapeutic instruction or external expectation. The action is connected to a credible account of self: A part of me anticipated shame, and I was also capable of acting according to what mattered. The person owns the action without treating it as evidence of permanent transformation or a completed identity. That authorship then informs the next experiment rather than completing the process.

Authenticity and the Development of the Integrated-Self

Authenticity is sometimes imagined as perfect correspondence between inner feeling and outward behaviour. Such a definition is neither clinically realistic nor ethically sufficient. People contain competing wishes, affects and obligations. Privacy is not necessarily falseness; restraint is not necessarily capitulation; adaptation is not necessarily masking. Authenticity requires context and proportion.

Within this article, an authentic life refers to an increasingly coherent relationship among experience, values and chosen action. The person can recognise fear without allowing fear to impersonate identity, acknowledge shame without accepting its global verdict, and respond to relationship without automatically proving, hiding or surrendering.

Authenticity and integration are therefore related but not identical. Authenticity concerns how experience, values and chosen action are brought into relationship in a particular life. Integration concerns the breadth, connection and flexible availability of the personโ€™s repertoire.

The Integrated-Self refers to the wider and more connected repertoire that develops through this process. Different affects, needs, roles, values and action tendencies can be acknowledged without one protective position controlling the whole response. Integration does not replace the Pendulum with a permanently confident character. It expands what the person can recognise, tolerate, choose and enact.

The personโ€™s identity is therefore not treated as a statement to be installed through repetition. Rehearsal provides experiences; experience generates affective, relational and practical information; reflection organises meaning; and meaning influences subsequent imagination and action. Development remains recursive. What is imagined is tested against reality, and reality revises what is imagined.

This account also leaves room for surprise. A person may discover that a long-pursued goal belonged largely to overcompensation. They may experience anger where compliance previously obscured it, grief when avoidance recedes, or pleasure in an activity they had dismissed. A more authentic life is not simply a calmer version of the old one. It may involve new relationships, interests, boundaries and values.

The phrase reinventing oneself is useful if it does not imply discarding history or manufacturing an ideal persona. Reinvention can mean reorganising the relationship with what has been inherited: preserving capacities that remain valuable, relinquishing responses that have become restrictive and developing possibilities that earlier environments did not permit.

When Values-Guided Experiments Become Another Performance

Embodied rehearsal is not inherently liberating. It can reproduce the Pendulum when it is used to demand acceptable performance.

Rehearsal can become masking when the person is encouraged to conceal distress, fatigue, disability or neurodivergent difference in order to satisfy social expectations.

Values can become overcompensation when they are converted into moral standards the person must perform perfectly. Courage does not require maximal exposure; compassion does not require self-erasure; authenticity does not require indiscriminate disclosure.

Imagery can become coercive when the therapist supplies an ideal future that reflects therapeutic preference rather than the clientโ€™s emerging direction.

Functionally alternative action can become flooding when the person is pushed into overwhelming exposure without sufficient consent, preparation or capacity for recovery.

Relational rehearsal can become compliance when the therapist interprets agreement, emotional expression or apparent closeness as evidence of progress while overlooking the clientโ€™s fear of displeasing them.

Trauma survivors may already have extensive experience of performing compliance while internally mobilised, frozen or dissociated. Inviting further enactment without attending to power, consent and bodily cues risks repeating the very pattern therapy intends to change. Regulation and relational safety are not optional preliminaries to โ€œrealโ€ action; they are part of the conditions under which action can remain chosen and learnable.

Scientific and Conceptual Limits

This article offers a conceptual formulation rather than evidence for a uniquely validated NA-CBT mechanism. Grounded cognition, mental imagery research, psychodrama and behavioural experimentation provide relevant but distinct bodies of knowledge. Their conceptual convergence does not prove that a particular sequence produces an Integrated-Self.

Performed, imagined and lived experiences may overlap in perceptual, motor and affective processes, but they are not interchangeable. Context, consequence, relationship, agency and autobiographical meaning affect what is learned. A successful rehearsal in therapy may not generalise; a values-consistent action may receive a painful response; repetition may consolidate rigidity if it occurs without reflection and adaptation.

Likewise, neuroplasticity is a general property of the nervous system, not evidence that every imagined or repeated action produces therapeutic change. Claims concerning neurological encoding, simulation or reconsolidation require specification of the process measured, the population studied, the conditions and the durability of any effect.

The Pendulum-Effect Formulation also requires empirical development. Its value in the present article is heuristic: it organises observable movement among three protective positions and supports collaborative selection of an alternative response. Future research should examine the formulationโ€™s reliability, clinical utility and incremental contribution beyond established CBT, contextual behavioural and experiential approaches.

Conclusion

Authenticity need not be fully known before values-consistent action begins. Equally, it cannot be manufactured by counterfeiting confidence or performing an ideal identity. The person is not asked to suppress shame or behave as though vulnerability has disappeared. They are invited to recognise how shame may already be organising a restricted and repeatedly enacted repertoire.

Overcompensation rehearses the need to prove worth. Avoidance rehearses the danger of being seen. Capitulation rehearses the apparent truth of the shame-based account. Because these strategies are enacted cognitively, bodily and relationally, their familiarity may be mistaken for authenticity.

Values-guided behavioural experiments can redirect this capacity for repeated enactment. Imagery makes a different response conceivable. Embodied rehearsal gives it voice, posture, movement and affective relevance. The therapeutic relationship allows it to be attempted with another person, while graded action in everyday life tests it beyond the therapy room. Reflection, recovery and repetition help the person evaluate what occurred, recognise authorship and relate the experience to a developing autobiographical understanding.

Through this process, the person may discover preferences, boundaries, relationships and values that could not be fully known while life was organised around proving, hiding or surrendering. Authenticity is therefore neither simply found before action nor installed through performance. It is discovered and developed as imagined possibilities are embodied, lived, evaluated and revised. The Integrated-Self does not denote a permanently confident or completed identity. It describes an increasingly connected and flexible repertoire in which affects, needs, values and action tendencies can be acknowledged without one protective position automatically controlling the whole response.

The central therapeutic question is therefore not, How can I convincingly pretend to be someone else? It is:

If shame did not have the final say, what way of living would I be willing to imagine, test and gradually make my own?

References

Barsalou, L.W. (2008) โ€˜Grounded cognitionโ€™, Annual Review of Psychology, 59, pp. 617โ€“645. https://doi.org/10.1146/annurev.psych.59.103006.093639

Berghs, M., Prick, A.J.C., Vissers, C. and van Hooren, S. (2022) โ€˜Drama therapy for children and adolescents with psychosocial problems: a systematic review on effects, means, therapeutic attitude, and supposed mechanisms of changeโ€™, Children, 9(9), 1358. https://doi.org/10.3390/children9091358

Cole, S.N., Smith, D.M., Ragan, K., Suurmond, R. and Armitage, C.J. (2021) โ€˜Synthesizing the effects of mental simulation on behavior change: systematic review and multilevel meta-analysisโ€™, Psychonomic Bulletin & Review, 28(5), pp. 1514โ€“1537. https://doi.org/10.3758/s13423-021-01880-6

Cruz, A., Sales, C.M.D., Alves, P. and Moita, G. (2018) โ€˜The core techniques of Morenian psychodrama: a systematic review of the literatureโ€™, Frontiers in Psychology, 9, 1263. https://doi.org/10.3389/fpsyg.2018.01263

Greenberger, D. and Padesky, C.A. (2016) Mind Over Mood: Change How You Feel by Changing the Way You Think. 2nd edn. New York: Guilford Press.

Hayes, S.C., Strosahl, K.D. and Wilson, K.G. (2012) Acceptance and Commitment Therapy: The Process and Practice of Mindful Change. 2nd edn. New York: Guilford Press.

Holmes, E.A. and Mathews, A. (2010) โ€˜Mental imagery in emotion and emotional disordersโ€™, Clinical Psychology Review, 30(3), pp. 349โ€“362. https://doi.org/10.1016/j.cpr.2010.01.001

Ji, J.L., Burnett Heyes, S., MacLeod, C. and Holmes, E.A. (2016) โ€˜Emotional mental imagery as simulation of reality: fear and beyondโ€”a tribute to Peter Langโ€™, Behavior Therapy, 47(5), pp. 702โ€“719. https://doi.org/10.1016/j.beth.2015.11.004

Ji, J.L., Geiles, D. and Saulsman, L.M. (2021) โ€˜Mental imagery-based episodic simulation amplifies motivation and behavioural engagement in planned reward activitiesโ€™, Behaviour Research and Therapy, 145, 103947. https://doi.org/10.1016/j.brat.2021.103947

Jiang, L., Alizadeh, F. and Cui, W. (2023) โ€˜Effectiveness of drama-based intervention in improving mental health and well-being: a systematic review and meta-analysis during the COVID-19 pandemic and post-pandemic periodโ€™, Healthcare, 11(6), 839. https://doi.org/10.3390/healthcare11060839

Mirea, D. (2026) โ€˜Beyond โ€œFake It Till You Make Itโ€: The Pendulum-Effect, Embodied Rehearsal and the Development of the Integrated-Selfโ€™, The NeuroAffective-CBTยฎ Journal, 3 September. Available at: https://neuroaffectivecbt.com/2026/09/03/beyond-fake-it-till-you-make-it-the-pendulum-effect-embodied-rehearsal-and-the-development-of-the-integrated-self/ (Accessed: 12 September 2026).

Moreno, J.L. (1946) Psychodrama: First Volume. Beacon, NY: Beacon House.

Moreno, J.L. (1947) The Theatre of Spontaneity. Beacon, NY: Beacon House.

Moreno, J.L. (1955) โ€˜Theory of spontaneity-creativityโ€™, Sociometry, 18(4), pp. 105โ€“118. https://doi.org/10.2307/2785848

Moreno, J.L. (1961) โ€˜The role concept: a bridge between psychiatry and sociologyโ€™, American Journal of Psychiatry, 118(6), pp. 518โ€“523.

Moreno, J.L. (1965) โ€˜Therapeutic vehicles and the concept of surplus realityโ€™, Group Psychotherapy, 18, pp. 211โ€“216. https://doi.org/10.12926/ek7xhv15

Niedenthal, P.M. (2007) โ€˜Embodying emotionโ€™, Science, 316(5827), pp. 1002โ€“1005. https://doi.org/10.1126/science.1136930

Stanislavski, K. (2008) An Actorโ€™s Work: A Studentโ€™s Diary. Translated and edited by J. Benedetti. London: Routledge.

Stanislavski, K. (2009) An Actorโ€™s Work on a Role. Translated and edited by J. Benedetti. London: Routledge.

Vygotsky, L.S. (1999) โ€˜On the problem of the psychology of the actorโ€™s creative workโ€™, in Rieber, R.W. (ed.) The Collected Works of L. S. Vygotsky, Volume 6: Scientific Legacy. New York: Kluwer Academic/Plenum, pp. 237โ€“244. (Original work published 1932.)


Confidentiality and composite-case statement

โ€œAnnaโ€ is a fictionalised composite constructed from several clinically similar cases and is not a single client presented under a pseudonym. Identifying details, circumstances and sequences of events have been altered and combined to protect confidentiality. The illustration does not represent the complete treatment history of any individual client.

Copyright

ยฉ 2026 Daniel Mirea. All rights reserved.

Beyond the Mirror: A NeuroAffective-CBT Case Study of Body Dysmorphic Disorder

Dr Oana Barnett (July, 2026)
|ย The NeuroAffective-CBTยฎ Journal |ย 

Abstract

Body Dysmorphic Disorder (BDD) is a debilitating psychological condition characterised by persistent preoccupation with perceived defects in physical appearance, often resulting in significant emotional distress, functional impairment, and repetitive safety behaviours. Although cognitive-behavioural therapy (CBT) remains the recommended psychological intervention for BDD, many individuals continue to experience recurrent symptoms despite previous therapeutic gains.

This case study introduces NeuroAffective-CBT (NA-CBT) through the treatment of “Sophie”, a woman in her fifties presenting with longstanding Body Dysmorphic Disorder, chronic shame, recurrent depression, insomnia, social withdrawal, and increasing psychological distress following menopause, occupational loss, and repeated cosmetic procedures. Rather than conceptualising these difficulties as isolated symptoms, NA-CBT formulated them as interacting manifestations of increased neuroaffective load, arising through the dynamic relationship between physiology, affect, cognition, autobiographical memory, and interpersonal experience.

Grounded within the cognitive behavioural tradition, NA-CBT integrates contemporary neuroscience, affective science, lifestyle medicine, and behavioural psychology while maintaining the collaborative, structured and evidence-informed principles that characterise CBT (Beck, 1976, 2021; Clark & Beck, 2010). Central to this formulation is the TED (Tiredโ€“Exerciseโ€“Diet) framework, alongside the Bodyโ€“Brainโ€“Affect Triangle, which together provide a practical model for understanding how physiological regulation influences affective processing, cognitive interpretation, and psychological flexibility (Mirea, 2023, 2025a, 2025b).

Treatment focused on reducing neuroaffective load, strengthening physiological regulation, facilitating NeuroAffective Narrative Reconsolidation, and supporting the gradual emergence of a more coherent and compassionate Integrated-Self. Throughout therapy, the therapist repeatedly returned to a simple but clinically significant question:

“What might be maintaining your neuroaffective load, and what might help reduce it?”

Rather than replacing established cognitive behavioural models of Body Dysmorphic Disorder, NA-CBT extends them by integrating affective neuroscience and physiological regulation into psychological formulation and intervention. This case study illustrates how an integrated neuroaffective perspective may enhance therapeutic understanding and contribute to the treatment of complex presentations characterised by chronic shame, self-criticism, and recurrent emotional distress.

Keywords: Body Dysmorphic Disorder; Cognitive Behavioural Therapy; NeuroAffective-CBT; Affect; Neuroscience; TED; Lifestyle Interventions; Integrated-Self.

Introduction

Body Dysmorphic Disorder (BDD) is characterised by persistent preoccupation with perceived defects in physical appearance that are either unobservable or appear slight to others (American Psychiatric Association, 2022). These concerns are typically accompanied by repetitive behaviours such as mirror checking, camouflage, reassurance seeking, appearance comparisons, and avoidance of social situations. The condition frequently results in profound impairment across occupational, interpersonal, and emotional domains and is associated with elevated rates of depression, anxiety, social isolation, and suicidality (Phillips, 2005; Phillips et al., 2010).

Cognitive Behavioural Therapy (CBT) remains the recommended psychological treatment for Body Dysmorphic Disorder, with substantial evidence supporting interventions targeting dysfunctional appearance beliefs, selective attention, avoidance, and safety behaviours (Veale, 2004; Veale & Neziroglu, 2010; Wilhelm et al., 2013). Nevertheless, many individuals continue to experience recurring symptoms following successful therapy, particularly when significant life transitions, physiological changes, or cumulative adversity increase emotional vulnerability.

These observations invite an important clinical question: Is recurrence always evidence that previous therapy has failed? Or might it reflect a profound change in the physiological and affective conditions within which previously acquired psychological skills are now expected to operate?

NeuroAffective-CBT (NA-CBT) emerged from this question. NA-CBT belongs firmly within the broad family of cognitive behavioural therapies. It retains the structured formulation, collaborative empiricism, behavioural experimentation, and evidence-informed practice that have long characterised CBT (Beck, 1976; Beck, 2021; Clark & Beck, 2010). What distinguishes NA-CBT is not a departure from cognitive behavioural principles, but a greater depth of integration. It draws together contemporary neuroscience, affective science, physiology, attachment, and behavioural psychology within a unified cognitive behavioural formulation (Damasio, 1999; LeDoux, 2015; Panksepp, 1998; Mirea, 2018).

Here, philosophy meets science. The body meets the mind.

Rather than conceptualising emotional distress as existing solely within cognition, NA-CBT understands psychological experience as emerging through continuous interactions between physiology, affective systems, cognitive interpretation, autobiographical memory, and interpersonal relationships. Mind and body are therefore not treated as separate domains requiring different explanatory models, but as components of a single, dynamically regulated neuroaffective system (Barrett, 2017; Friston, 2010; Siegel, 2012).

This perspective does not replace existing CBT models of Body Dysmorphic Disorder. Instead, it extends them by asking an additional question:

What neuroaffective conditions allow these cognitive and behavioural processes to become more or less dominant?

The following case study illustrates how this formulation informed the treatment of a woman with longstanding Body Dysmorphic Disorder whose psychological difficulties unfolded against a backdrop of increasing physiological, relational, and emotional burden.

Case Presentation

Sophie was a woman in her early fifties who self-referred for psychological therapy following a significant deterioration in her emotional wellbeing. She had previously completed a course of Cognitive Behavioural Therapy several years earlier, during which she developed a good understanding of the cognitive and behavioural processes maintaining her appearance concerns. She described this therapy positively and reported that it had enabled her to manage her symptoms effectively for a number of years.

However, by the time she returned to therapy, Sophie no longer felt able to access the psychological flexibility she had previously achieved.

Over the intervening years, she had undergone several cosmetic procedures in the hope of correcting perceived flaws in her appearance. Rather than reducing her distress, these interventions intensified her preoccupation, leaving her feeling increasingly disfigured and emotionally devastated. She subsequently became involved in prolonged legal proceedings against one of the practitioners, describing the experience as deeply invalidating and reinforcing her conviction that she had been permanently damaged.

Alongside these experiences, Sophie’s life had changed considerably. She was now navigating menopause, persistent insomnia, increasing fatigue, and declining physical energy. She had lost her employment and found it difficult to secure another position. The increasing reliance on online meetings following the COVID-19 pandemic intensified her appearance concerns, as seeing herself on camera throughout the working day became a persistent source of anxiety and self-monitoring. She frequently turned her camera off whenever possible and described feeling acutely self-conscious whenever she was visible on screen.

Socially, Sophie reported becoming increasingly isolated. Although married, she experienced growing emotional distance within her relationship and described feeling profoundly alone. Her family of origin remained abroad, limiting opportunities for support. She also spoke with increasing sadness about never having had children, describing this as a source of grief that had become more salient as she grew older.

Despite continuing to use many of the cognitive strategies she had learned previously, Sophie experienced overwhelming shame, chronic self-criticism, increasing avoidance, disrupted sleep, emotional exhaustion, and persistent beliefs that she was fundamentally defective. She no longer described herself as simply feeling unattractive.She described feeling broken.

From a conventional CBT perspective, these changes might reasonably be understood as an exacerbation of existing Body Dysmorphic Disorder following multiple adverse life events. From a NeuroAffective-CBT perspective, however, a different question emerged:

What had changed within Sophie’s neuroaffective system that made previously effective psychological strategies increasingly difficult to access?

Developmental Experiences and the Emergence of the Integrated-Self

Sophie’s appearance concerns did not emerge in isolation. As therapy progressed, it became increasingly apparent that her relationship with beauty, worth, and belonging had developed within a family environment in which physical appearance carried considerable emotional significance.

She described growing up with the implicit understanding that beauty was more than an aesthetic qualityโ€”it reflected character, value, and lovability. Family conversations frequently centred on appearance, and those considered physically attractive appeared to receive greater admiration, attention, and warmth. Beauty became quietly associated with being “a good person”, while ordinary appearance felt synonymous with being overlooked.

One figure came to symbolise this experience throughout Sophie’s childhood.

Her cousin was widely regarded within the family as exceptionally beautiful. Sophie recalled adults openly commenting on her cousin’s appearance with admiration and delight, describing her as special, elegant, and somehow different from everyone else. As a young girl, Sophie became convinced that if she could somehow become beautiful enough, she too might receive the same affection, recognition, and emotional closeness from her mother and older sister.

Although this belief was never explicitly stated, it gradually became woven into her understanding of herself and others.

Beauty became associated with safety.Acceptance became conditional. Worth became something that had to be earned.

From a NeuroAffective-CBT perspective, these experiences contributed to the development of Deeply Rooted Beliefs (DRBs) concerning identity, acceptance, and interpersonal value. Unlike automatic thoughts, DRBs are understood as emotionally organised assumptions that develop over repeated affective experiences and gradually shape how individuals interpret themselves, others, and the world (Beck, 1976; Mirea, 2018). These beliefs rarely operate at the level of deliberate reasoning. Instead, they become embedded within autobiographical memory, affective prediction, and patterns of physiological responding.

One childhood memory remained particularly vivid throughout therapy.

Sophie recalled accompanying her cousin into a shop during adolescence. Her cousin secretly stole an item before leaving the store. Moments later, the shop assistant stopped Sophie, accusing her of the theft. Despite Sophie’s repeated insistence that she had done nothing wrong, the accusation continued. What remained most emotionally significant was not the theft itself, but the explanation she believed lay behind the accusation.

She recalled the shop assistant commenting that her cousin “looked too beautiful” to have stolen anything, whereas Sophie, with her darker features, “looked like the sort of person who would.” Whether these words were remembered verbatim or reconstructed over time became less important than the emotional meaning they continued to hold.

For Sophie, the experience crystallised a painful conclusion:

“People see something bad in me before they know me.”

The memory became one of the earliest examples of shame becoming organised not around behaviour, but around identity.

Many years later, this image continued to intrude unexpectedly. It frequently emerged before social situations, during work meetings, while shopping, and whenever Sophie felt herself being observed. Although intellectually she recognised the event belonged to the past, emotionally it continued to feel immediate. Her body responded as though the judgement were happening again in the present.

From a NeuroAffective-CBT perspective, such memories are understood not simply as autobiographical recollections but as emotionally encoded experiences that continue to influence present-day prediction and affective regulation (Lane et al., 2015; Brewin, 2014). Rather than remaining historical events, they become living templates through which new interpersonal experiences are interpreted.

Importantly, therapy did not conceptualise these experiences as evidence of a permanently fragmented self.

Instead, NA-CBT assumes that beneath layers of shame, fear, self-protection, and defensive adaptation lies an Integrated-Self, a coherent and compassionate sense of identity that has become increasingly difficult to access under conditions of sustained neuroaffective load (Mirea, 2018).

The therapeutic task therefore shifts. Rather than asking how the fragmented self can be repaired, NA-CBT asks:

What conditions might allow the Integrated Self to emerge more consistently?

This subtle change in formulation proved clinically important. It invited both therapist and client to become curious about the conditions supporting psychological integration, rather than focusing exclusively on pathology or symptom reduction.

Pause for Curiosity

Perhaps the most important question was no longer:

“Why does Sophie continue to experience Body Dysmorphic Disorder?”

Instead, therapy repeatedly returned to a different question:

“What might be maintaining Sophie’s neuroaffective load, and what might help reduce it?”

This question became a recurring anchor throughout therapy.

Rather than assuming that distress reflected psychological weakness or therapeutic failure, it invited curiosity about the interaction between physiology, affect, cognition, memory, relationships, and the broader context in which emotional regulation was taking place.

Within NeuroAffective-CBT, curiosity is not simply a therapeutic attitude.

It is a clinical intervention.

Neuroaffective Formulation

The developmental formulation helped explain why Sophie’s appearance concerns had become so emotionally significant. The next therapeutic question was equally important:

Why had these difficulties intensified now, after several years of relative stability?

Although Sophie retained many of the cognitive insights she had developed during her previous course of CBT, she increasingly described feeling unable to access them during periods of emotional distress. She understood that her thoughts were often biased, recognised many of her appearance-related safety behaviours, and could frequently identify alternative interpretations. Yet these skills no longer seemed sufficient to regulate the intensity of her emotional experience.

Rather than viewing this as evidence that therapy had failed, NA-CBT approached it as evidence that the neuroaffective conditions within which these cognitive skills operated had fundamentally changed.

Over recent years Sophie had experienced the cumulative impact of persistent insomnia, menopausal transition, occupational loss, increasing social isolation, repeated cosmetic procedures, prolonged legal proceedings, reduced physical activity, and the gradual erosion of interpersonal support. Each experience contributed not simply to “stress,” but to an increasing burden on the systems responsible for physiological regulation, emotional processing, and cognitive flexibility.

Within NeuroAffective-CBT, this accumulation is conceptualised as neuroaffective load (Mirea, 2018).

Neuroaffective load refers to the cumulative demands placed upon the integrated body-brain system through ongoing physiological dysregulation, affective activation, interpersonal adversity, cognitive burden, and environmental pressures. Unlike the broader concept of stress, neuroaffective load emphasises the dynamic interaction between bodily regulation and psychological functioning. It recognises that emotional suffering often emerges not from a single precipitating event but from the gradual accumulation of multiple interacting influences that reduce the nervous system’s capacity for flexible adaptation.

This distinction proved clinically meaningful.

When Sophie was invited to consider her difficulties through the lens of neuroaffective load, her experience began to make sense in a different way. Rather than concluding that she had “gone backwards” or that she had somehow lost the benefits of her previous therapy, she became increasingly able to understand why familiar psychological strategies were becoming harder to access.

Her brain had not forgotten what she had learned. It was working under very different physiological and affective conditions. This understanding became one of the most compassionate moments within therapy. Rather than asking,

“Why can’t I cope anymore?”

Sophie gradually found herself asking,

“What has happened to my system that makes coping so much harder?”

The question itself represented an important therapeutic shift.

Pause for Curiosity

Perhaps psychological resilience is not simply a characteristic that people possess.

Perhaps it is an emergent property of a nervous system that has sufficient physiological and emotional capacity to remain flexible.

If so, therapy may need to become curious not only about thoughts and behaviours, but about the conditions that either increase or reduce neuroaffective load.

This broader perspective also complements established cognitive behavioural models of Body Dysmorphic Disorder, which emphasise dysfunctional appearance beliefs, selective attention, mirror checking, reassurance seeking, avoidance, and safety behaviours in maintaining distress (Veale, 2004; Veale & Neziroglu, 2010; Phillips, 2005; Wilhelm et al., 2013). Rather than replacing these well-established formulations, NA-CBT seeks to extend them by incorporating physiological regulation, affective neuroscience, and predictive brain processes as interacting influences on these cognitive and behavioural maintenance cycles.

In doing so, the formulation broadens the therapeutic focus. The question is no longer solely,

“What thoughts maintain the problem?” but also,

“What neuroaffective conditions make these thoughts feel so compelling?”

Mind, Body, and the Foundations of Change

Many people enter psychotherapy believing that their emotional difficulties exist primarily “in the mind.” From a NeuroAffective-CBT perspective, this understanding is incomplete.

Mind and body form a single regulatory system. Thoughts influence physiology. Physiology influences affect. Affect shapes interpretation. Interpretation influences subsequent physiological responding.

Each component continuously influences the others within an ongoing cycle of prediction and regulation (Barrett, 2017; Damasio, 1999; Friston, 2010).

For this reason, NA-CBT integrates TED (Tiredโ€“Exerciseโ€“Diet) as a core stabilisation framework within psychotherapy (Mirea, 2023, 2025a, 2025b).

TED is not presented as a lifestyle programme or a substitute for psychological therapy. Nor does the NA-CBT therapist assume the role of a dietitian, physician, physiotherapist, or exercise professional. Instead, TED provides a psychologically informed framework through which clinicians explore how sleep, movement, nutrition, energy regulation, and everyday physiological functioning influence emotional experience and psychological flexibility. Where appropriate, clients are supported to access other healthcare professionals with specialist expertise in these areas.

This distinction is important. NeuroAffective-CBT is not practising medicine, nor is it reducing psychotherapy to lifestyle advice. Rather, it recognises that psychotherapy takes place within a living nervous system. Understanding how physiological regulation interacts with emotional processing enables the therapist to formulate distress more comprehensively and to collaborate with clients in reducing factors that unnecessarily increase neuroaffective load.

For Sophie, this became an essential component of therapy. Rather than viewing chronic fatigue, menopausal changes, insomnia, reduced physical activity, and nutritional habits as separate concerns to be addressed elsewhere, they became integrated into the psychological formulation. Together they provided important clues regarding the conditions under which shame intensified, emotional flexibility diminished, and appearance concerns became increasingly dominant.

Consequently, therapy frequently returned to one practical question:

What might be maintaining your neuroaffective load, and what might help reduce it?

This question gradually became the organising principle of treatment.

Rather than functioning as a checklist, it encouraged collaborative curiosity. It also translated naturally into collaborative goal setting. Together, therapist and Sophie began distinguishing between behaviours that appeared to maintain neuroaffective load and those that helped reduce neuroaffective load.

Visually, this was represented using two interconnected formulations.

The first resembled the familiar CBT vicious cycle, illustrating how poor sleep, inactivity, shame, social withdrawal, mirror checking, self-criticism, and avoidance interacted to perpetuate neuroaffective load.

Alongside this, therapist and client gradually constructed what Sophie came to call her virtuous flower. Each petal represented a small but meaningful influence that helped restore regulation: improved sleep routines, gentle movement, stretching, regular meals, meaningful social connection, compassionate self-reflection, behavioural experiments, and valued activity. No single intervention transformed her wellbeing. Collectively, however, they gradually altered the physiological and emotional context within which change became possible.

This visual distinction proved particularly helpful because it extended familiar CBT formulation without replacing it. Sophie immediately recognised its structure while simultaneously appreciating that the therapeutic focus had broadened beyond cognition alone.

The Bodyโ€“Brainโ€“Affect Triangle

Central to NeuroAffective-CBT is the Bodyโ€“Brainโ€“Affect Triangle, a formulation that conceptualises psychological functioning as a continuously interacting regulatory system rather than a sequence of isolated psychological events. Drawing upon affective neuroscience, predictive processing, and embodied cognition, the triangle proposes that physiological regulation, predictive brain processes, and primary affective systems are engaged in a constant reciprocal dialogue (Panksepp, 1998; Damasio, 1999; Friston, 2010; Barrett, 2017; LeDoux, 2015).

Within this model, none of the three components operates independently. A change within one corner of the triangle inevitably influences the others, often before conscious awareness emerges.

Body (Physiology)

The body provides the biological context within which psychological experience unfolds. Sleep, movement, nutrition, hormonal functioning, autonomic regulation, metabolic stability, chronic pain, illness, and fatigue all influence the nervous system’s capacity to regulate emotional experience.

From this perspective, physiology is not simply a background variable. It is an active participant in emotional life.

When physiological regulation becomes compromised through chronic sleep disruption, hormonal transition, nutritional imbalance, prolonged inactivity, or persistent stress, the nervous system becomes increasingly sensitive to perceived threat. Emotional reactions occur more readily, remain active for longer, and become progressively more difficult to regulate.

Brain (Prediction and Interpretation)

Within NeuroAffective-CBT, the brain is understood primarily as a predictive organ whose central evolutionary function is protection rather than objective perception (Friston, 2010; Barrett, 2017).

Long before conscious reasoning begins, the brain is continuously asking:

“Am I safe?”

“What is about to happen?”

“What should I prepare for?”

“How bad could this become?”

These predictions are shaped not only by conscious beliefs and interpretations but also by bodily sensations, previous emotional learning, autobiographical memory, attachment experiences, and current physiological state.

Consequently, individuals rarely respond to the world exactly as it is.

They respond to the brain’s best prediction of what is about to happen.

When physiology becomes dysregulated, these predictive systems become increasingly threat-sensitive. Neutral situations are more easily interpreted as dangerous. Ambiguous facial expressions appear rejecting. Minor imperfections become overwhelming evidence of failure. Shame becomes more readily activated and more difficult to regulate.

Affect (Primary Emotional Systems)

Affect represents the fast, evolutionarily conserved emotional systems that organise survival long before reflective thinking becomes possible (Panksepp, 1998; LeDoux, 2015).

Fear. Shame. Disgust. Anger. Relief.

These emotional systems rapidly orient attention towards information relevant to survival and social belonging. Only afterwards does cognition begin constructing explanations for what has already been felt.

Within NeuroAffective-CBT, cognition therefore remains critically important, but it is understood as the meaning-making layer built upon ongoing physiological and affective activity. Emotions are not simply generated by thoughts, nor are thoughts merely reactions to emotions. Each continuously shapes the other within an integrated regulatory system.

Differentiating Affect from Interpretation

One of the central therapeutic aims of NeuroAffective-CBT is helping clients distinguish between raw affect and interpretation.

Raw affect refers to the body’s immediate emotional signalโ€”fear, shame, sadness, anger, or reliefโ€”generated rapidly in response to internal or external cues.

Interpretation refers to the meaning subsequently assigned to those emotional signals through prediction, memory, beliefs, and conscious reflection (Barrett, 2017; Damasio, 1999).

When affect and interpretation become fused, emotional experiences begin to feel absolute.

“I feel ashamed” gradually becomes “I am shameful.”

“I feel afraid” becomes “I am unsafe.”

“I feel unattractive” becomes “I am fundamentally defective.”

Helping Sophie recognise this distinction became transformative. She gradually learned that the intensity of her emotional experience did not necessarily provide accurate information about objective reality. Instead, emotions increasingly became understood as important signals requiring curiosity rather than unquestioning acceptance.

Therapy repeatedly slowed these moments by returning to a more fundamental question:

What is your body signalling right now?

followed by..

Is your brain interpreting that signal in a way that accurately reflects the present?

These questions gradually interrupted the automatic fusion of affect and identity that had characterised Sophie’s experience for many years.

Therapeutic Process

The therapeutic process unfolded over approximately twelve months through weekly outpatient sessions. Although therapy retained the collaborative structure characteristic of Cognitive Behavioural Therapy, the emphasis gradually shifted from challenging isolated cognitions towards understanding the broader neuroaffective conditions within which those cognitions emerged.

From the outset, formulation became a collaborative process of curiosity rather than explanation. Rather than seeking a single underlying cause for Sophie’s distress, therapy explored how developmental experiences, current relationships, physiological regulation, affective responses, autobiographical memory, and behavioural patterns interacted to maintain her psychological difficulties.

Sophie’s previous CBT had equipped her with valuable cognitive skills. These were not discarded or replaced. Instead, they were revisited within a broader formulation that recognised why accessing these skills had become increasingly difficult under conditions of elevated neuroaffective load.

Behavioural experiments therefore remained central to therapy, but their purpose subtly expanded.

Rather than asking only, “What evidence supports this belief?” therapy increasingly asked,

“What happens to your emotional experience when your nervous system is more regulated?”

And “How does reducing neuroaffective load influence your ability to think differently?”

This shift was particularly evident when addressing mirror checking, avoidance, and appearance-focused behaviours.

Previously, behavioural experiments had focused primarily on testing catastrophic beliefs concerning Sophie’s appearance.

Within NA-CBT, these experiments continued, but they were carefully timed to coincide with periods of improved physiological regulation whenever possible. Sessions frequently explored the relationship between sleep quality, physical activity, emotional intensity, and the outcomes of behavioural experiments.

Over time, Sophie herself began noticing an important pattern. On days following adequate sleep, regular movement, and greater physiological stability, behavioural experiments felt challenging but manageable. Following several nights of poor sleep or heightened emotional exhaustion, identical experiments often felt overwhelming. This observation reinforced one of the central propositions of NA-CBT:

Psychological flexibility is not determined solely by cognitive skill. It is profoundly influenced by the physiological and affective conditions within which those skills are required.

Pause for Curiosity

Perhaps therapy becomes most effective not when clients think differently first…

…but when the conditions exist that allow different thinking to become possible.

NeuroAffective Narrative Reconsolidation (NNR)

As Sophie’s neuroaffective load gradually reduced, a notable shift began to emerge within therapy. She did not simply experience fewer distressing thoughts or engage in fewer appearance-related safety behaviours. Rather, she began relating to herself differently.

This change was subtle at first. Memories that had previously felt emotionally overwhelming became easier to approach. Shame remained present but no longer felt all-encompassing. Situations that once automatically confirmed long-held beliefs of defectiveness began to acquire alternative meanings.

Importantly, these changes did not arise through repeated attempts to replace “irrational thoughts” with more rational alternatives alone. Instead, they appeared to emerge as Sophie’s nervous system became increasingly able to tolerate emotional experience without immediately defaulting to threat-based prediction.

One memory proved particularly significant.

Throughout therapy, Sophie repeatedly returned to the childhood incident in which she had been accused of stealing after her cousin concealed an item in a shop. For many years she had experienced this memory not simply as an unfortunate childhood event but as compelling evidence that other people instinctively saw her as fundamentally bad, suspicious, or unworthy.

Earlier in life she had attempted to challenge this conclusion intellectually. She understood that the accusation had been unfair and recognised that many people would interpret the situation differently.

Yet this cognitive understanding had done little to alter the emotional meaning carried by the memory. Within NA-CBT, the therapeutic task therefore became different.

Rather than attempting to dispute the factual accuracy of the event, therapy sought to understand how its emotional significance had become organised within Sophie’s broader neuroaffective system.

The memory was no longer viewed in isolation. It became connected to a much wider developmental narrative. Repeated experiences in which beauty appeared to determine acceptance. The gradual belief that being attractive was necessary to deserve love. The experience of becoming increasingly invisible within important relationships. The emotional impact of repeated cosmetic procedures that left her feeling more flawed rather than less. The grief associated with childlessness. The loneliness she experienced within her marriage. The loss of work and identity. The exhaustion associated with chronic insomnia and menopause.

Together, these experiences formed an interconnected autobiographical narrative organised around a central expectation: “There is something fundamentally wrong with me.”

Within NeuroAffective-CBT, this process is conceptualised as NeuroAffective Narrative Reconsolidation (NNR).

NNR describes the gradual revision of emotionally organised autobiographical narratives through repeated experiences of physiological regulation, emotional safety, cognitive flexibility, and corrective interpersonal experience. Rather than focusing solely on changing individual beliefs, NNR seeks to reorganise the broader narrative structures through which people understand themselves, others, and the world. This understanding is consistent with contemporary theories of memory reconsolidation and emotional learning, which suggest that previously established emotional meanings remain open to revision when reactivated under conditions that permit new learning (Lane et al., 2015; Brewin, 2014; Arntz, 2012).

For Sophie, this process unfolded gradually rather than dramatically.

There was no single transformative session. Instead, countless small moments accumulated. She noticed herself remaining on camera for slightly longer during online meetings. She accepted invitations that she would previously have declined. She looked in the mirror without immediately searching for defects. She found herself walking outside without feeling compelled to hide behind sunglasses or heavy make-up. Most importantly, she became increasingly able to experience shame without allowing it to define her identity.

One session illustrated this particularly clearly. While discussing the childhood shop incident, Sophie paused and quietly said,

“I think I spent most of my life trying to prove that they were wrong.” ..“Maybe I don’t need to prove anything anymore.”

This moment was not interpreted as the disappearance of shame. Nor did it represent the complete resolution of Body Dysmorphic Disorder. Instead, it reflected a profound reorganisation of meaning. The memory remained but its emotional authority had changed. Rather than functioning as unquestioned evidence of personal defectiveness, it became recognised as one painful chapter within a much larger life story.

From that point onwards, the memory could be held with compassion rather than certainty.

The Emergence of the Integrated-Self

Throughout therapy, the central therapeutic aim was never to eliminate unwanted emotions or construct an idealised version of the self.

Instead, NA-CBT sought to create the neuroaffective conditions in which Sophie’s Integrated-Self could emerge more consistently.

The Integrated Self does not represent perfection, permanent happiness, or the absence of vulnerability.

Rather, it reflects an increasingly coherent experience of identity in which physiology, affect, cognition, behaviour, autobiographical memory, and interpersonal experience become more harmoniously aligned.

Within this state, emotional experiences remain meaningful without becoming overwhelming.

Thoughts remain influential without becoming absolute. The body becomes a source of information rather than threat. Relationships become opportunities for connection rather than continual evaluation. Most importantly, identity becomes less organised around protection and more organised around authenticity.

This distinction proved fundamental. Early in therapy, Sophie experienced herself almost entirely through the lens of shame. Later, she increasingly recognised shame as one emotional experience among many. The difference was profound as she no longer experienced what she felt as who she was. Instead, emotions became experiences that could be observed, understood, and responded to with increasing flexibility.

As the Integrated-Self became more accessible, behavioural change emerged naturally rather than through constant effort. Mirror checking reduced,  avoidance diminished and social engagement gradually increased. Self-care became motivated less by fear of judgement and more by genuine compassion for herself. Perhaps most significantly, therapy no longer revolved around repairing a defective person.

Instead, it focused on creating the biological, psychological, and relational conditions that allowed an already existing, though previously obscured, sense of self to become increasingly available.

Pause for Curiosity

Perhaps psychological change is not always about becoming someone new.

Perhaps it is about reducing the neuroaffective conditions that prevent people from becoming who they have always had the capacity to be.

Discussion

Sophie’s therapeutic journey illustrates one of the central propositions of NeuroAffective-CBT: the recurrence of psychological symptoms does not necessarily indicate that previous therapy has been unsuccessful. Rather, it may reflect profound changes in the neuroaffective context within which previously acquired psychological skills are now expected to operate.

Although Sophie retained many of the cognitive insights developed during her previous course of CBT, years of accumulating physiological, relational, occupational, and emotional adversity had fundamentally altered the conditions under which these skills were required. Menopause, persistent insomnia, occupational loss, social isolation, repeated cosmetic procedures, prolonged litigation, and unresolved grief collectively increased her neuroaffective load, reducing psychological flexibility despite preserved cognitive understanding.

Rather than conceptualising this deterioration as therapeutic failure, NA-CBT understood it as evidence that cognition does not operate independently of physiology and affect. Cognitive restructuring, behavioural experiments, and exposure remain essential components of evidence-based treatment (Beck, 1976, 2021; Clark & Beck, 2010). However, the effectiveness of these interventions may be influenced by the physiological and affective state within which they occur.

This broader formulation complements established cognitive behavioural models of Body Dysmorphic Disorder, which emphasise dysfunctional appearance beliefs, selective attention, mirror checking, avoidance, reassurance seeking, and safety behaviours in maintaining distress (Veale, 2004; Veale & Neziroglu, 2010; Phillips, 2005; Wilhelm et al., 2013). Rather than replacing these well-established models, NeuroAffective-CBT seeks to extend them by incorporating physiological regulation, predictive processing, and affective neuroscience into psychological formulation.

From this perspective, body dysmorphic symptoms are understood not only as products of maladaptive cognition and behaviour but also as emerging within an integrated body-brain system continuously attempting to predict, interpret, and respond to potential threat (Friston, 2010; Barrett, 2017). The brain’s primary evolutionary task is not objective reasoning but anticipation in the service of protection. Consequently, alterations in physiological regulation may significantly influence the intensity, persistence, and credibility of appearance-related beliefs.

Central to this formulation is the concept of neuroaffective load (Mirea, 2018). Unlike broader notions of stress, neuroaffective load refers to the cumulative interaction between physiological dysregulation, affective activation, cognitive burden, interpersonal adversity, and environmental demands. Sophie’s presentation illustrated how multiple seemingly independent difficulties gradually converged to create conditions in which shame, self-criticism, and avoidance became increasingly dominant.

The introduction of the TED (Tiredโ€“Exerciseโ€“Diet) framework provided a practical means of addressing these physiological influences within psychotherapy (Mirea, 2023, 2025a, 2025b). Importantly, TED is not intended to replace specialist medical, nutritional, or exercise interventions. Rather, it offers psychologists a psychologically informed framework through which physiological regulation becomes part of collaborative formulation. Where clinically appropriate, clients may be supported to access relevant healthcare professionals while psychotherapy continues to address the emotional and cognitive implications of physiological dysregulation.

One of the distinguishing features of NA-CBT is its explicit rejection of a traditional mind-body dichotomy. Rather than viewing biological and psychological processes as separate domains, NA-CBT conceptualises emotional experience as emerging through continuous interactions between physiology, affect, cognition, autobiographical memory, and interpersonal relationships (Damasio, 1999; Barrett, 2017; Siegel, 2012). The Body-Brain-Affect Triangle offers one way of organising these interactions clinically, helping therapists and clients appreciate how changes in one component inevitably influence the others.

Another important contribution concerns the distinction between affect and interpretation. Throughout therapy, Sophie gradually learned to differentiate immediate emotional signals from the meanings subsequently assigned to them. This distinction allowed shame to become an emotional experience rather than a fixed identity. Increasingly, she recognised that intense emotional reactions were not necessarily accurate reflections of present reality but understandable responses generated within a nervous system organised around protection rather than objective perception (LeDoux, 2015; Panksepp, 1998).

These developments created the conditions for NeuroAffective Narrative Reconsolidation. Rather than focusing exclusively on modifying individual cognitions, therapy facilitated the gradual reorganisation of emotionally significant autobiographical narratives. Memories that had long functioned as unquestioned evidence of personal defectiveness became integrated into a broader, more compassionate life story. This process aligns conceptually with contemporary understandings of memory reconsolidation and emotional learning, suggesting that autobiographical narratives remain open to revision when reactivated under conditions of sufficient emotional safety and physiological regulation (Lane et al., 2015; Brewin, 2014; Arntz, 2012).

Perhaps most importantly, the therapeutic goal extended beyond symptom reduction. While reductions in appearance preoccupation, avoidance, and self-criticism were clinically meaningful, they were understood as consequences of a broader developmental process rather than endpoints in themselves. The overarching aim became the emergence of an Integrated-Self, a coherent experience of identity in which physiology, affect, cognition, autobiographical memory, behaviour, and relationships become increasingly aligned (Mirea, 2018).

Throughout treatment, one recurring question appeared to organise both formulation and intervention:

What might be maintaining your neuroaffective load, and what might help reduce it?

Although deceptively simple, this question repeatedly redirected attention away from self-blame and towards collaborative curiosity. It also proved highly transportable across therapeutic goals, helping distinguish behaviours that maintained neuroaffective load from those that gradually reduced it. In Sophie’s therapy, this distinction was represented visually through a traditional CBT vicious cycle alongside a complementary “virtuous flower”, illustrating the multiple pathways through which physiological regulation, valued action, behavioural flexibility, and compassionate self-care gradually supported psychological recovery.

Limitations

As a single case study, the present report cannot determine the efficacy of NeuroAffective-CBT or establish causal relationships between specific interventions and clinical outcomes. Improvements observed throughout therapy likely reflected the combined influence of multiple therapeutic, interpersonal, and contextual factors.

Accordingly, the present case should be viewed as an illustration of clinical formulation rather than evidence of treatment superiority. Future research should evaluate NA-CBT across a range of clinical presentations using controlled methodologies, examining both symptom outcomes and broader indicators of physiological regulation, emotional flexibility, identity integration, and quality of life.

Future Directions

Future developments within NeuroAffective-CBT should focus on systematic empirical evaluation of the model across anxiety disorders, obsessive-compulsive and related disorders, mood disorders, trauma-related presentations, and personality difficulties. In particular, research exploring interactions between physiological regulation, affective processing, and cognitive flexibility may further clarify the mechanisms through which neuroaffective load influences psychological functioning. Finally, future publications may expand the present work by exploring the theoretical foundations of NA-CBT in greater depth, alongside additional clinical illustrations across diverse diagnostic presentations.

Conclusion

This case study has presented NeuroAffective-CBT (NA-CBT) through the treatment of a woman with longstanding Body Dysmorphic Disorder whose difficulties evolved within the context of cumulative physiological, developmental, relational, and emotional adversity. Rather than conceptualising symptom recurrence as evidence of therapeutic failure, NA-CBT proposed that previously acquired psychological skills had become increasingly difficult to access because the neuroaffective conditions supporting their effective use had fundamentally changed.

Throughout therapy, formulation extended beyond cognition alone to consider the continuous interaction between physiology, affect, predictive brain processes, autobiographical memory, behaviour, and interpersonal experience. Concepts such as neuroaffective load, the TED (Tiredโ€“Exerciseโ€“Diet) framework, the Bodyโ€“Brainโ€“Affect Triangle, and NeuroAffective Narrative Reconsolidation provided an integrated framework through which Sophie’s presentation became increasingly understandable and clinically meaningful.

Importantly, NA-CBT does not seek to replace established cognitive behavioural models. Instead, it builds upon the considerable strengths of contemporary CBT by incorporating developments from affective neuroscience, predictive processing, embodied cognition, attachment theory, and lifestyle medicine into psychological formulation and intervention (Beck, 2021; Barrett, 2017; Friston, 2010). In doing so, it offers clinicians an expanded framework for understanding how physiological regulation, emotional processing, and cognitive flexibility continuously influence one another.

Perhaps the most significant shift within therapy concerned its ultimate aim.

Rather than striving simply to reduce symptoms, challenge distorted cognitions, or eliminate distress, treatment sought to create the biological, psychological, and relational conditions in which Sophie’s Integrated-Self could emerge more consistently. As neuroaffective load gradually reduced, shame became less defining, autobiographical memories acquired new meaning, behavioural flexibility increased, and compassion gradually replaced self-protection as the organising principle of her relationship with herself.

At its heart, NeuroAffective-CBT invites clinicians to become curious. Curious about the relationship between body and mind. Curious about the interaction between physiology and cognition. Curious about how affect shapes prediction before conscious thought has emerged. Curious about the stories people carry about themselves and the neuroaffective conditions that allow those stories to evolve.

Clinical Reflections

This case illustrates how broadening formulation beyond cognition alone may enrich clinical understanding without abandoning the principles of Cognitive Behavioural Therapy. The concepts presented within NA-CBT are intended to complementโ€”not replaceโ€”existing evidence-based CBT models. Throughout treatment, curiosity functioned not merely as a therapeutic attitude but as an active clinical intervention, encouraging therapist and client to explore how physiology, affect, cognition, memory, and relationships continuously interacted.

For practising clinicians, the recurring questionโ€” What might be maintaining neuroaffective load, and what might help reduce it? โ€”may provide a simple yet clinically useful organising principle that readily translates into collaborative formulation, treatment planning, behavioural goals, and relapse prevention.

Disclaimer

This case study is intended solely for educational and professional discussion purposes. It does not constitute clinical guidance, diagnosis, or treatment recommendations. Therapeutic approaches described should be implemented only by appropriately trained professionals within their scope of competence and adapted to the individual needs of each client. Readers are encouraged to consult relevant clinical guidelines, current evidence, and professional supervision when applying the concepts presented within this paper.

The image used in this article is an illustrative image only. This image is AI-generated and does not depict the actual client. It has been created solely to reflect the themes of this anonymised case study.

Ethics and Anonymisation Statement

All identifying client information has been altered to protect anonymity. The case has been substantially anonymised, and contextual details have been modified where necessary to minimise the possibility of identification while preserving the clinical relevance of the formulation. Informed consent was obtained for the use of anonymised clinical material for educational and dissemination purposes.

References

American Psychiatric Association. (2022). Diagnostic and statistical manual of mental disorders (5th ed., text rev.; DSM-5-TR). American Psychiatric Association.

Arntz, A. (2012). Imagery rescripting as a therapeutic technique: Review of clinical trials, basic studies, and research agenda. Journal of Experimental Psychopathology, 3(2), 189โ€“208. https://doi.org/10.5127/jep.024211

Barrett, L. F. (2017). How emotions are made: The secret life of the brain. Houghton Mifflin Harcourt.

Barrett, L. F., & Simmons, W. K. (2015). Interoceptive predictions in the brain. Nature Reviews Neuroscience, 16(7), 419โ€“429. https://doi.org/10.1038/nrn3950

Beck, A. T. (1976). Cognitive therapy and the emotional disorders. International Universities Press.

Beck, J. S. (2021). Cognitive behavior therapy: Basics and beyond (3rd ed.). Guilford Press.

Brewin, C. R. (2014). Episodic memory, perceptual memory, and their interaction: Foundations for a theory of posttraumatic stress disorder. Psychological Bulletin, 140(1), 69โ€“97. https://doi.org/10.1037/a0033722

Clark, A. (2013). Whatever next? Predictive brains, situated agents, and the future of cognitive science. Behavioral and Brain Sciences, 36(3), 181โ€“204. https://doi.org/10.1017/S0140525X12000477

Clark, D. A., & Beck, A. T. (2010). Cognitive therapy of anxiety disorders: Science and practice. Guilford Press.

Damasio, A. (1999). The feeling of what happens: Body and emotion in the making of consciousness. Harcourt Brace.

Elsey, J. W. B., Van Ast, V. A., & Kindt, M. (2018). Human memory reconsolidation: A guiding framework and critical review. Neuroscience & Biobehavioral Reviews, 89, 1โ€“19. https://doi.org/10.1016/j.neubiorev.2018.03.008

Firth, J., Solmi, M., Wootton, R. E., et al. (2020). A meta-review of lifestyle psychiatry: The role of exercise, smoking, diet and sleep in the prevention and treatment of mental disorders. World Psychiatry, 19(3), 360โ€“380. https://doi.org/10.1002/wps.20773

Friston, K. (2010). The free-energy principle: A unified brain theory? Nature Reviews Neuroscience, 11(2), 127โ€“138. https://doi.org/10.1038/nrn2787

Hayes, S. C., Hofmann, S. G., & Ciarrochi, J. (2022). A process-based approach to psychological diagnosis and treatment. Current Directions in Psychological Science, 31(4), 343โ€“350. https://doi.org/10.1177/09637214221089356

Hayes, S. C., Strosahl, K. D., & Wilson, K. G. (2012). Acceptance and commitment therapy: The process and practice of mindful change (2nd ed.). Guilford Press.

Hofmann, S. G., & Hayes, S. C. (2019). The future of intervention science: Process-based therapy. Clinical Psychological Science, 7(1), 37โ€“50. https://doi.org/10.1177/2167702618772296

Hohwy, J. (2020). New directions in predictive processing. Mind & Language, 35(2), 209โ€“223. https://doi.org/10.1111/mila.12281

Khalsa, S. S., Adolphs, R., Cameron, O. G., et al. (2018). Interoception and mental health: A roadmap. Biological Psychiatry: Cognitive Neuroscience and Neuroimaging, 3(6), 501โ€“513. https://doi.org/10.1016/j.bpsc.2017.12.004

Lane, R. D., Ryan, L., Nadel, L., & Greenberg, L. S. (2015). Memory reconsolidation, emotional arousal, and the process of change in psychotherapy: New insights from brain science. Behavioral and Brain Sciences, 38, e1. https://doi.org/10.1017/S0140525X14000041

LeDoux, J. E. (2015). Anxious: Using the brain to understand and treat fear and anxiety. Viking.

Marx, W., Moseley, G., Berk, M., & Jacka, F. (2017). Nutritional psychiatry: The present state of the evidence. Proceedings of the Nutrition Society, 76(4), 427โ€“436. https://doi.org/10.1017/S0029665117002026

Mirea, D. (2018, October 19). The underlayers of NeuroAffective-CBTยฎ. NeuroAffective-CBTยฎ. https://neuroaffectivecbt.com/2018/10/19/the-underlayers-of-neuroaffective-cbt/

Mirea, D. (2023, July 18). Tired, Exercise and Diet your way out of trouble: TED’s your best friend. NeuroAffective-CBTยฎ. https://neuroaffectivecbt.com/2023/07/18/teds-your-best-friend/

Mirea, D. (2025, December 10). TED in NeuroAffective-CBTยฎ: An applied self-regulation framework for enhancing emotional well-being through sleep, movement, and nutrition. NeuroAffective-CBTยฎ. https://neuroaffectivecbt.com/2025/12/10/ted-in-neuroaffective-cbt-an-applied-self-regulation-framework-for-enhancing-emotional-well-being-through-sleep-movement-and-nutrition/

Mirea, D. (2025, December 17). The use of lifestyle interventions in psychotherapy. NeuroAffective-CBTยฎ. https://neuroaffectivecbt.com/2025/12/17/the-use-of-lifestyle-interventions-in-psychotherapy/

Niedenthal, P. M. (2007). Embodying emotion. Science, 316(5827), 1002โ€“1005. https://doi.org/10.1126/science.1136930

Panksepp, J. (1998). Affective neuroscience: The foundations of human and animal emotions. Oxford University Press.

Pessoa, L. (2017). A network model of the emotional brain. Trends in Cognitive Sciences, 21(5), 357โ€“371. https://doi.org/10.1016/j.tics.2017.03.002

Phillips, K. A. (2005). The broken mirror: Understanding and treating body dysmorphic disorder (Rev. ed.). Oxford University Press.

Phillips, K. A., Didie, E. R., Feusner, J., & Wilhelm, S. (2008). Body dysmorphic disorder: Treating an underrecognized disorder. American Journal of Psychiatry, 165(9), 1111โ€“1118. https://doi.org/10.1176/appi.ajp.2008.08040500

Seth, A. K., & Friston, K. J. (2016). Active interoceptive inference and the emotional brain. Philosophical Transactions of the Royal Society B: Biological Sciences, 371(1708), 20160007. https://doi.org/10.1098/rstb.2016.0007

Siegel, D. J. (2012). The developing mind: How relationships and the brain interact to shape who we are (2nd ed.). Guilford Press.

Veale, D. (2004). Advances in a cognitive behavioural model of body dysmorphic disorder. Body Image, 1(1), 113โ€“125. https://doi.org/10.1016/S1740-1445(03)00009-3

Veale, D., & Neziroglu, F. (2010). Body dysmorphic disorder: A treatment manual. Wiley-Blackwell.

Wilhelm, S., Phillips, K. A., & Steketee, G. (2013). Cognitive behavioral therapy for body dysmorphic disorder: A treatment manual. Guilford Press.

The Transdiagnostic Application of NeuroAffective-CBT: A Case Study of Chronic Stress and Burnout

Dr Marco Cortez (January, 2026)
|The NeuroAffective-CBTยฎ Journal |ย 


Abstract

This case report describes the application of NeuroAffective-CBTยฎ (NA-CBTยฎ) with a single working mother, Susan, presenting with chronic stress, shame-organised self-criticism, affective instability, and fluctuating anxiety and low mood. The article may be relevant for clinicians working with clients who โ€˜understand their patternsโ€™ cognitively but struggle to sustain regulation under stress.

Although Susan demonstrated motivation and cognitive insight consistent with traditional CBT, therapeutic progress was initially constrained by physiological dysregulation and entrenched affective patterns. NA-CBT was therefore selected for its neurobiologically informed, transdiagnostic framework (Mirea, 2018). Central to the intervention were the Pendulum-Effect formulation and the TED (Tiredโ€“Exerciseโ€“Diet) module, which supported affect regulation and consolidation of learning. Outcomes indicate improvements in emotional stability, behavioural consistency, and self-compassion. The case highlights both the clinical utility and the limitations of NA-CBT within a time-limited therapeutic context characterised by ongoing psychosocial stress.

This case offers a clinically grounded illustration of how an affect-regulation-first, transdiagnostic approach may be applied to chronic stress and burnout-adjacent presentations, where cognitive insight is present but sustained behavioural change is constrained by physiological and shame-organised responding.

Keywords: NeuroAffective-CBT; affect regulation; shame; behavioural experiments; Pendulum Effect; TED model; psychological flexibility; embodied cognition; transdiagnostic psychotherapy; lifestyle interventions; affective neuroscience; case study


Introduction

Cognitive Behavioural Therapy (CBT) is an established evidence-based treatment for anxiety and depressive disorders (Beck, 1976; Hofmann et al., 2012). However, CBT may be less effective for clients whose difficulties are dominated by chronic shame, affective dysregulation, and embodied stress responses, rather than by explicit cognitive distortions alone (Gilbert, 2010; Panksepp, 2011).

NeuroAffective-CBT extends traditional CBT by explicitly integrating findings from affective neuroscience, attachment theory, and psychophysiology (Mirea, 2018). NA-CBT proposes that durable cognitive and behavioural change depends on the regulation of subcortical affective systems and bodily states, particularly in individuals experiencing persistent emotional volatility and shame-organised responding (Mirea, 2018; Schore, 2012).

This paper presents a detailed, practice-based case study illustrating the application of NA-CBT with a single working mother whose presenting difficulties were coherently conceptualised using the Pendulum-Effect formulation. As a single-case report, the aim is not to necessarily establish efficacy but rather to provide a clinically grounded illustration of how affect-regulation-focused interventions may support therapeutic engagement and change in complex, non-diagnostic presentations.


Client Information

The client, referred to as Susan, is a 42-year-old single mother of two children, one of whom has significant additional needs. She works part-time in a professional role and experiences ongoing financial strain, chronic fatigue, and emotional overwhelm. Susan self-referred for therapy due to persistent anxiety, low mood, bodily tension, and difficulty initiating and sustaining work-related tasks.

She reported no previous experience of psychological therapy and denied suicidal ideation or risk to others. Her difficulties were longstanding and had intensified in the context of prolonged caregiving demands and occupational disruption. Although Susan did not meet formal criteria for occupational burnout, her presentation reflected core burnout features including emotional exhaustion, reduced task initiation, and shame-organised overcompensation.


Presenting Difficulties

Susan reported the following difficulties:

  • persistent tiredness and bodily pain
  • anxiety related to finances and perceived competence
  • fluctuating mood states rather than sustained depression
  • strong self-criticism and pervasive shame
  • cycles of overworking followed by avoidance and emotional shutdown

Despite insight into her thinking patterns, Susan struggled to implement consistent behavioural change. Emotional reactions were often rapid, intense, and disproportionate to present-day triggers, suggesting affective processes operating beneath conscious cognition and outside deliberate control (LeDoux, 1996; Mirea, 2025).


Rationale for NeuroAffective-CBTยฎ

Although Susan met many criteria for standard CBT suitability (Safran et al., 1993), her difficulties were better explained by affective and physiological dysregulation rather than faulty beliefs alone or a discrete diagnostic category. Instead, her presentation reflected a cluster of symptoms common across common mental health presentations, organised around shame-dominant affective responding and chronic stress exposure.

NA-CBT was therefore selected to:

  1. Address emotional reactivity at a neuroaffective level
  2. Reduce shame-organised responding
  3. Stabilise physiological states that interfered with learning
  4. Support belief change through emotionally salient experience

When affective systems are chronically activated, cognitive techniques may inadvertently intensify self-criticism or compensatory over-effort (Mirea, 2018). This pattern was observed during the early phase of Susanโ€™s therapy, further supporting the need for a regulation-first approach.


Pendulum-Effect Formulation

A core feature of NA-CBT is the Pendulum-Effect formulation, which conceptualises psychological distress as oscillation between opposing coping strategies driven by unresolved core affect (Mirea, 2018). These oscillations occur largely outside conscious awareness and function to maintain dominant affects such as shame, guilt, fear, or self-criticism.

In Susanโ€™s case, this oscillation was pronounced. She alternated between procrastination (intentional delay) and avoidance (withdrawal) until tasks became unavoidable. These phases were then followed by periods of overcompensation marked by excessive responsibility-taking, urgency, and perfectionistic standards. Such efforts were typically unsustainable and culminated in collapse, accompanied by intensified self-blame, hopelessness, and emotional withdrawal (or capitulation). A similar pendulum pattern was observed in her eating behaviour, in which episodes of overeating (overcompensation) were followed by periods of restriction (avoidance) and harsh self-reproach (capitulation), further reinforcing shame and loss of self-trust.

Within the Pendulum-Effect formulation, these patterns reflect the complex and dynamic oscillation between avoidant, overcompensatory, and capitulating strategies rather than a linear sequence of behaviours. Shame-based core affect was conceptualised as occupying the functional centre of the system, with oscillating strategies serving as complex self-sabotage, to temporarily manage distress while simultaneously reinforcing negative self-evaluative beliefs such as โ€œI am inadequateโ€ or โ€œI am failing.โ€ Importantly, these strategies were understood not as pathology, but as historically adaptive survival responses shaped by cumulative relational, developmental, and contextual stress (Mirea, 2018; Porges, 2011).

Therapeutic work therefore focused on reducing the amplitude of oscillation rather than eliminating emotional experience, while gradually introducing adaptive coping strategies aligned with authentic personal values that promote psychological health and functional independence. Intervention emphasised affect regulation, increased awareness of pendulum dynamics, and the cultivation of compassionate choice at moments of activation, thereby supporting greater stability and flexibility in emotional and behavioural responding.

Pendulum Poles Identified

Susan oscillated between the following coping poles:

  • Overcompensation: excessive responsibility, perfectionism, overworking
  • Avoidance: procrastination, emotional numbing, withdrawal
  • Capitulation: resignation, hopelessness, self-blame

Conceptually, this can be represented as:

These responses were understood not as pathology, but as adaptive survival strategies shaped by past and current relational stress (Mirea, 2018; Porges, 2011). An early narrative contributing to Susanโ€™s internalised shame involved comparison with an idealised maternal figure perceived as coping effortlessly, reinforcing beliefs of inadequacy and shame-based self-evaluation.

Therapeutic work focused on reducing pendulum amplitude by strengthening affect regulation, increasing awareness of oscillation patterns, and cultivating compassionate choice, rather than attempting to eliminate emotional experience altogether.


Description of the NA-CBTยฎ Intervention

Module 1: Engagement and Affective Assessment

Assessment emphasised collaborative formulation, mapping Susanโ€™s pendulum patterns, and identifying bodily markers associated with distinct affective states. Emotional responses were normalised as nervous-system reactions shaped by experience and rooted in the brainโ€™s predictive regulatory processes, whose primary function is to maintain physiological survival. This framing supported affect tolerance and therapeutic engagement (Schore, 2012; Mirea, 2018).

Within NA-CBTโ€“informed practice, early sessions are understood as a critical opportunity to establish safety, trust, and a robust therapeutic alliance oriented toward authentic living rather than a life organised around internalised shame states. During this phase, the therapistโ€™s role involves providing guidance and psychoeducation alongside compassion and active listening, thereby supporting engagement while modelling a regulated, responsive, and relationally attuned stance.


Module 2: Psychoeducation

NA-CBTยฎ can appear to be a phased treatment; however, clinical practice demonstrates that modules are applied flexibly and intersect dynamically according to formulation and regulatory needs (Mirea, 2018). Psychoeducation was therefore embedded throughout therapy rather than delivered as a discrete phase.

This approach is consistent with evidence that learning and meaning-making enhance neuroplasticity and psychological flexibility, now recognised as a transdiagnostic protective factor (Kolb, 1984; Davidson and McEwen, 2012; Kashdan and Rottenberg, 2010).

Susan was introduced to:

โ€ข the role of pendulum-effect oscillating strategies in reinforcing shame
โ€ข distinctions between core affect and cognitive appraisal
โ€ข the regulatory function of emotions such as shame (signalling perceived social threat and guiding protective behaviour)
โ€ข the impact of physiological stress on emotional intensity
โ€ข the role of lifestyle stability in moderating affective reactivity

This psychoeducation reduced self-blame and strengthened engagement, consistent with NA-CBTยฎโ€™s emphasis on emotional literacy (Mirea, 2018).


Module 3: TED โ€“ Tired, Exercise, Diet

The TED module was implemented as a foundational affect-regulation strategy rather than as adjunctive lifestyle advice (Mirea, 2023; Mirea, 2025). Within NA-CBTโ€“informed practice, TED targets background physiological instability known to amplify emotional reactivity and undermine cognitive and behavioural learning (Damasio, 1999).

Behavioural changes and corresponding behavioural experiments were introduced across all three TED domains. Within the Tired domain, interventions prioritised sleep regularity and pacing rather than sleep optimisation. Within the Exercise domain, distinctions were made between incidental activity and intentional regulating movement such as yoga or purposeful walking, which were more consistently associated with reductions in affective volatility. Within the Diet domain, psychoeducation addressed the short-term stimulating and longer-term destabilising effects of high sugar intake, reframing reliance on sugar as a stress-driven coping strategy rather than a sustainable energy source.

Susan observed that spikes in self-criticism and shame reliably followed prolonged sedentary days characterised by binge eating and alcohol use. Within the Pendulum-Effect formulation, these patterns were understood as oscillations between overcompensation, avoidance, and capitulation, functioning as a recurring self-reinforcing cycle driven by unresolved shame-based affect.

In response, brief โ€œexercise snacksโ€ were introduced not as fitness goals, but as identity-repair behaviours (e.g., โ€œI am someone who cares for my body and nervous systemโ€).

Susan also noted heightened fear and emotional reactivity following poor sleep, skipped meals, and excessive caffeine intake. Using the TED self-check, these affective shifts were re-contextualised as substantially physiological rather than as evidence of personal failure. This reframing reduced shame and overwhelm, allowing subsequent exposure-based and cognitive interventions to proceed with greater tolerance and engagement.

Where relevant, Susan was encouraged to seek medical or dietetic input to support nutritional adequacy and metabolic stability, consistent with TEDโ€™s positioning as complementary to, rather than a replacement for, healthcare input (Mirea, 2025). Following consultation with her general practitioner, routine blood investigations identified physiological factors (e.g., iron and vitamin D insufficiency) considered contributory to fatigue and fluctuating energy levels. Addressing these factors further supported affect regulation and behavioural engagement within therapy without displacing psychological intervention.

As emphasised by Mirea (2025), within NA-CBT informed practice, lifestyle regulation, affective formulation, exposure, and identity repair are conceptualised as interlocking components of a single regulatory system rather than as parallel or competing therapeutic tracks.


Module 4: The Integrated Self

Within NA-CBT, this phase of therapy focuses on working with specific, emotionally salient (โ€œhotโ€) memories that activate cascades of negative affect and self-defeating behavioural responses. Attending to discrete memory fragments is often more effective than attempting to process broad or global relational narratives, which may become cognitively assimilated over time into fear, guilt or shame-based conclusions that are resistant to change (Erten MM, 2018; Mirea, 2018).

Clients were supported to maintain present-moment physiological awareness while narrating specific memories in a contained and titrated manner. This process enabled the gradual re-appraisal of trauma-linked affect as tolerable bodily sensation rather than overwhelming threat. Over time, emotional fluctuations were experienced as manageable variations in internal state, supporting acceptance and the integration of a more adaptive and cohesive sense of self (Gilbert, 2010; Mirea, 2018).


Module 5: Coping Skills-Enhanced Behavioural Experiments

Although behavioural experiments are described as a discrete module within NA-CBT, the creation of new lived experience is emphasised throughout therapy, reflecting the modelโ€™s use of intersecting and flexible modules rather than a linear sequence (Mirea, 2018). Behavioural experimentation was therefore conceptualised as an ongoing learning process supporting affect regulation, belief revision, and identity repair.

Across therapy, experiments were designed to test emotional predictions alongside cognitions, consistent with experiential learning theory (Kolb, 1984; Engelkamp, 1998) and the principle that belief change occurs primarily through emotionally meaningful action (Chadwick, Birchwood and Trower, 1996).


Module 6: Consolidation and Ending

Ending focused on recognising early pendulum swings, applying TED independently, and maintaining ongoing affect awareness. Relapse prevention was framed as a process of continued regulation rather than symptom elimination (Mirea, 2018). TED was positioned as a long-term inner compass, with setbacks reframed as signals of nervous-system strain rather than personal failure.


Outcomes

Therapy progressed steadily across 18 sessions. The initial six sessions focused on assessment, collaborative formulation, psychoeducation, and the introduction of the TED framework, with particular emphasis on affect regulation and lifestyle stabilisation.

The subsequent nine sessions facilitated early narrative processing and the development of acceptance through self-compassion. These sessions also incorporated behavioural and social experiments aimed at promoting new learning, strengthening adaptive coping, and gradually modifying overcompensatory, avoidant, and capitulating coping strategies. Such patterns were frequently organised around shame-based conditional assumptions, for example: โ€œIf I do not sacrifice myself and meet othersโ€™ demands perfectly, I am worthless,โ€ accompanied by implicit affective experiences of shame and guilt.

The final three sessions were conducted on a monthly basis and focused on consolidating therapeutic gains, strengthening relapse-prevention strategies, and supporting the clientโ€™s increasing capacity for autonomous self-regulation.

By the end of therapy, Susan demonstrated:

  • Adoption of a more regulated lifestyle informed by TED principles
  • Reduced affective volatility and improved emotional self-regulation
  • Increased tolerance of uncertainty and distress
  • Greater behavioural consistency across work and caregiving contexts
  • Development of a more compassionate and flexible self-narrative

Although significant external stressors persisted, Susan experienced emotional responses with greater awareness, reduced escalation, and increased capacity for regulation, indicating meaningful consolidation of therapeutic learning.

Symptomatic progress was monitored using the Hospital Anxiety and Depression Scale (HADS) and CORE-32, administered at assessment, session nine, and session eighteen. Improvements were observed across key domains of concern, including chronic stress, day-to-day functioning, shame-organised self-criticism, affective instability, anxiety, and low mood.


Learning Outcomes

This case demonstrates that:

  1. โ€œAffect regulation may be a prerequisite for sustained cognitive and behavioural change.โ€
  2. โ€œThe Pendulum-Effect formulation offers a dynamic, non-pathologising framework for understanding oscillating coping patterns.โ€
  3. โ€œTED-based interventions can function as core therapeutic tools rather than adjunctive lifestyle advice.โ€
  4. โ€œBehavioural experiments are most effective when designed to be emotionally salient.โ€
  5. โ€œNA-CBT may be particularly well suited to presentations characterised by chronic stress, low self-esteem, and shame-organised responding.โ€

Critical Evaluation

Strengths

  • Integrates affective neuroscience, lifestyle regulation, and principles from nutritional psychiatry within an evidence-based CBT framework
  • Reduces self-blame through the normalisation of physiological and affective processes
  • Provides a coherent and non-pathologising framework for complex, non-diagnostic presentations

Limitations

  • Requires advanced therapist skill in affective attunement and regulation
  • Requires additional therapist knowledge drawn from domains that traditionally fall outside the core remit of psychotherapy, including nutrition, neuroscience, and exercise psychology
  • Some concepts may initially feel abstract or unfamiliar to clients
  • Time-limited therapy constrained the depth of narrative integration and longer-term consolidation

Clinical Reflexivity

With hindsight, earlier emphasis on TED-based stabilisation may have reduced initial pendulum oscillations more rapidly. Encouraging liaison with primary healthcare services, including general practitioner consultation and routine blood investigations, provided clinically useful contextual information that complemented psychological formulation and supported affect regulation.

This early physiological stabilisation facilitated increased engagement in self-care and self-compassion practices, which in turn enabled deeper therapeutic work with shame-laden narratives, including beliefs linking personal worth to constant performance and self-sacrifice.

Agenda management required ongoing sensitivity to balance therapeutic structure with respect for the clientโ€™s lived complexity, ensuring that therapeutic direction did not inadvertently replicate earlier experiences of invalidation or over-demand.


Conclusion

This case illustrates how NeuroAffective-CBT can extend traditional CBT by directly engaging the affective and physiological processes that organise psychological distress. Through the combined use of the Pendulum-Effect formulation and TED (Tiredโ€“Exerciseโ€“Diet), NA-CBT supported sustainable emotional and behavioural change within the context of ongoing psychosocial stress. Rather than functioning solely as a time-limited intervention, NA-CBT may be understood as a lifelong self-regulation framework, offering clients a practical internal compass for stabilising physiology first and thereby expanding freedom in how they think, feel, and act.

More broadly, this case reflects a growing movement within psychotherapy toward a deeper integration of mind and body. As neuroscience, psychosomatic medicine, nutritional psychiatry, and biologically informed treatments increasingly converge, it is becoming difficult to justify approaches that address cognition and emotion in isolation from physiology. Integrative models such as NA-CBT are well positioned to contribute to this evolving landscape by offering clinicians a coherent framework that bridges affective neuroscience with everyday therapeutic practice (Mirea, 2025).

NA-CBTยฎ positions itself not merely as a set of techniques, but as a compassion-centred, neurobiologically informed psychological approach. While many traditional psychotherapeutic schools have historically approached lifestyle factors with caution, emerging evidence and clinical experience suggest that disrupted sleep, nutritional instability, and insufficient movement are pervasive across mental health presentations and frequently undermine therapeutic progress. Addressing these factors thoughtfully and collaboratively does not dilute psychological depth; rather, it creates the physiological conditions necessary for insight, emotional processing, and behavioural change to take root.

From this perspective, interventions such as TED are not ancillary to therapy but foundational. Encouraging appropriate medical collaboration when clients present with chronic fatigue or low energy can help identify modifiable physiological contributors that, when addressed, enhance affect regulation, therapeutic engagement, and overall quality of life. Such integration reflects a broader shift away from symptom-focused treatment toward whole-person care, where psychological flexibility, embodied awareness, and compassionate self-regulation become central therapeutic outcomes.

Taken together, this case suggests that the future of psychotherapy may lie less in refining ever more specialised techniques and more in developing integrative, transdiagnostic frameworks capable of holding mind, body, affect, and behaviour within a single coherent model. NA-CBT offers one such framework, grounded in neuroscience, oriented toward compassion, and designed to meet the complex realities of contemporary clinical practice.

Future Directions for Psychotherapy

The evolving landscape of mental health care increasingly calls for psychotherapeutic models that move beyond rigid diagnostic categories and isolated treatment techniques. As research continues to clarify the reciprocal influence of physiology, affect, cognition, and behaviour, future psychotherapy is likely to become more integrative, transdiagnostic, and biologically informed.

Approaches such as NeuroAffective-CBT point toward a future in which affect regulation and nervous-system stability are recognised as foundational prerequisites for psychological change. Rather than positioning lifestyle, embodiment, and self-regulation strategies as peripheral or adjunctive, emerging models are likely to incorporate these elements centrally within formulation and intervention. This shift has the potential to enhance treatment accessibility, durability of outcomes, and client autonomy.

Future developments in psychotherapy may also involve closer collaboration between psychological practitioners and other health disciplines, including primary care, nutritional psychiatry, and psychosomatic medicine. Such interdisciplinary integration may support earlier identification of physiological contributors to emotional distress and reduce unnecessary chronicity across mental health presentations.

Finally, the field may increasingly value therapeutic frameworks that prioritise psychological flexibility, compassion, and embodied self-awareness over symptom suppression alone. In this context, psychotherapy may evolve from a primarily corrective endeavour into a developmental process, one that supports individuals in cultivating sustainable self-regulation, resilience, and a more integrated sense of identity across the lifespan.


Disclaimer

This case study is intended for educational and professional discussion purposes only. It does not constitute clinical guidance, diagnosis, or treatment recommendations. Therapeutic approaches described should be applied only by appropriately trained professionals and adapted to individual client needs. Readers are advised to consult relevant clinical guidelines and professional supervision when translating concepts into practice.

Ethics and Anonymisation Statement

All identifying client information has been altered to protect anonymity. Informed consent was obtained for the use of anonymised clinical material for educational and dissemination purposes.


References

Beck AT. Cognitive therapy and the emotional disorders. New York: International Universities Press; 1976.

Chadwick P, Birchwood M, Trower P. Cognitive therapy for delusions, voices and paranoia. Chichester: Wiley; 1996.

Damasio A. The feeling of what happens: body and emotion in the making of consciousness. London: Heinemann; 1999.

Davidson RJ, McEwen BS. Social influences on neuroplasticity: stress and interventions to promote well-being. Nature Neuroscience. 2012;15(5):689โ€“695.

Engelkamp J. Memory for actions. Psychology of Learning and Motivation. 1998;38:1โ€“40.

Erten MM, Williams JM, Raes F, Hermans D. Memory Specificity Training for Depression and Posttraumatic Stress Disorder. Eur J Psychotraumatol. 2018;9(1):1432007. PMID: 29355369. doi:10.1080/20008198.2018.1432007.

Gilbert P. Compassion focused therapy. London: Routledge; 2010.

Hofmann SG, Asnaani A, Vonk IJ, Sawyer AT, Fang A. The efficacy of cognitive behavioural therapy: a review of meta-analyses. Cognitive Therapy and Research. 2012;36(5):427โ€“440.

Kashdan TB, Rottenberg J. Psychological flexibility as a fundamental aspect of health. Clin Psychology Rev. 2010;30(7):865โ€“878.

Kolb DA. Experiential learning: experience as the source of learning and development. Englewood Cliffs (NJ): Prentice Hall; 1984.

LeDoux J. The emotional brain: the mysterious underpinnings of emotional life. New York: Simon & Schuster; 1996.

Mirea D. The underlayers of NeuroAffective-CBTยฎ [Internet]. NeuroAffective-CBTยฎ; 2018 [cited 2026 Jan 19]. Available from: https://neuroaffectivecbt.com/2018/10/19/the-underlayers-of-neuroaffective-cbt/

Mirea D. Tired, Exercise and Diet your way out of trouble, TEDโ€™s your best friend [Internet]. NeuroAffective-CBTยฎ; 2023 [cited 2026 Jan 19]. Available from: https://neuroaffectivecbt.com/2023/07/18/teds-your-best-friend/

Mirea D. The use of lifestyle interventions in psychotherapy [Internet]. NeuroAffective-CBTยฎ; 2025 Dec 17 [cited 2026 Jan 19]. Available from: https://neuroaffectivecbt.com/2025/12/17/the-use-of-lifestyle-interventions-in-psychotherapy/

Mirea D. TED in NeuroAffective-CBTยฎ: an applied self-regulation framework for enhancing emotional well-being through sleep, movement, and nutrition [Internet]. NeuroAffective-CBTยฎ; 2025 Dec 10 [cited 2026 Jan 19]. Available from: https://neuroaffectivecbt.com/2025/12/10/ted-in-neuroaffective-cbt-an-applied-self-regulation-framework-for-enhancing-emotional-well-being-through-sleep-movement-and-nutrition/

Panksepp J. The basic emotional circuits of mammalian brains. Emotion Rev. 2011;3(1):5โ€“14.

Porges SW. The polyvagal theory: neurophysiological foundations of emotions, attachment, communication, and self-regulation. New York: W.W. Norton; 2011.

Safran JD, Segal ZV, Vallis TM, Shaw BF, Samstag LW. Assessing patient suitability for cognitive therapy. J Cognitive Psychotherapy. 1993;7(1):11โ€“23.

Schore AN. The science of the art of psychotherapy. New York: W.W. Norton; 2012.