
Rethinking Mechanisms of Change in CBT: A Historical Review Through Predictive Processing and Embodied Cognition

Dr Kristina Ivings and Daniel Mirea (10 November 2026)
| The NeuroAffective-CBT® Journal |

Abstract

This historical review draws on predictive processing and 4E cognition to reconsider how change occurs in cognitive behavioural therapies. It proposes that bodily regulation, imagery and behavioural practice may help clients revise threat expectations and expand what they feel able to do. NeuroAffective-CBT® serves as an example of how these methods can be integrated with cognitive reflection. The review also briefly considers the use of imaginal rehearsal in Hypno-CBT®. Further research could test which components contribute to change and whether gains carry into everyday life.

Keywords: Cognitive behavioural therapy, mechanisms of change, predictive processing, 4E cognition, embodiment, integrative psychotherapy

Introduction

Cognitive Behavioural Therapy (CBT) is the most extensively researched form of psychotherapy (Hofmann et al., 2012), and Dialectical Behaviour Therapy (DBT) is among the best-supported treatments for borderline personality disorder (Storebø et al., 2020). The models used to explain how these therapies work, to therapists and to clients, have not kept pace with contemporary neuroscience.

Psychoeducation in CBT and DBT commonly draws on simplified neuroanatomical stories and evolutionary models of emotion and behaviour. Compassion-Focused Therapy teaches a distinction between an “old brain” of evolved emotions and motives and a “new brain” of thought and imagination (Gilbert, 2009, 2010), echoing MacLean’s (1990) triune model. Widely used CBT-informed self-help presents anxiety as the product of an amygdala pathway that the cortex must work around or retrain (Pittman & Karle, 2015). DBT’s skills materials teach that primary emotions such as fear, anger, disgust and shame are innate and evolved, each serving a survival function (Linehan, 2015). Dual-system models also appear in theoretical accounts of CT: Clark and Beck (2010) proposed that anxiety and depression involve heightened bottom-up, amygdala-driven processing combined with weakened top-down, prefrontal reflective control. The dual-process theorists themselves are more cautious. Kahneman (2011) describes System 1 and System 2 as useful fictional characters rather than brain systems, and Evans and Stanovich (2013) prefer to speak of Type 1 and Type 2 processes. The clinical version hardens these metaphors into anatomy and casts the amygdala as a fear centre, a view that LeDoux (2015), whose earlier research helped establish the amygdala’s role in threat detection, now argues against.

Contemporary affective neuroscience describes cortical and subcortical regions as densely interconnected and jointly involved in both emotion and cognition (Pessoa, 2013; Barrett, 2020). Predictive processing retains a hierarchy of top-down and bottom-up signalling, but it is a single integrated hierarchy, not a contest between separate emotional and rational systems.

Our concern is not with the efficacy of CBT and DBT but with the models offered to explain it. Therapists and clients are asked to accept inaccurate accounts of their own biology, and the mismatch may obscure which components of treatment are effective. We suggest it may also have slowed the development of approaches that work with, rather than in spite of, the brain’s predictive and embodied organisation.

This paper draws on predictive processing and 4E cognition to set out a contemporary account of mind and brain, then uses it to re-read the history of psychotherapy: its Stoic antecedents, early somatic and behavioural methods, Beckian Cognitive Therapy (CT), metacognitive therapy, the third-wave approaches and DBT.

This review considers whether some interventions may work through processes that their original theories gave less attention to. Early behavioural approaches, including Salter’s (1949) conditioned reflex therapy and Wolpe’s (1958) systematic desensitisation, made action and bodily experience central to therapeutic learning. Beckian cognitive therapy (CT) retained behavioural methods and used some of them to test and revise beliefs. Later approaches, including Meichenbaum’s (1985) Stress Inoculation Training (SIT), continued to emphasise rehearsal and the graded application of coping skills. We use predictive processing and 4E cognition to explore how bodily regulation, rehearsal and action may contribute to therapeutic change. We close by considering how these methods can be integrated with cognitive reflection and how future research might test the proposed mechanisms.

Neuroscientific Foundations

Predictive Processing and Allostasis

A useful starting question is what a brain is for. Barrett (2017) argues that its core task is regulating the body rather than thinking: anticipating the needs of the organism and meeting them before they arise, a process she describes as running a budget for the body. The view draws on Sterling’s (2012) account of allostasis, the predictive regulation of physiological variables such as glucose, oxygen, water and salt. It is not universally accepted as the brain’s primary function, but it supplies the framing adopted here.

Predictive processing describes how this regulation might be achieved. The brain is modelled as a generative system that continually predicts its inputs and revises those predictions in light of prediction error, the mismatch between what was expected and what arrives (Friston, 2010; Clark, 2013). Predictions prepare the cardiovascular, metabolic and muscular systems in advance of anticipated demand, so prediction serves allostasis rather than operating separately from it.

Peters et al. (2017) argue that sustained uncertainty is metabolically costly, because a system that cannot resolve its predictions must remain mobilised. We propose that some of what clients describe as chronic worry, ambient threat and the urge to ruminate reflects this state of unresolved prediction error and sustained autonomic arousal. On this view, deliberate, linguistic thought is one form of the brain’s predictive activity, serving the regulation of the body and the guidance of action, rather than the brain’s defining function.

Precision weighting determines how much influence a signal has. The brain estimates the reliability of its predictions and of incoming sensory evidence and weights each accordingly (Friston, 2010; Clark, 2013). Precision weighting operates throughout the hierarchy, across exteroceptive, proprioceptive and interoceptive signals. Applied to interoception, the brain’s inference about the internal state of the body, it shapes how bodily states are felt and interpreted (Seth, 2013).

Where a prediction carries high precision, conflicting evidence can be discounted. In the rubber hand illusion, synchronous stroking of a visible rubber hand and the participant’s hidden hand leads participants to feel the touch as located on the rubber hand and to experience it as their own (Botvinick & Cohen, 1998). The sense of ownership is associated with activity in premotor cortex (Ehrsson et al., 2004), and threatening the rubber hand produces skin conductance responses (Armel & Ramachandran, 2003). Visual evidence given high precision reshapes the felt location of the body. Clinically, the analogy suggests that a high-precision prediction of threat could lead the brain to discount interoceptive and environmental evidence of safety, which would help explain why reassurance and contrary evidence often fail to reduce distress.

4E Cognition

4E cognition holds that the mind is not a program running inside an isolated skull. Mind is:

  • Embodied: shaped by visceral, gut–brain and autonomic states.
  • Embedded: functioning within a physical, socioeconomic and cultural niche.
  • Enacted: brought forth through sensorimotor activity and engagement with the environment.
  • Extended: offloading cognitive work onto external tools, technologies and spaces.

The 4E paradigm emerged as a philosophical and phenomenological critique of computer-metaphor cognitive science, with roots in the work of Varela, Thompson and Rosch (1991). Predictive processing grew out of computational neuroscience, formalised through models of Bayesian inference and the free-energy principle (Friston, 2010).

Clark (2016) argues that the two frameworks are compatible: predictive processing offers a candidate mechanism for embodied and enacted cognition, because the brain minimises prediction error partly by acting on the body and the world. The compatibility is debated, and radical enactivists reject the representational reading of predictive processing (Hutto & Myin, 2013). The argument here requires only the weaker claim that the brain’s predictions serve an organism that is embodied, embedded and acting in the world.

Affordances and Self-Efficacy

Gibson (1979) introduced the concept of affordances: the possibilities for action an environment offers an organism, given the fit between the organism’s capacities and the properties of its surroundings. Rietveld and Kiverstein (2014) extend this into a landscape of affordances, the field of possibilities open to an organism within a given practice and situation. A chair affords sitting; a phone affords contact with others.

We propose that the state of the body budget shapes which affordances are salient. When resources are ample, the landscape is rich with invitations to approach, connect and explore. When the budget is depleted, or the system is held in high-precision threat prediction, invitations to reward recede while obstacles and threats gain salience. A flight of stairs becomes a barrier and a social encounter becomes a threat.

This proposal offers a mechanistic reading of two earlier ideas. Salter (1949) argued that psychological health depends on excitation predominating over inhibition, illustrated by the image of a dog bounding into a room to see what it offers. Bandura (1977) argued that efficacy expectations, a person’s belief that they can carry out the behaviour an outcome requires, govern whether they initiate and persist in coping. In predictive processing terms, self-efficacy can be modelled as the precision the brain assigns to predictions of its own capacity to act and cope. High self-efficacy would make approach-related affordances salient before any action is taken, whereas low self-efficacy would act as a confident prediction of failure that narrows the perceived field in advance.

Emotions as Constructed

The view that emotions are discrete, biologically fixed responses is often traced to Darwin (1872), who argued that emotional expressions are innate and shared across cultures and species. Darwin did not present most expressions as adaptations; he explained many as “serviceable associated habits”, vestiges of actions that had once been useful. The later basic-emotion tradition recast emotions as evolved programmes, each with a characteristic expression and physiology (Ekman, 1992).

The idea acquired an anatomical home in MacLean’s limbic system, which he developed from 1949 and later incorporated into the triune brain model, summarised in his 1990 book (MacLean, 1990). The triune model presents the limbic system as an older emotional brain lying beneath a rational neocortex.

DBT’s skills curriculum draws on the basic-emotion tradition. It teaches that emotions have evolutionary functions and unfold through a sequence of prompting events, interpretations, biological changes, action urges and expressions (Linehan, 2015). Because the sequence includes interpretation, the model is not purely reflexive, but it presents a set of primary emotions as universal, biologically prepared responses, and this is the model taught to DBT therapists and clients.

Barrett’s (2017) theory of constructed emotion offers an alternative. On this account, emotions are categories the brain constructs in the moment by applying learned concepts to core affect, rather than circuits waiting to be triggered. Core affect is a continuous blend of valence (pleasant or unpleasant) and arousal, often represented as a circumplex (Russell, 2003; Barrett, 2006). An emotion such as fear or anger arises when the brain categorises a change in core affect, in context, using culturally learned concepts. Basic-emotion theorists dispute this account (Ekman, 1992), but it is consistent with the predictive framework above and carries different clinical implications: if emotions are constructed predictions, they can be changed through the body, the situation and the concepts available to the client.

A Historical Re-Reading of the Clinical Lineage

This section does not claim that earlier clinicians held predictive processing views. It asks how far each approach’s effective components can be explained by the framework above, and how closely its stated theory matches those components.

Stoic Antecedents

Epictetus held that people are disturbed not by events but by their judgements about them (Enchiridion 5) and advised wanting events to happen as they do rather than as one wishes (Enchiridion 8) (Epictetus, 2014). In predictive processing terms, a rigid judgement about how events should unfold resembles a high-precision prediction that reality repeatedly violates. Beck and Ellis both acknowledged Stoicism as an antecedent of their approaches, but they adopted its emphasis on judgement more readily than its emphasis on acceptance.

Somatic and First-Wave Behavioural Approaches

Early somatic approaches targeted the body directly. Jacobson’s (1938) progressive relaxation and Benson’s (1975) relaxation response aimed to lower muscular tension and sympathetic arousal. These methods change the interoceptive evidence available to the brain, and we hypothesise that they reduce the precision assigned to threat predictions without requiring verbal engagement.

First-wave behaviour therapy focused on environmental contingencies, conditioning and overt behaviour (Skinner, 1953; Salter, 1949; Wolpe, 1958). It did not exclude internal experience. Wolpe’s systematic desensitisation paired deep muscle relaxation with imagined scenes from a graded hierarchy, and Wolpe used hypnosis to deepen relaxation (Wolpe, 1958). Systematic desensitisation is an early demonstration that embodied imagery, practised in a regulated bodily state, can change fear responses.

Salter (1949) argued that anxiety reflects an excess of inhibition and prescribed excitatory exercises: spontaneous, expressive action, including voicing feelings and acting on impulse. His approach was clinically influential but was never tested in controlled trials. Salter had earlier written on hypnosis (Salter, 1944), and his emphasis on action, expression and expanded behavioural capacity anticipates the enactive view later developed in 4E cognition. Read through this lens, uninhibited action exposes the person to real-world prediction errors whose evidence is likely to update the generative model more effectively than abstract verbal reflection.

Self-Efficacy and Stress Inoculation Training

Two later developments kept action and rehearsal central. Bandura’s (1977) self-efficacy theory identified performance accomplishments as the most powerful source of efficacy expectations, ahead of vicarious experience, verbal persuasion and physiological states, and proposed that desensitisation and exposure work partly by raising self-efficacy. SIT combined conceptual preparation with skills acquisition and rehearsal, including imaginal and in vivo rehearsal of coping, followed by graded application (Meichenbaum, 1985). SIT includes cognitive restructuring and self-instruction, but its rehearsal and application phases embody the principle that coping is learned through practice.

Neither was rejected by CBT. Self-efficacy is widely used within CBT, and SIT remains in use, particularly for stress and trauma. Our claim is narrower: in Beckian theory, efficacy and rehearsal are not the mechanism of change; belief change is.

The Cognitive Revolution

Beck (1976) and Ellis (1962) placed thought content at the centre of the clinical model. Beck’s CT identified negative automatic thoughts, underlying assumptions and core beliefs, organised in schemas, as the primary targets of treatment. Ellis targeted irrational beliefs, worked through his ABC (later ABCDE) framework in Rational Emotive Behaviour Therapy.

Beck’s later work broadened the model. His theory of modes integrates cognitive, affective, motivational, behavioural and physiological systems (Beck, 1996), the generic cognitive model extends this account across disorders (Beck & Haigh, 2014), and Clark and Beck (2010) linked the model to neurobiological findings. In clinical practice, however, CT remains centred on content: identifying “thinking errors”, examining the evidence for and against thoughts, and constructing more rational alternatives through thought records and Socratic questioning.

CT retained behavioural methods, including activity scheduling, graded tasks, exposure and behavioural experiments, but changed their rationale. Behavioural experiments are framed as tests of explicit predictions, with success measured by the degree of belief change, so that action serves as evidence in a cognitive argument. The approach rests on an implicitly Cartesian assumption that the problem lies in the accuracy of mental representations and that the remedy is better representations.

Metacognitive Therapy

Wells’ Self-Regulatory Executive Function (S-REF) model (Wells & Matthews, 1994) is the clearest precedent for the process-over-content position taken here. It locates the maintenance of disorder in the Cognitive Attentional Syndrome (CAS), the pattern of perseverative worry and rumination, threat monitoring and counterproductive coping driven by positive and negative beliefs about thinking, rather than in thought content. Metacognitive Therapy (MCT) accordingly does not dispute content. It modifies these beliefs and trains non-engagement with thoughts through detached mindfulness and the Attention Training Technique (ATT; Wells, 2009). ATT involves focusing on and switching attention between multiple external sounds; Wells stresses that it is not distraction but training in flexible, executive control of attention, which also disconfirms beliefs that attention and worry are uncontrollable.

Predictive processing allows this account to be restated. Metacognitive beliefs can be read as high-level priors governing the precision assigned to internally generated content, so that believing worry to be necessary or uncontrollable keeps precision on threat simulations. ATT can be read as practice in reallocating precision away from such content. The frameworks differ in what they treat as the substrate of change. S-REF is framed in information-processing terms of levels, stored plans and executive control, whereas a predictive and 4E account treats the same phenomena as properties of a single embodied hierarchy regulating the body budget.

MCT therefore converges with the present argument at the clinical level while offering a different account of how change occurs. Hypno-CBT® uses hypnosis to rehearse coping responses in imagination (Davis, 2016). Whether using hypnosis to help clients disengage from thoughts, followed by imaginal rehearsal, offers benefits beyond detached mindfulness remains an open question.

Third-Wave Approaches and DBT

Mindfulness-Based Cognitive Therapy (MBCT) and Acceptance and Commitment Therapy (ACT) also moved from content to process. MBCT trains clients to relate to thoughts as passing mental events rather than facts (Segal et al., 2002). ACT targets the function of thoughts through defusion, acceptance and contact with the present moment, and is grounded in functional contextualism and relational frame theory (Hayes et al., 2006). ACT explicitly rejects mechanistic information-processing models, and its contextual, action-oriented stance is arguably closer to the enactive view taken here than any other variant of CBT. Its limitation, from the present perspective, is that it deliberately works at the level of functional analysis rather than mechanism, so it does not offer an account of how these processes relate to prediction and the regulation of the body.

DBT combines behavioural science with Zen-informed acceptance and mindfulness practice (Linehan, 1993). Its distress tolerance skills include TIPP: changing body Temperature (for example, cold water on the face to trigger the dive reflex), Intense exercise, Paced breathing and Paired muscle relaxation (Linehan, 2015). These skills act directly on autonomic arousal. We hypothesise that a strong, immediate change in bodily input forces rapid updating of interoceptive predictions and draws precision away from internally generated threat content. DBT’s mindfulness skills ask clients to observe and describe internal experience without judgement, echoing contemplative traditions that aim to quieten the mind rather than argue with it. DBT thus restored much of what CT had marginalised, but its explanatory framework remains the basic-emotion model described above, together with the states-of-mind metaphor of emotion mind, reasonable mind and wise mind.

Recent Integrative Models

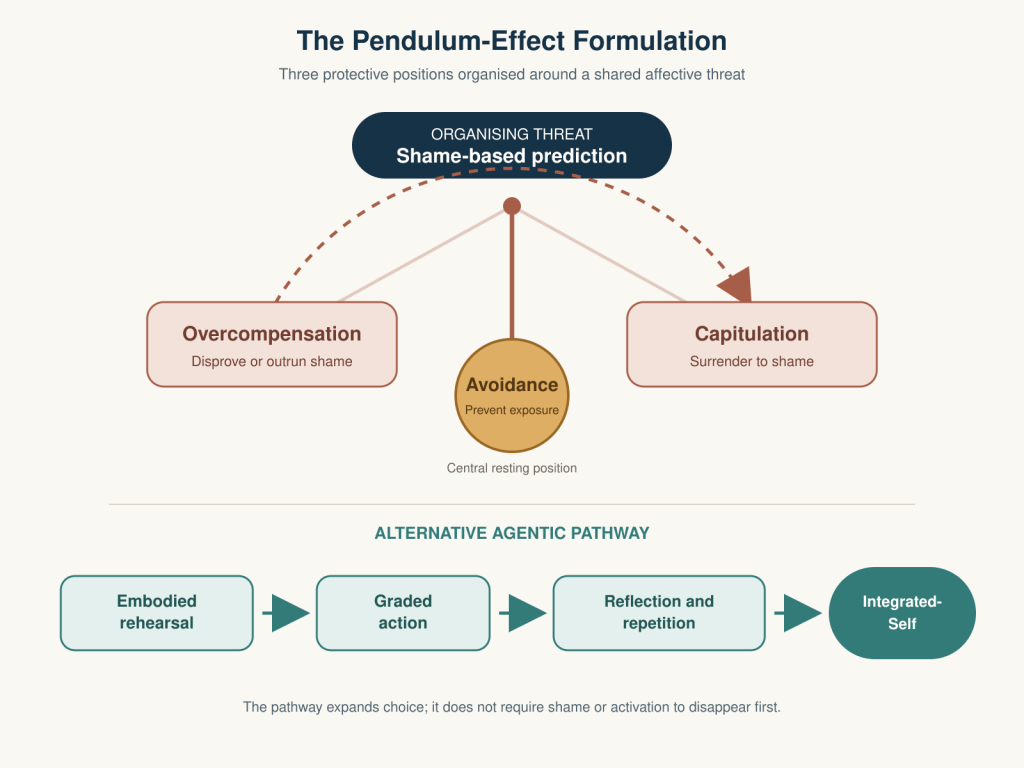
Daniel Mirea’s NeuroAffective-CBT® (NA-CBT), developed for difficulties involving shame, self-disgust and low self-esteem, combines cognitive-behavioural methods with affective neuroscience and embodied regulation (Mirea, 2018). Its six-module structure places physiological stabilisation early in treatment. The Tiredness, Exercise and Diet (TED) framework addresses sleep and fatigue, physical activity and nutrition as foundations for emotional regulation (Mirea, 2025). The Pendulum Effect formulation describes how clients may oscillate between overcompensation, avoidance and capitulation in response to a shared affective threat. More recent work uses embodied rehearsal, mental imagery and values-guided behavioural experiments to develop what Mirea calls the Integrated-Self (Mirea, 2026).

This emphasis on embodied and experiential learning is evident in NeuroAffective Narrative Reconsolidation (NNR), the fourth of the six NA-CBT modules. The method can be interpreted through the lens of 4E cognition, as illustrated by its use in clinical supervision (Mirea & People, 2026). It brings bodily sensations and emotional responses into the retelling of a significant experience (embodied) and situates that experience within the person’s relationships and circumstances (embedded). First-person role-play, imagery and rehearsal allow alternative responses to be explored through action (enacted). The supervisor’s prompts and the structure of the exercise can also serve as external supports for organising and revisiting the account (extended).

Mirea reports learning directly from Donald Meichenbaum and identifies Stress Inoculation Training as an influence on NA-CBT’s use of coping-skills rehearsal and graded practice. The NeuroAffective-CBT® Journal publishes Mirea’s conceptual and clinical papers alongside case studies and reviews by other clinicians. The case studies illustrate how clinicians have applied the framework in practice. Mirea presents NA-CBT as a clinical formulation framework, and its effectiveness as a treatment protocol remains to be established.

Clinical Implications

If the brain is a predictive system whose core task is allostasis, distress is better understood as a problem of prediction and precision than as a problem of inaccurate belief. When rigid top-down expectations repeatedly meet contrary evidence, the system remains mobilised, and the client experiences worry, ambient threat and the drive to ruminate.

Predictive processing also suggests why CT’s focus on content may be limited. Thoughts are simulations generated by a predictive system, and their influence depends on the precision (the confidence or salience) the system assigns to them. Sustained analytical engagement with distressing content is itself a precision-raising act: attending to a thought, interrogating it and treating it as a problem to be solved signals that it matters. The client may exchange irrational rumination for rational rumination without leaving the loop. A related difficulty is familiar to cognitive therapists: clients often report knowing an alternative thought to be true without feeling it to be true, a pattern described as rational-emotional dissociation (Stott, 2007). Where behavioural experiments succeed, predictive processing would locate the change in the precision updating produced by acting, not in the verbal re-rating that follows, which suggests they may work despite their stated rationale rather than because of it.

This does not mean that only overt action can produce change. Imagined action engages much of the neural machinery used to plan and perform it (Jeannerod, 2001), so vivid, embodied rehearsal is closer to offline action than to verbal reflection, and Wolpe’s imaginal hierarchies show its clinical value. The relevant distinction is between abstract, evaluative thinking about experience and embodied simulation of it. Bandura (1977) nonetheless ranks performance accomplishments above other sources of efficacy, so simulation is best treated as preparation for enactive mastery rather than a replacement for it.

Through the lens of affordances, anxiety and depression can be understood partly as the perception of an impoverished, threatening field of possibilities, not only as misinterpretation. The aim of therapy then shifts from changing what a client thinks about the world toward expanding what they perceive themselves able to do in it, by raising self-efficacy and the salience of approach-related affordances.

The same framework explains why contemplative traditions aim to quieten the mind rather than dispute its content. Laukkonen and Slagter (2021) propose that meditation progressively reduces the precision and influence of high-level predictions. Epictetus’s advice to want events to happen as they do points in the same direction, since relaxing demands on reality reduces the prediction error those demands generate. We hypothesise that resting in non-evaluative awareness lowers the precision of top-down expectations about how things should be, reducing prediction error, autonomic arousal and metabolic cost.

A clinical model built on this account would be enactive and embodied. It would use somatic regulation to restore the body budget, embodied simulation to raise self-efficacy, and real-world action to confirm it, opening the client’s landscape to possibilities for safety, agency and action not previously perceived.

The Efficacy Question

Johnsen and Friborg (2015) reported that the effects of CBT for depression declined across trials published since 1977. The finding is contested: a re-analysis by Ljótsson et al. (2017) argued that the decline was not robust. The data cover depression only, and because they begin after CT was established, they cannot show that the shift from behaviour therapy to CT reduced efficacy. We cite the finding as a reason for concern rather than as evidence for the present thesis.

More direct evidence comes from studies separating CT’s components. In a component analysis, behavioural activation alone produced outcomes comparable to full CT for depression (Jacobson et al., 1996), and in a later trial behavioural activation performed comparably to antidepressant medication and better than CT among more severely depressed clients (Dimidjian et al., 2006). Longmore and Worrell (2007) reviewed the evidence and questioned whether challenging thoughts is necessary for CBT’s effects. The evidence is not uniform, and Lorenzo-Luaces et al. (2015) review findings that cognitive change can mediate symptom change in CT. Taken together, these findings are consistent with the view that much of CBT’s effectiveness derives from its behavioural and experiential components, and that CT may be effective despite, rather than because of, its stated rationale.

Conclusion

Across its history, psychotherapy has developed somatic, behavioural, experiential and process-focused interventions whose effects can be understood in more than one way. Predictive processing and 4E cognition offer complementary perspectives on how bodily regulation, expectations, action and context may shape therapeutic learning. From this perspective, some of the benefits of CBT and DBT may arise from changes in what people feel able to do as well as from changes in how they interpret their experiences.

Cognitive reflection can help people identify what they expect to happen, while bodily regulation, imagery and rehearsal can help them prepare to try a different response. Acting in everyday settings gives them an opportunity to learn from what happens. NeuroAffective-CBT® offers one example of how embodied narrative work and values-guided behavioural experiments might connect new understandings with action in daily life (Mirea, 2026; Mirea & People, 2026).

Further research could examine what these components contribute, for whom and under what conditions. Comparing an established intervention with and without imaginal rehearsal could test whether rehearsal improves coping in situations clients previously avoided. Tracking bodily arousal, threat expectations and perceived coping ability during therapy could help clarify whether changes in these processes precede improvements in everyday functioning. Follow-up could show whether those improvements persist.

Taken together, these ideas make the case for a new wave of integrative cognitive behavioural therapies rooted in embodied learning, informed by contemporary neuroscience and guided by research into how change occurs in therapy and carries into everyday life.

References

Armel, K. C., & Ramachandran, V. S. (2003). Projecting sensations to external objects: Evidence from skin conductance response. Proceedings of the Royal Society B: Biological Sciences, 270(1523), 1499–1506.

Bandura, A. (1977). Self-efficacy: Toward a unifying theory of behavioral change. Psychological Review, 84(2), 191–215.

Barrett, L. F. (2006). Solving the emotion paradox: Categorization and the experience of emotion. Personality and Social Psychology Review, 10(1), 20–46.

Barrett, L. F. (2017). How emotions are made: The secret life of the brain. Houghton Mifflin Harcourt.

Barrett, L. F. (2020). Seven and a half lessons about the brain. Houghton Mifflin Harcourt.

Beck, A. T. (1976). Cognitive therapy and the emotional disorders. International Universities Press.

Beck, A. T. (1996). Beyond belief: A theory of modes, personality, and psychopathology. In P. M. Salkovskis (Ed.), Frontiers of cognitive therapy (pp. 1–25). Guilford Press.

Beck, A. T., & Haigh, E. A. P. (2014). Advances in cognitive theory and therapy: The generic cognitive model. Annual Review of Clinical Psychology, 10, 1–24.

Benson, H. (1975). The relaxation response. William Morrow.

Botvinick, M., & Cohen, J. (1998). Rubber hands ‘feel’ touch that eyes see. Nature, 391(6669), 756.

Clark, A. (2013). Whatever next? Predictive brains, situated agents, and the future of cognitive science. Behavioral and Brain Sciences, 36(3), 181–204.

Clark, A. (2016). Surfing uncertainty: Prediction, action, and the embodied mind. Oxford University Press.

Clark, D. A., & Beck, A. T. (2010). Cognitive theory and therapy of anxiety and depression: Convergence with neurobiological findings. Trends in Cognitive Sciences, 14(9), 418–424.

Darwin, C. (1872). The expression of the emotions in man and animals. John Murray.

Davis, M. R. (2016, October 5). The Hypno-CBT® toolbox: 35 different therapy techniques. UK College of Hypnosis & Hypnotherapy. https://www.ukhypnosis.com/2016/10/05/the-hypno-cbt-toolbox-35-different-interventions/

Dimidjian, S., Hollon, S. D., Dobson, K. S., Schmaling, K. B., Kohlenberg, R. J., Addis, M. E., Gallop, R., McGlinchey, J. B., Markley, D. K., Gollan, J. K., Atkins, D. C., Dunner, D. L., & Jacobson, N. S. (2006). Randomized trial of behavioral activation, cognitive therapy, and antidepressant medication in the acute treatment of adults with major depression. Journal of Consulting and Clinical Psychology, 74(4), 658–670.

Ehrsson, H. H., Spence, C., & Passingham, R. E. (2004). That’s my hand! Activity in premotor cortex reflects feeling of ownership of a limb. Science, 305(5685), 875–877.

Ekman, P. (1992). An argument for basic emotions. Cognition and Emotion, 6(3–4), 169–200.

Ellis, A. (1962). Reason and emotion in psychotherapy. Lyle Stuart.

Epictetus. (2014). Discourses, fragments, handbook (R. Hard, Trans.). Oxford University Press.

Evans, J. St. B. T., & Stanovich, K. E. (2013). Dual-process theories of higher cognition: Advancing the debate. Perspectives on Psychological Science, 8(3), 223–241.

Friston, K. (2010). The free-energy principle: A unified brain theory? Nature Reviews Neuroscience, 11(2), 127–138.

Gilbert, P. (2009). The compassionate mind. Constable.

Gilbert, P. (2010). Compassion focused therapy: Distinctive features. Routledge.

Gibson, J. J. (1979). The ecological approach to visual perception. Houghton Mifflin.

Hayes, S. C., Luoma, J. B., Bond, F. W., Masuda, A., & Lillis, J. (2006). Acceptance and commitment therapy: Model, processes and outcomes. Behaviour Research and Therapy, 44(1), 1–25.

Hofmann, S. G., Asnaani, A., Vonk, I. J. J., Sawyer, A. T., & Fang, A. (2012). The efficacy of cognitive behavioral therapy: A review of meta-analyses. Cognitive Therapy and Research, 36(5), 427–440.

Hutto, D. D., & Myin, E. (2013). Radicalizing enactivism: Basic minds without content. MIT Press.

Jacobson, E. (1938). Progressive relaxation. University of Chicago Press.

Jacobson, N. S., Dobson, K. S., Truax, P. A., Addis, M. E., Koerner, K., Gollan, J. K., Gortner, E., & Prince, S. E. (1996). A component analysis of cognitive-behavioral treatment for depression. Journal of Consulting and Clinical Psychology, 64(2), 295–304.

Jeannerod, M. (2001). Neural simulation of action: A unifying mechanism for motor cognition. NeuroImage, 14(1), S103–S109.

Johnsen, T. J., & Friborg, O. (2015). The effects of cognitive behavioral therapy as an anti-depressive treatment is falling: A meta-analysis. Psychological Bulletin, 141(4), 747–768.

Kahneman, D. (2011). Thinking, fast and slow. Farrar, Straus and Giroux.

Laukkonen, R. E., & Slagter, H. A. (2021). From many to (n)one: Meditation and the plasticity of the predictive mind. Neuroscience & Biobehavioral Reviews, 128, 199–217.

LeDoux, J. E. (2015). Anxious: Using the brain to understand and treat fear and anxiety. Viking.

Linehan, M. M. (1993). Cognitive-behavioral treatment of borderline personality disorder. Guilford Press.

Linehan, M. M. (2015). DBT skills training manual (2nd ed.). Guilford Press.

Ljótsson, B., Hedman, E., Mattsson, S., & Andersson, E. (2017). The effects of cognitive-behavioral therapy for depression are not falling: A re-analysis of Johnsen and Friborg (2015). Psychological Bulletin, 143(3), 321–325.

Longmore, R. J., & Worrell, M. (2007). Do we need to challenge thoughts in cognitive behavior therapy? Clinical Psychology Review, 27(2), 173–187.

Lorenzo-Luaces, L., German, R. E., & DeRubeis, R. J. (2015). It’s complicated: The relation between cognitive change procedures, cognitive change, and symptom change in cognitive therapy for depression. Clinical Psychology Review, 41, 3–15.

MacLean, P. D. (1990). The triune brain in evolution: Role in paleocerebral functions. Plenum Press.

Meichenbaum, D. (1985). Stress inoculation training. Pergamon Press.

Mirea, D. (2018). The underlayers of NeuroAffective-CBT. Academia.edu. https://www.academia.edu/40996196/The_underlayers_of_NeuroAffective_CBT_by_Mirea_D

Mirea, D. (2025, December 10). TED in NeuroAffective-CBT®: An applied self-regulation framework for enhancing emotional well-being through sleep, movement, and nutrition. The NeuroAffective-CBT® Journal. https://neuroaffectivecbt.com/2025/12/10/ted-in-neuroaffective-cbt-an-applied-self-regulation-framework-for-enhancing-emotional-well-being-through-sleep-movement-and-nutrition/

Mirea, D. (2026, September 3). Beyond “fake it till you make it”: The Pendulum-Effect, embodied rehearsal and the development of the Integrated-Self. The NeuroAffective-CBT® Journal. https://neuroaffectivecbt.com/2026/09/03/beyond-fake-it-till-you-make-it-the-pendulum-effect-embodied-rehearsal-and-the-development-of-the-integrated-self/

Mirea, D., & People, C. (2026, November 3). NeuroAffective Narrative Reconsolidation (NNR) in clinical supervision: A case illustration of male relationship loss and grief. The NeuroAffective-CBT® Journal. https://www.academia.edu/180135956

Pessoa, L. (2013). The cognitive-emotional brain: From interactions to integration. MIT Press.

Peters, A., McEwen, B. S., & Friston, K. (2017). Uncertainty and stress: Why it causes diseases and how it is mastered by the brain. Progress in Neurobiology, 156, 164–188.

Pittman, C. M., & Karle, E. M. (2015). Rewire your anxious brain: How to use the neuroscience of fear to end anxiety, panic, and worry. New Harbinger.

Rietveld, E., & Kiverstein, J. (2014). A rich landscape of affordances. Ecological Psychology, 26(4), 325–352.

Russell, J. A. (2003). Core affect and the psychological construction of emotion. Psychological Review, 110(1), 145–172.

Salter, A. (1944). What is hypnosis: Studies in auto and hetero conditioning. Richard R. Smith.

Salter, A. (1949). Conditioned reflex therapy: The direct approach to the reconstruction of personality. Creative Age Press.

Segal, Z. V., Williams, J. M. G., & Teasdale, J. D. (2002). Mindfulness-based cognitive therapy for depression: A new approach to preventing relapse. Guilford Press.

Seth, A. K. (2013). Interoceptive inference, emotion, and the embodied self. Trends in Cognitive Sciences, 17(11), 565–573.

Skinner, B. F. (1953). Science and human behavior. Macmillan.

Sterling, P. (2012). Allostasis: A model of predictive regulation. Physiology & Behavior, 106(1), 5–15.

Storebø, O. J., Stoffers-Winterling, J. M., Völlm, B. A., Kongerslev, M. T., Mattivi, J. T., Jørgensen, M. S., Faltinsen, E., Todorovac, A., Sales, C. P., Callesen, H. E., Lieb, K., & Simonsen, E. (2020). Psychological therapies for people with borderline personality disorder. Cochrane Database of Systematic Reviews, (5), Article CD012955.

Stott, R. (2007). When head and heart do not agree: A theoretical and clinical analysis of rational-emotional dissociation (RED) in cognitive therapy. Journal of Cognitive Psychotherapy, 21(1), 37–50.

Varela, F. J., Thompson, E., & Rosch, E. (1991). The embodied mind: Cognitive science and human experience. MIT Press.

Wells, A. (2009). Metacognitive therapy for anxiety and depression. Guilford Press.

Wells, A., & Matthews, G. (1994). Attention and emotion: A clinical perspective. Lawrence Erlbaum.

Wolpe, J. (1958). Psychotherapy by reciprocal inhibition. Stanford University Press.

Declaration of interests

Dr Kristina Ivings (HCPC, BPS) is Head of the Hypno-CBT® Research Unit. Daniel Mirea is the founder of NeuroAffective-CBT® and has authored and co-authored publications on the model that are cited in this review. These professional interests are relevant to the selection and interpretation of material on Hypno-CBT® and NeuroAffective-CBT®. The review discusses both approaches as examples of recent integrative developments. The proposed mechanisms of change are presented as hypotheses for empirical investigation.

Authorship and attribution

This selective historical review and conceptual analysis draws on published research and publicly available clinical and training resources. The authors distinguish the claims made in the cited sources from their own interpretation of earlier therapies through predictive processing and 4E cognition.

Data availability

No original participant data were collected or analysed for this review. The sources are listed in the references.

Ethics and confidentiality

The article draws on publicly available sources and contains no original participant data or identifiable clinical material.

Can Martial Arts Training Make a Difference to Mental Health?

Matching Movement to the Individual Through Regulation, Agency and Meaning

Chris People and Daniel Mirea (23 October 2026)
| The NeuroAffective-CBT® Journal |

Introduction

Combat training and mental health hardly seem to belong in the same sentence. The connection is counterintuitive. Combat suggests aggression, confrontation and the possibility of harm. Concerns about injury, including brain injury in activities involving head contact, are real and deserve attention (Neidecker et al., 2019). Why, then, consider martial arts within a discussion of psychological wellbeing?

To a keen observer, the answer may emerge through the training itself. What becomes apparent is how much attention is given to the art: learning movement, judging distance, coordinating effort, responding to another person and exercising control. In a supportive training environment, these abilities develop gradually, with the intensity and physical demands adjusted as the participant gains familiarity and skill.

Martial arts also have a substantial interpersonal dimension. Individual practice is important, but partner exercises introduce something different: another person whose movement, timing and response cannot always be fully predicted. The participant must attend, interpret and act while remaining aware of their own reactions. They may need to communicate a limit, request a slower pace, accept correction or manage the frustration of getting something wrong.

Breathing is often part of this learning. In some traditions, explicit instruction in breathing accompanies the development of posture, movement and control from an early stage. Japanese martial traditions may direct focused attention towards the hara, while Chinese practices such as Tai Chi emphasise the lower dantian, traditionally understood as a centre of vital energy (Mai, 2015; National Qigong Association, 2025). These concepts provide ways of organising attention around the abdomen, breathing and coordinated movement. Breathing becomes something to notice and coordinate with action, particularly as effort and intensity change.

Figure 1: Karate meditation (mokusō): bringing attention to the hara (the lower abdomen) through an upright, relaxed posture and gentle abdominal breathing.

Attention, bodily awareness, breathing, gradual engagement with discomfort and responsiveness to others are also familiar concerns within mindfulness and emotional regulation approaches. Their presence in martial arts makes the clinical connection worth exploring. What might a participant be learning psychologically while practising physically? Could these experiences be connected more deliberately with therapeutic goals?

Our observations and individual experiences suggest that participants can learn more than the execution of a technique. Someone who initially responds with excessive tension, hurried movement or withdrawal may gradually become more able to pause, direct attention, adjust effort and choose what to do next. Another may discover that asking for help or expressing a boundary allows participation to continue. These experiences may acquire psychological significance even when neither instructor nor participant describes them in therapeutic language.

From a NeuroAffective-CBT perspective, lifestyle interventions are an essential part of promoting health and resilience. We propose that appropriately selected martial arts training may provide a practical setting for rehearsing regulation and agency. The relevant learning will differ between individuals. It may involve remaining engaged while uncomfortable, responding less harshly to mistakes, exercising restraint or recognising when to stop. These possibilities depend on the training environment, the quality of instruction and the meaning the person gives to participation.

Matching movement to the individual is therefore central. Preferences, physical capacity, cultural meaning, access and recovery all influence whether an activity is suitable and sustainable. The same exercise may offer one person an experience of capability while becoming another demand through which someone else judges or punishes themselves. Understanding that difference belongs within therapeutic formulation.

This selective narrative review brings together exercise and martial arts research with clinical reasoning and observations from training. Drawing on NeuroAffective-CBT alongside established cognitive behavioural approaches, we examine how chosen and adapted participation might support attention, coping self-instruction, assertiveness, mastery and belonging. A hypothetical clinical illustration shows how physical practice can be connected with a specific prediction, collaborative review and an experiment outside training.

The wider exercise literature supports therapeutic relevance, while evidence specific to martial arts remains heterogeneous. Our observations inform the proposed applications rather than establish their effectiveness. The question is how particular forms of training, matched to the individual and delivered within suitable conditions, might support mental health and whether what is learned during practice becomes available in everyday life.

Keywords: martial arts; combat sports; lifestyle interventions; cognitive behavioural therapy; NeuroAffective-CBT; emotional regulation; agency; psychological flexibility; therapeutic learning.

Martial Arts and the Cultivation of Mind and Body

Organised combat practices have a documented history extending across millennia and cultures. Wrestling entered the ancient Olympic programme in 708 BCE, boxing in 688 BCE and pankration, which combined striking and wrestling, in 648 BCE. These dates concern their inclusion in the Games rather than the origins of combat practice, but they demonstrate the longstanding place of fighting skills within organised physical culture (Foundation of the Hellenic World, n.d.).

The history of Chinese martial arts provides a further connection between physical practice, cultural meaning and self-cultivation. Shahar (2008) documents the involvement of Shaolin monks in seventh-century military events and traces the subsequent development of their martial traditions. This history encompasses armed and unarmed practices, religious commitments and relationships with political institutions. Later developments also connected martial practice with therapeutic purposes. Shaolin represents one important tradition within a diverse history, illustrating how fighting skills could become associated with broader understandings of health, discipline and personal development.

In the twentieth century, Bruce Lee brought the relationship between martial practice and personal philosophy to a wide international audience. His reflections emphasised adaptability, self-expression and learning through experience. His water metaphor presented responsiveness as an alternative to rigidly imposing a predetermined form. These ideas offer a philosophical connection with contemporary interests in psychological flexibility and agency, although Lee was articulating a philosophy of practice rather than a clinical treatment model (Bruce Lee Enterprises, n.d.).

Accounts of Lee’s recovery following a serious back injury add a personal dimension to this relationship. His family describes pain and emotional difficulty, extensive study, rest and a cautious return to movement. This account illustrates purposeful engagement with physical limitation, bringing reflection, learning and action together. It remains a biographical account rather than evidence that determination or self-instruction alone repaired the injury (Bruce Lee Enterprises, 2017).

Clinical interest in these connections also has an established history. Fuller (1988) discussed parallels between martial arts and psychotherapeutic concepts, including possible clinical applications. Twemlow and Sacco (1998) described therapeutic applications with adolescents presenting with violent behaviour. These contributions provide a foundation for asking how particular experiences within training might become relevant to an individual’s psychological difficulties and treatment goals.

Beyond the instruction to exercise

Recommending exercise can leave the main therapeutic problem untouched. A person may understand that movement could help and still feel unable to enter a gym, tolerate being a beginner or return after a difficult first session. Shame, fatigue, anticipated judgement and practical barriers can make an apparently simple recommendation difficult to act upon.

Clinical work therefore needs to address how participation becomes possible and what the person learns through it. A correction might be interpreted as evidence of inadequacy or as ordinary assistance in learning. Asking for a pause might feel humiliating or become an experience of effective choice.

The same activity can serve different functions. Training may support curiosity and connection, reinforce punitive standards or provide temporary escape from distress. Its therapeutic significance depends on the person’s formulation and experience. Salkovskis et al. (2023) describe therapy in terms of a shared understanding that is tested to enable more flexible responding. Applied to movement, this directs attention to the expectations being examined and the responses being practised.

Established approaches such as graded engagement, behavioural experiments and coping rehearsal provide methods for connecting physical practice with psychological learning. NeuroAffective-CBT offers one organising perspective for considering bodily regulation, protective responses and embodied rehearsal within this work.

Scope and approach

This selective narrative review is intended primarily for clinicians working with adults. Sources are brought together according to their relevance to exercise outcomes, martial arts and boxing, participation and candidate psychological processes. Systematic reviews and meta-analyses inform the evidence overview; selected trials and conceptual publications address particular clinical questions. The synthesis is purposive and does not claim exhaustive coverage or an independent formal quality appraisal.

General exercise findings are distinguished from evidence concerning particular disciplines and interventions. Outcomes are also distinguished from the mechanisms proposed to explain them. NeuroAffective-CBT publications provide conceptual and practitioner perspectives rather than independent empirical validation of the integrated approach.

The clinical proposals additionally draw on the authors’ observations and individual experiences of training. These inform hypothesis development rather than constitute systematically collected outcome data. The worked illustration is hypothetical, and no original patient data are reported.

What participants actually do

Martial arts and combat sports overlap, but neither label defines a uniform intervention. Traditional forms, non-contact boxing, recreational grappling and competitive mixed martial arts involve different movements, expectations and exposures. A practice may emphasise cultural tradition, self-defence, fitness or competition.

For clinical interpretation, important distinctions concern contact, sparring, exertion, instruction and freedom to stop. Shadowboxing and pad work can use striking movements without participants receiving blows. Grappling involves close physical contact and its own injury exposures. Recreational training and competition can differ substantially even within one club.

The learning environment matters alongside these physical ingredients. An instructor who welcomes questions and adapts tasks creates different opportunities from one who treats uncertainty or stopping as weakness. Community membership, traditional philosophy and shared rituals may matter in some settings and be absent in others.

An individualised recommendation therefore needs to specify what the person will do, with whom, under which conditions and for what purpose. The clinical applications discussed here concern mainly recreational training and adapted non-contact activities. Contact and competition remain separate choices rather than necessary stages of therapeutic progress.

What the exercise evidence supports

Physical activity has a substantial evidence base in mental health. Singh et al. (2023) brought together 97 systematic reviews covering 1,039 trials and 128,119 participants, reporting improvements in depression, anxiety and psychological distress across varied adult populations. However, 77 reviews received a critically low AMSTAR-2 methodological quality rating. These ratings concern the reviews rather than 77 individual trials.

Noetel et al. (2024) found benefits for several exercise modalities in depression, including walking or jogging, yoga and strength training, with confidence in estimates limited by study quality and other uncertainties. Gordon et al. (2018) identified an average reduction in depressive symptoms across 33 resistance-training trials involving 1,877 participants.

The evidence supports considering several forms of movement while leaving their selection and delivery open to individual planning. An advantage over inactivity or usual care may reflect structure, encouragement, expectation and social contact as well as exertion. Comparison with another credible activity asks a more specific question about relative benefit.

White et al. (2024) reviewed 247 studies examining mediators and moderators of the relationship between physical activity and mental health. Their synthesis identified support for self-esteem, self-efficacy, physical self-worth and social connection, with more qualified support for mastery and mindfulness. Most included studies were observational. These findings identify plausible processes for investigation while leaving uncertainty about causal pathways in an individual client.

Evidence specific to martial arts and boxing

Moore et al. (2020) synthesised 14 studies and reported a small pooled benefit for wellbeing and a moderate pooled effect on internalising mental health outcomes. Heterogeneity was substantial, particularly for internalising outcomes, and the pooled aggression finding was not statistically significant.

Ciaccioni et al. (2024) reviewed 72 observational adult studies, comprising 70 cross-sectional and two longitudinal studies. Findings varied across self-related, emotional and cognitive outcomes. The designs limit conclusions about whether differences resulted from training, pre-existing characteristics or continued participation by people who found the activity helpful.

Non-contact boxing is a closer comparison for interventions using pads, bags and combinations. Bozdarov et al. (2023) identified 16 studies across diverse populations and delivery formats. In 56%, boxing was supplemented by components such as mentoring, mindfulness or psychological strategies. The review maps promising applications, but the mixture of designs and combined interventions prevents a firm estimate of boxing’s independent contribution.

Weiss et al. (2025) provide a recent clinical example. Their 24-person pilot examined taekwondo and mindfulness within a dialectical behaviour therapy intensive outpatient programme. Participants reported favourable acceptability and immediate affective changes. The small within-subject study, conducted during ongoing treatment, supports feasibility and further investigation.

Together, these findings support studying specified practices in defined contexts. They leave open which components contribute to change and how outcomes compare with other meaningful activities.

Lifestyle interventions within NeuroAffective-CBT

Lifestyle interventions address recurring conditions of daily life that affect wellbeing and participation. Sleep, movement, nutrition, hydration and recovery can influence one another. Fatigue may reduce the capacity to attend a class, while an excessively demanding training schedule may interfere with rest. These conditions belong within formulation when they contribute to difficulties or limit engagement with treatment.

Within NeuroAffective-CBT (NA-CBT), TED refers to Tiredness–Exercise–Diet. Mirea’s exercise discussion emphasises individualisation and meaningful participation (Mirea, 2025a), while the applied TED account places sleep, movement and nutrition within therapeutic planning (Mirea, 2025b). Practical questions include whether the person is sufficiently rested, whether the activity fits their capacity and whether training supports daily life or becomes another demand they feel compelled to meet.

Mirea’s (2026) Pendulum-Effect account describes avoidance, overcompensation and capitulation as protective responses within a formulation concerned with shame. In training, these might appear as withdrawing when mistakes become visible, exercising punitively to prove worth or accepting an identity of permanent incapability. Embodied rehearsal offers a proposed way of practising a different response while difficult experience remains present.

This formulation helps distinguish occasions when demands should be reduced from occasions when a prediction maintaining avoidance could usefully be tested. Rest and adaptation may be appropriate on one occasion; on another, the useful learning may be that discomfort is compatible with chosen action.

Meichenbaum’s Roadmap to Resilience places physical resources alongside interpersonal, emotional, cognitive, behavioural and spiritual resources (Meichenbaum, n.d.). This broader account keeps strengths, relationships and meaning visible alongside physical capability.

Matching movement to the individual

Activity selection begins with interests and circumstances. What has the person enjoyed previously? Would they prefer technical learning, rhythm, independent practice, cooperation or competition? What does a particular sport represent to them? Physical health, disability and previous injury matter alongside cultural identity, cost, transport and the available training environment.

The useful psychological question is often what the person needs an opportunity to practise. Achievable progression may help someone who expects failure. A supportive class may provide opportunities to be seen trying and receive feedback. Partner work might allow someone to express a preference, while regular shared activity may offer structure and repeated contact to someone experiencing isolation.

These possibilities do not prescribe a sport for a diagnosis. One person with social anxiety may appreciate interaction organised around a shared task; another may initially prefer predictable individual instruction. Someone seeking confidence may find a suitable opportunity in martial arts, dance, climbing or resistance training. Formulation clarifies what confidence means and how the setting might help develop it.

Personal meaning and enjoyment also matter for continuation. Teixeira et al. (2012) reviewed 66 studies of exercise through self-determination theory. Their findings supported relationships between autonomous motivation and participation, with enjoyment and intrinsic motivation particularly relevant to longer-term adherence. Much of the evidence was observational.

Interest may develop through skill, companionship or discovering that movement feels different from what was anticipated. Initial discomfort does not necessarily indicate a poor match, while persistent difficulty should remain open to review. Choosing another instructor, format or activity can be a successful outcome of collaborative planning.

Why martial arts may be a useful resource

Martial arts can bring technical learning, bodily effort and interpersonal negotiation into the same activity. Depending on the practice, participants must manage distance, coordinate movement, respond to another person and communicate the intensity they are willing to accept. These features can make questions of capability, control and boundaries immediately available for reflection.

Their significance remains individual. Someone who habitually withdraws may value discovering that they can take up space and act decisively. A person who overcompensates through excessive effort may benefit from practising restraint, accepting correction or stopping at an agreed point. Another may find predictable partner work an accessible route into cooperation and connection.

These are proposed learning opportunities. Their usefulness depends on preference, instruction and interpretation. The range of available formats also allows adaptation: individual non-contact practice, recreational group training and partner exercises need not involve the same demands.

The clinical rationale rests on the fit between these opportunities and the person’s formulation. Martial practice becomes informative when it allows relevant responses to be practised and reviewed.

Confidence, shame, assertiveness and responses to mistakes

Confidence may develop through supported action. A simple movement becomes a short combination, and repetition makes progress visible. Someone expecting complete failure may discover that they can learn part of a task and return after difficulty.

Technical mastery, specific self-efficacy and global self-worth nevertheless remain distinguishable. A person can acquire skill while continuing to interpret mistakes as evidence of inadequacy. Shame and self-criticism therefore warrant attention when relevant to the formulation. Compassion-focused therapy provides one example of explicitly addressing these difficulties (Leaviss and Uttley, 2015).

Training offers frequent encounters with being inexperienced. Sequences are forgotten and coordination develops unevenly. A behavioural experiment could examine a prediction that an ordinary mistake will lead to rejection. It requires an agreed prediction, suitable practice and review of what happened, including the participant’s interpretation and protective strategies.

Progression can vary through complexity, speed, effort or social visibility. These dimensions need not increase together. For someone whose worth depends on achievement, a useful task might involve receiving correction without self-attack or stopping at an agreed level.

Assertiveness can also be rehearsed through asking for clarification, requesting lighter contact or declining an additional round. The instructor’s response becomes part of the learning. Physical performance provides only a partial account of progress when the intended change concerns communicating a need or recovering from a mistake.

Manageable challenge and coping rehearsal

Exertion, uncertainty and frustration can provide occasions to practise coping. The first challenge may be entering the venue; later tasks might involve an unfamiliar combination or remaining engaged after an error.

Meichenbaum and Deffenbacher’s (1988) stress inoculation framework offers a useful structure: develop a shared understanding, acquire and rehearse coping skills, then apply and review them in relevant situations. This directs attention to preparation and coping choices before increasing demand.

Brief self-instructions such as “slow the sequence”, “ask for clarification” or “reset and try again” connect language with available actions. Hatzigeorgiadis et al. (2011) found that self-talk interventions improved sport performance. Their wider therapeutic contribution needs assessment against the intended clinical outcome.

Physical endurance, anxiety sensitivity and distress tolerance are distinct. LeBouthillier and Asmundson (2015) found that one aerobic exercise session reduced anxiety sensitivity without improving distress tolerance or intolerance of uncertainty. Their later four-week trial involving 48 participants reported benefits for distress tolerance and intolerance of uncertainty following resistance training (LeBouthillier and Asmundson, 2017). Different activities and doses may influence different processes.

Craske et al. (2014) emphasise expectancy violation and new learning within exposure rather than requiring fear to diminish during a session. Movement could provide a setting for such learning where a relevant fear has been identified. The task might examine whether activation can be experienced while retaining choice. Increased intensity alone is an inadequate measure of therapeutic progress.

Attention, flexibility and personal meaning

Movement sequences require attention to targets, balance, timing and instructions. A participant can notice distraction or self-criticism and return to the next action. This provides a concrete setting for attentional practice, with transfer beyond the task requiring review.

Acceptance and commitment therapy offers language for willingness, defusion and values-guided action. Macri and Rogge (2024) review psychological flexibility and inflexibility processes within ACT. Applied here, willingness might involve allowing embarrassment while trying a chosen task; defusion might involve noticing “everyone thinks I am useless” without treating it as an instruction to leave. Flexibility also includes adapting or declining when those choices serve the person’s goals.

Dialectical behaviour therapy distinguishes mindfulness, emotion regulation, distress tolerance and interpersonal effectiveness (Chapman, 2006). These distinctions help specify whether a task concerns attending, modifying activation, enduring distress or communicating a need.

Absorption during training may provide welcome relief. Its function deserves review if movement becomes the only way to avoid painful thoughts. Psychological flexibility concerns the range of responses available, including the ability to rest and engage with difficulties elsewhere.

Meaning should likewise be elicited directly. Practice may represent cooperation, capability or community membership; it may also become organised around punishment or approval. Park (2010) distinguishes efforts to make meaning from meanings actually achieved. Attendance and enjoyment therefore provide incomplete evidence of changes in longstanding beliefs or identity.

Bodily activation, breathing and recovery

Training may make breath-holding, muscular bracing, fatigue and rising arousal more noticeable. A participant can practise adjusting effort, recognising tension and responding to changing demands.

Competition research demonstrates that these demands can be accompanied by substantial physiological activation. Slimani et al. (2018) identified increases in cortisol, adrenaline and noradrenaline following striking combat events compared with pre-combat measurements. These findings concern acute responses to competition and cannot establish how every recreational participant experiences training or whether participation produces lasting improvements in regulation.

Our observations suggest that increasing familiarity may sometimes be accompanied by less unnecessary tension, more economical movement and better-paced effort. We propose that this can provide a setting for learning to act purposefully while activated. This interpretation concerns observable responses; particular hormone or neurotransmitter levels cannot be inferred from performance.

Sometimes the useful task involves reducing unnecessary activation. At other times, it involves discovering that activation is tolerable. Instructions should fit the therapeutic purpose and physical demand.

Breathing during movement differs from a separate paced-breathing practice. Balban et al. (2023) examined brief daily structured breathing protocols, including cyclic sighing, and reported effects on mood and respiratory rate. Fincham et al. (2023) found that coherent breathing at approximately 5.5 breaths per minute did not outperform a matched 12-breaths-per-minute practice on mental health and wellbeing outcomes in 400 participants. These studies concern particular breathing protocols rather than breathing instructions during striking combinations.

During exertion, ventilation must accommodate physical demand. Recovery breathing can be explored separately and reviewed for whether it supports participation. A practice may become restrictive if the person concludes that discomfort must disappear before action is possible.

Recovery also concerns how a session ends, rest between training days and responses to fatigue. These observations help establish whether exercise supports wider functioning or becomes punitive. Recovery should remain adaptable rather than become another performance standard.

Belonging, coaching and interpersonal boundaries

A supportive club can offer repeated contact around shared activity. Connection may develop without immediate personal disclosure. Predictable routines, recognition and constructive feedback may make participation easier, depending on the interpersonal environment.

For people with histories of coercion or interpersonal threat, proximity, commands, touch or unpredictability may carry particular significance. Preparation should establish what participation involves, available adaptations and how consent can be withdrawn. An instructor who respects a request can support learning that needs may be expressed without rejection.

A first step may involve contacting an instructor, observing a class or trying a short introduction. Review should address experience and interpretation. Did the anticipated difficulty occur? Did assistance feel useful or become further evidence of inadequacy? Was there interest or enjoyment?

An unpleasant experience may justify another setting. It should not automatically be interpreted as avoidance to overcome. The suitability of the environment remains part of the formulation.

A hypothetical clinical illustration

The following illustration describes proposed professional reasoning rather than an actual patient account.

An adult interested in boxing avoids asking for help at work and expects that expressing a need will provoke irritation. They also stop unfamiliar activities after mistakes, interpreting difficulty as evidence of incompetence. Assessment explores physical health, previous learning experiences, the meaning of bodily activation and whether current relationships contain actual hostility. It identifies strengths, including an interest in technical skills and previous occasions of effective communication.

A shared hypothesis is that remaining silent provides immediate relief while preventing learning about how others respond to reasonable requests. The client chooses a short non-contact introduction with an instructor who welcomes adaptation. The proposed experiment concerns requesting a slower pace during a manageable combination.

Before practice, clinician and client specify the prediction and rehearse a credible request. Afterwards, review examines whether the request was made, how the instructor responded and how that response was interpreted. If a respectful response is dismissed as “only because this is therapy”, the interpretation becomes a question to investigate. A dismissive response would require reconsideration of both the prediction and the suitability of the setting.

An agreed experiment outside training might involve asking a colleague to clarify an instruction. Review would distinguish willingness, actual behaviour and confidence, which may change at different rates. The example shows how a chosen physical activity can provide a setting for testing a prediction and rehearsing agency.

Evaluating learning beyond training

Evaluation should match the formulation. Technical competence, specific self-efficacy, global self-worth, self-critical responding and everyday participation are related but distinct outcomes. Session review can record predictions, coping choices, interpretation and actual behaviour. Suitable symptom or wellbeing measures can complement personally meaningful goals.

Learning outside training requires further opportunities for practice. Someone who returns to a drill after an error might revisit an activity they previously abandoned. A participant who communicates a limit may examine where else expressing a preference matters. These are further experiments with outcomes to review.

Follow-up should examine whether changes persist, whether participation continues and what happens during interruptions. Attendance, adaptations, adverse experiences and discontinuation provide information about fit. Missed sessions and fluctuating energy should be anticipated within a realistic routine.

The client’s explanation should remain distinguishable from the clinician’s inference. Reported improvement is valuable information, while causal conclusions require stronger evidence.

Physical risk and professional responsibilities

Contact combat sports introduce injury exposures requiring explicit consideration. Head impacts and concussion are material concerns; the Association of Ringside Physicians has emphasised the particular demands of concussion management in this setting (Neidecker et al., 2019).

Non-contact practice can provide movement and learning opportunities without making head contact part of the therapeutic task, but it is not injury-free. Grappling, kicking and pad work place demands on joints, balance and physical capacity.

Selection and progression should account for health, previous injury and current capacity, with appropriate professional input where needed. Participation should permit stopping and distinguish ordinary effort from pain or symptoms requiring reassessment.

Psychotherapy and martial arts instruction require separate competencies. A clinician using physical tasks needs relevant competence and suitable arrangements, or collaboration with a qualified instructor. Clear roles, informed consent, confidentiality and agreed communication help participants understand what is offered.

Combining roles requires attention to whether the person feels free to disagree or stop. Information shared with an instructor should be limited to what is needed for agreed coordination and shared with the client’s consent.

Limitations and research priorities

This selective review combines heterogeneous exercise findings, discipline-specific research and conceptual accounts. Its source selection may omit relevant evidence, and it provides no pooled estimate or formal appraisal of the literature as a whole. Observations and individual experiences inform the clinical proposal but do not establish treatment effectiveness.

Smith and Merwin (2021) describe interacting biological and behavioural pathways through which exercise may influence mental health. General findings concerning cognition, inflammation or neuroplasticity cannot establish that a particular martial arts programme produces the same changes or that those changes explain clinical improvement.

A useful comparative question is whether explicit formulation-guided instruction adds benefit to otherwise similar physical practice. Research could compare matched programmes with and without agreed psychological tasks, accounting for encouragement, contact time, progression and expectations. Comparisons with other meaningful activities could examine shared contributions such as mastery and social connection.

Individualisation also deserves study. Does matching preferences and therapeutic goals improve engagement? Which features of instruction influence participation? When should the initial choice be revised?

Prospective assessment should measure intended outcomes and candidate processes over time. Changes in proposed mechanisms should precede the outcomes they are intended to explain, with alternative explanations considered.

Carefully planned single-case experimental designs may help investigate delivery before larger trials. Follow-up, concurrent care, practitioner competence and less favourable experiences should be reported. Including people who discontinue or find the activity unsuitable would improve understanding of practical limits.

Conclusion

The available evidence suggests that martial arts training can support mental health for some participants, although benefits vary across practices, populations and training environments. Its place within individualised care depends on what participation offers the particular person.

Martial arts bring physical activity, technical learning and interpersonal exchange together, creating opportunities to practise choice during manageable challenge. Therapeutic goals may concern developing confidence, responding differently to mistakes, communicating limits, coping with activation or reconnecting with others. Clinical usefulness depends on matching these opportunities to the person’s formulation and reviewing what becomes available beyond training.

The wider exercise literature supports therapeutic relevance, while the specific outcomes and mechanisms of martial arts require further investigation. Our observations inform a clinical proposal: chosen and appropriately adapted practice may provide a setting in which people test expectations, develop agency and participate more fully in a life they value.

References

Balban, M.Y., Neri, E., Kogon, M.M., Weed, L., Nouriani, B., Jo, B., Holl, G., Zeitzer, J.M., Spiegel, D. and Huberman, A.D. (2023) ‘Brief structured respiration practices enhance mood and reduce physiological arousal’, Cell Reports Medicine, 4(1), article 100895. Available at: https://doi.org/10.1016/j.xcrm.2022.100895.

Bozdarov, J., Jones, B.D.M., Daskalakis, Z.J. and Husain, M.I. (2023) ‘Boxing as an intervention in mental health: a scoping review’, American Journal of Lifestyle Medicine, 17(4), pp. 589–600. Available at: https://doi.org/10.1177/15598276221124095.

Bruce Lee Enterprises (2017) ‘#78 Motivation when you’re stuck’, Bruce Lee Podcast, 27 December. Available at: https://brucelee.com/podcast-blog/2017/12/27/78-motivation-when-youre-stuck (Accessed: 23 October 2026).

Bruce Lee Enterprises (n.d.) ‘The philosophies’. Available at: https://brucelee.com/philosophies/ (Accessed: 23 October 2026).

Chapman, A.L. (2006) ‘Dialectical behavior therapy: current indications and unique elements’, Psychiatry (Edgmont), 3(9), pp. 62–68. Available at: https://pubmed.ncbi.nlm.nih.gov/20975829/.

Ciaccioni, S., Castro, O., Bahrami, F., Tomporowski, P.D., Capranica, L., Biddle, S.J.H., Vergeer, I. and Pesce, C. (2024) ‘Martial arts, combat sports, and mental health in adults: a systematic review’, Psychology of Sport and Exercise, 70, article 102556. Available at: https://doi.org/10.1016/j.psychsport.2023.102556.

Craske, M.G., Treanor, M., Conway, C.C., Zbozinek, T. and Vervliet, B. (2014) ‘Maximizing exposure therapy: an inhibitory learning approach’, Behaviour Research and Therapy, 58, pp. 10–23. Available at: https://doi.org/10.1016/j.brat.2014.04.006.

Fincham, G.W., Strauss, C. and Cavanagh, K. (2023) ‘Effect of coherent breathing on mental health and wellbeing: a randomised placebo-controlled trial’, Scientific Reports, 13, article 22141. Available at: https://doi.org/10.1038/s41598-023-49279-8.

Foundation of the Hellenic World (n.d.) ‘Introduction of the events to the Olympic Games program’. Available at: https://www.ime.gr/olympics/ancient/en/203b1.html (Accessed: 23 October 2026).

Fuller, J.R. (1988) ‘Martial arts and psychological health’, British Journal of Medical Psychology, 61(4), pp. 317–328. Available at: https://doi.org/10.1111/j.2044-8341.1988.tb02794.x.

Gordon, B.R., McDowell, C.P., Hallgren, M., Meyer, J.D., Lyons, M. and Herring, M.P. (2018) ‘Association of efficacy of resistance exercise training with depressive symptoms: meta-analysis and meta-regression analysis of randomized clinical trials’, JAMA Psychiatry, 75(6), pp. 566–576. Available at: https://doi.org/10.1001/jamapsychiatry.2018.0572.

Hatzigeorgiadis, A., Zourbanos, N., Galanis, E. and Theodorakis, Y. (2011) ‘Self-talk and sports performance: a meta-analysis’, Perspectives on Psychological Science, 6(4), pp. 348–356. Available at: https://doi.org/10.1177/1745691611413136.

Leaviss, J. and Uttley, L. (2015) ‘Psychotherapeutic benefits of compassion-focused therapy: an early systematic review’, Psychological Medicine, 45(5), pp. 927–945. Available at: https://doi.org/10.1017/S0033291714002141.

LeBouthillier, D.M. and Asmundson, G.J.G. (2015) ‘A single bout of aerobic exercise reduces anxiety sensitivity but not intolerance of uncertainty or distress tolerance: a randomized controlled trial’, Cognitive Behaviour Therapy, 44(4), pp. 252–263. Available at: https://doi.org/10.1080/16506073.2015.1028094.

LeBouthillier, D.M. and Asmundson, G.J.G. (2017) ‘The efficacy of aerobic exercise and resistance training as transdiagnostic interventions for anxiety-related disorders and constructs: a randomized controlled trial’, Journal of Anxiety Disorders, 52, pp. 43–52. Available at: https://doi.org/10.1016/j.janxdis.2017.09.005.

Macri, J.A. and Rogge, R.D. (2024) ‘Examining domains of psychological flexibility and inflexibility as treatment mechanisms in acceptance and commitment therapy: a comprehensive systematic and meta-analytic review’, Clinical Psychology Review, 110, article 102432. Available at: https://doi.org/10.1016/j.cpr.2024.102432.

Mai, S. (2015) ‘Kiai’, translated by S. Pranin, Aikido Journal, 6 January. Available at: https://aikidojournal.com/2015/01/06/kiai-by-sakura-mai/ (Accessed: 23 October 2026).

Meichenbaum, D. (n.d.) Roadmap to Resilience. Available at: https://roadmaptoresilience.wordpress.com/ (Accessed: 23 October 2026).

Meichenbaum, D.H. and Deffenbacher, J.L. (1988) ‘Stress inoculation training’, The Counseling Psychologist, 16(1), pp. 69–90. Available at: https://doi.org/10.1177/0011000088161005.

Mirea, D. (2025a) ‘Physical exercise, sports science and mental health’, The NeuroAffective-CBT Journal, TED Series, 31 October. Available at: https://neuroaffectivecbt.com/2025/10/31/ted-series-part-vii-physical-exercise-sports-science-and-mental-health/ (Accessed: 23 October 2026).

Mirea, D. (2025b) ‘TED in NeuroAffective-CBT: An applied self-regulation framework for enhancing emotional well-being through sleep, movement, and nutrition’. Available at: https://neuroaffectivecbt.com/2025/12/10/ted-in-neuroaffective-cbt-an-applied-self-regulation-framework-for-enhancing-emotional-well-being-through-sleep-movement-and-nutrition/ (Accessed: 23 October 2026).

Mirea, D. (2026) ‘Beyond fake it till you make it: The Pendulum-Effect, embodied rehearsal and the development of the Integrated-Self’. Available at: https://neuroaffectivecbt.com/2026/09/03/beyond-fake-it-till-you-make-it-the-pendulum-effect-embodied-rehearsal-and-the-development-of-the-integrated-self/ (Accessed: 23 October 2026).

Moore, B., Dudley, D. and Woodcock, S. (2020) ‘The effect of martial arts training on mental health outcomes: a systematic review and meta-analysis’, Journal of Bodywork and Movement Therapies, 24(4), pp. 402–412. Available at: https://doi.org/10.1016/j.jbmt.2020.06.017.

National Qigong Association (2025) ‘The 3 Dantian: An in-depth look’, 20 January. Available at: https://www.nqa.org/library/the-3-dantian-an-in-depth-look (Accessed: 23 October 2026).

Neidecker, J., Sethi, N.K., Taylor, R. et al. (2019) ‘Concussion management in combat sports: consensus statement from the Association of Ringside Physicians’, British Journal of Sports Medicine, 53(6), pp. 328–333. Available at: https://doi.org/10.1136/bjsports-2017-098799.

Noetel, M., Sanders, T., Gallardo-Gómez, D., Taylor, P., Del Pozo Cruz, B., van den Hoek, D., Smith, J.J., Mahoney, J., Spathis, J., Moresi, M., Pagano, R., Pagano, L., Vasconcellos, R., Arnott, H., Varley, B., Parker, P., Biddle, S. and Lonsdale, C. (2024) ‘Effect of exercise for depression: systematic review and network meta-analysis of randomised controlled trials’, BMJ, 384, article e075847. Available at: https://doi.org/10.1136/bmj-2023-075847.

Park, C.L. (2010) ‘Making sense of the meaning literature: an integrative review of meaning making and its effects on adjustment to stressful life events’, Psychological Bulletin, 136(2), pp. 257–301. Available at: https://doi.org/10.1037/a0018301.

Salkovskis, P.M., Sighvatsson, M.B. and Sigurdsson, J.F. (2023) ‘How effective psychological treatments work: mechanisms of change in cognitive behavioural therapy and beyond’, Behavioural and Cognitive Psychotherapy, 51(6), pp. 595–615. Available at: https://doi.org/10.1017/S1352465823000590.

Shahar, M. (2008) The Shaolin Monastery: History, Religion, and the Chinese Martial Arts. Honolulu: University of Hawai‘i Press. Available at: https://doi.org/10.1515/9780824865023.

Singh, B., Olds, T., Curtis, R., Dumuid, D., Virgara, R., Watson, A., Szeto, K., O’Connor, E., Ferguson, T., Eglitis, E., Miatke, A., Simpson, C.E. and Maher, C. (2023) ‘Effectiveness of physical activity interventions for improving depression, anxiety and distress: an overview of systematic reviews’, British Journal of Sports Medicine, 57(18), pp. 1203–1209. Available at: https://doi.org/10.1136/bjsports-2022-106195.

Slimani, M., Paravlic, A.H., Chaabene, H., Davis, P., Chamari, K. and Cheour, F. (2018) ‘Hormonal responses to striking combat sports competition: a systematic review and meta-analysis’, Biology of Sport, 35(2), pp. 121–136. Available at: https://doi.org/10.5114/biolsport.2018.71601.

Smith, P.J. and Merwin, R.M. (2021) ‘The role of exercise in management of mental health disorders: an integrative review’, Annual Review of Medicine, 72, pp. 45–62. Available at: https://doi.org/10.1146/annurev-med-060619-022943.

Teixeira, P.J., Carraça, E.V., Markland, D., Silva, M.N. and Ryan, R.M. (2012) ‘Exercise, physical activity, and self-determination theory: a systematic review’, International Journal of Behavioral Nutrition and Physical Activity, 9, article 78. Available at: https://doi.org/10.1186/1479-5868-9-78.

Twemlow, S.W. and Sacco, F.C. (1998) ‘The application of traditional martial arts practice and theory to the treatment of violent adolescents’, Adolescence, 33(131), pp. 505–518. Available at: https://pubmed.ncbi.nlm.nih.gov/9831868/.

Weiss, E.R., Hart-Derrick, V.R., Ramsay-Patel, T., Barnes, S.E., Anderson, H., Gatti, C. and Davis, M.T. (2025) ‘Acceptability and feasibility of a Taekwondo mindful movement intervention in dialectical behavior therapy’, Journal of Behavioral and Cognitive Therapy, 35(2), article 100527. Available at: https://doi.org/10.1016/j.jbct.2025.100527.

White, R.L., Vella, S., Biddle, S., Sutcliffe, J., Guagliano, J.M., Uddin, R., Burgin, A., Apostolopoulos, M., Nguyen, T., Young, C., Taylor, N., Lilley, S. and Teychenne, M. (2024) ‘Physical activity and mental health: a systematic review and best-evidence synthesis of mediation and moderation studies’, International Journal of Behavioral Nutrition and Physical Activity, 21(1), article 134. Available at: https://doi.org/10.1186/s12966-024-01676-6.

About the Authors

Daniel Mirea is the founder of NeuroAffective-CBT, an accredited CBT therapist and a university lecturer. He is also a trained martial artist and a sports-psychotherapy consultant.

Chris People holds a black belt in traditional Japanese martial arts and teaching awards in combat sports and Brazilian martial arts. He trains both adults and children and is an accredited Hypno-CBT therapist and trainer. He is also undertaking training in psychotherapy.

Declaration of Interests and Article Scope

Daniel Mirea founded NeuroAffective-CBT, which provides a conceptual perspective discussed in this article. The clinical proposals draw partly on the authors’ observations and personal experiences of training. No original patient data are reported, and the clinical illustration is hypothetical.

Beyond ‘Fake It Till You Make It’: The Pendulum-Effect, Embodied Rehearsal and the Development of the Integrated-Self

Daniel Mirea (September, 2026)
| The NeuroAffective-CBT® Journal | 

Central proposition: We do not always need to feel confident before acting courageously. Carefully graded action can provide an embodied rehearsal through which affect tolerance, agency and self-trust may gradually develop.

She Knew What She Wanted to Say

Anna had prepared for the meeting more thoroughly than anyone else in the room.

She had read the papers twice, highlighted the relevant figures and anticipated several questions her colleagues might ask. The night before, she had rehearsed different versions of what she wanted to say. By the time the meeting began, there was little about the subject that she did not understand.

Yet when the opportunity to contribute arrived, Anna remained silent.

She felt the change in her body before she could put it into words. Her chest tightened, her throat seemed to narrow and her shoulders became rigid. While another colleague was speaking, Anna stopped listening fully and began monitoring herself.

When should I come in? What if I misunderstand the question? What if they realise that I am not as capable as they think?

She waited for the moment when she would feel certain enough to speak. It did not come.

When a colleague made a point similar to the one Anna had prepared, she nodded in agreement and told herself that there was no longer any reason to contribute. For a few seconds, she felt relieved. The danger of being exposed had passed.

The relief did not last. After the meeting, Anna replayed the conversation, criticised herself for remaining silent and treated the incident as evidence about her identity. She was no longer thinking, I found it difficult to speak in that meeting. She was thinking, I am weak. I am inadequate. This is who I am.

Her response was to prepare even more intensely for the next meeting.

Anna’s colleagues would probably have described her as conscientious, capable and exceptionally well prepared. They would not have seen the cycle beneath her competence: the attempt to overcome self-doubt through perfectionism, the withdrawal when certainty remained impossible and the self-attack that followed.

These responses were understandable in the context of Anna’s history. She had learned early that approval followed achievement and that mistakes attracted criticism. Careful preparation had helped her succeed; monitoring other people had helped her detect changes in mood; silence had sometimes protected her from humiliation. The difficulty was that these strategies had become so thoroughly rehearsed that they felt less like strategies and more like aspects of her personality.

When Anna entered therapy, she said that she wanted to become more confident. What she meant was that she wanted the anxiety to disappear before she acted. She imagined that confident people spoke because they felt certain, while she remained silent because something essential was missing within her.

Her first therapeutic experiment was deliberately modest. She was not asked to dominate a meeting, deliver a flawless presentation or behave as though she felt no anxiety. She was asked to prepare one genuine question and raise it within the first ten minutes.

Before rehearsing the question, Anna noticed what happened when she imagined herself speaking: her shoulders lifted, her jaw tightened and she felt an urge to delay. Rather than treating these reactions as proof that she should remain silent, she practised orienting towards the room, feeling the support of the chair and allowing a slower exhalation.

She then rehearsed the question aloud. At first, her voice was quiet and apologetic, and she prefaced the question with several explanations designed to protect her from being wrong. Gradually, she experimented with saying the same words more simply. She was not pretending to be another person. She was using her own voice to practise a response that her established protective system rarely permitted.

At the next meeting, Anna’s chest tightened again. The familiar prediction returned: Wait until you are completely certain.

This time, she asked the question.

She did not experience a sudden transformation. She did not feel fearless and nobody applauded. The question was answered and the meeting continued.

That ordinary continuation mattered. Anna had spoken while feeling activated. Nobody responded with contempt. Her body mobilised and then began to recover. Her specific prediction of humiliation had not occurred, but neither had she proved that criticism would never happen. She had learned something more credible: uncertainty did not make participation impossible.

This was not ‘faking it’. The anxiety was real, the bodily activation was real and the old prediction was still present. The action was also real.

Perhaps the more useful instruction is therefore:

Do not fake the feeling. Practise the action, remain connected to the body, observe what happens and allow the experience to revise what seems possible.

Anna’s experience will accompany the ideas that follow. Her movement between perfectionistic overpreparation, avoidance and self-attack illustrates the Pendulum-Effect Formulation. Her use of voice, posture, attention and action shows why rehearsal is more than positive thinking. Most importantly, her increasing ability to participate while remaining connected to her experience demonstrates how an unfamiliar response may gradually become available within the Integrated-Self.

From Pretence to Rehearsal

The phrase ‘fake it till you make it’ is memorable because it reverses a common assumption: that an internal state must arrive before action becomes possible. When I feel confident, I will speak. When my anxiety disappears, I will travel. When I believe I am worthy, I will allow myself to be visible.

Waiting for the preferred feeling can, however, become part of the avoidance cycle. The person receives little corrective information, the feared situation remains unfamiliar and the old self-concept is repeatedly confirmed.

The alternative is not dishonesty. A person can acknowledge, ‘I feel anxious and part of me expects rejection’, while also practising one behaviour associated with agency: making eye contact, expressing a preference, asking a question or remaining present long enough to discover what happens. Confidence may be incomplete, but the action is genuine.

This distinction matters clinically. Pretence requires the person to deny or conceal their experience. Rehearsal asks them to remain in contact with that experience while trying a response that has previously been inhibited. It is not a demand to feel differently on command; it is an opportunity to discover whether feeling anxious, ashamed or uncertain necessarily determines what happens next.

Why Embodiment Still Matters

Some traditional psychological language implies a one-way sequence in which thought creates emotion and the body merely displays the result. Embodied and grounded approaches complicate this picture. Cognitive and affective processes draw upon perception, movement, interoception and situated interaction with the environment. Bodily activity therefore participates in experience rather than serving only as its outward consequence (Barsalou, 2008; Niedenthal, 2007).

Anna’s bodily activation, threat predictions, shame, narrowed attention and silence formed an interacting state. Her tightening chest did not simply report a conclusion her mind had already reached; it contributed to an experience in which participation felt dangerous and withdrawal felt protective.

This does not mean that changing posture automatically transforms identity, or that imagination, performance and lived reality are neurologically interchangeable. Bodily manipulations can influence emotional experience, but their effects may be small, variable and dependent upon context. Research on facial feedback provides a useful warning: the overall effect appears detectable but modest, and outcomes differ according to the task and the emotional experience being measured (Coles, Larsen and Lench, 2019; Coles et al., 2022).

Embodied rehearsal makes a more limited and clinically useful claim. When a person rehearses a boundary or asks a question aloud, the intervention involves more than substituting one thought for another. The person must use their actual voice, regulate breath and muscular activation, direct attention outwards, tolerate the affect evoked by being visible and recover afterwards. The body is neither a shortcut nor a programmable prop; it is part of the situation in which new action and learning become possible.

Acting as Rehearsal Rather Than Pretence

Theatre makes the embodied nature of psychological experience unusually visible. An actor does not learn a role through abstract interpretation alone. The role is organised repeatedly through voice, breath, posture, timing, movement, attention, relationships and responses to the environment. Through rehearsal, the actor temporarily inhabits a behavioural and affective configuration that may initially feel unfamiliar.

Lev Vygotsky recognised that acting raises a psychologically important question: must actors genuinely experience the emotions they portray, or can emotion emerge through the organisation of performance? Discussing Stanislavski’s system and Diderot’s ‘paradox of the actor’, Vygotsky situated emotional experience within a wider relationship among role, action, social meaning, theatrical tradition and audience (Vygotsky, 1999; original work published 1932). His analysis cautions against treating performed and lived emotions as either completely separate or neurologically interchangeable.

Within a different clinical tradition, J. L. Moreno placed action, role and enactment at the centre of psychological change (Moreno, 1946, 1947). In psychodrama, clients do not merely describe an experience. They enter a structured dramatic space in which relationships, conflicts, memories and possible responses can be enacted. Role reversal, doubling, mirroring and role training allow previously unavailable perspectives and behavioural positions to be experienced, observed and rehearsed (Cruz et al., 2018; Moreno, 1946).

Moreno proposed that the self emerges through the roles a person develops and performs, describing role as a bridge between psychiatry, psychology and sociology (Moreno, 1946, 1961). Psychological development, from this perspective, does not require the discovery of one fixed and supposedly authentic identity concealed beneath behaviour. It may involve expanding the person’s role repertoire and increasing the capacity to respond spontaneously and creatively rather than remaining confined within rigid, overlearned patterns (Moreno, 1947, 1955).

A new role does not require a person to become somebody else. It may provide temporary access to an inhibited aspect of their existing repertoire. Someone organised around compliance may rehearse setting a boundary. Someone governed by shame may practise being visible. Someone who anticipates helplessness may experiment with acting from a position of agency.

What initially feels artificial may feel unfamiliar precisely because it contradicts an established protective pattern. A person who has spent years accommodating others may experience an ordinary boundary as unnatural. Someone accustomed to silence may describe speaking with authority as ‘not feeling like me’. Yet familiarity is not the same as authenticity. Sometimes what feels most familiar is simply what has been rehearsed for the longest.

Moreno’s concept of surplus reality is relevant here. The psychodramatic space allows a person to enact what did not happen, what has not yet happened or what could not safely be expressed in everyday life (Moreno, 1965). A boundary may finally be spoken or a more agentic position temporarily inhabited. The enactment is not equivalent to lived reality, but it may provide an experiential bridge between what the person currently predicts and what they may gradually become able to tolerate and perform.

Contemporary drama-based interventions employ related processes, including role, narrative, enactment, distancing and witnessed performance. Reviews report promising findings across psychosocial, emotional and behavioural outcomes, while also identifying considerable variation in populations, interventions, methods and study quality (Berghs et al., 2022; Jiang et al., 2023). These findings support careful clinical exploration; they do not establish that performance reliably installs safety, autonomy or a new identity within the nervous system.

From Psychodrama to Behavioural Rehearsal

Moreno was not the only early clinician to place action before emotional readiness. In Conditioned Reflex Therapy, Andrew Salter argued that change could be facilitated through deliberate practice of expressive and assertive behaviour, including speaking directly about feelings, using the first-person pronoun ‘I’, expressing disagreement and accepting praise (Salter, 1949). People were not expected to wait until they felt naturally assertive; behaviour was practised first, including beyond the consulting room, so that experience and interpersonal feedback could begin to modify established patterns.

Salter’s learning-based approach was theoretically distinct from Moreno’s emphasis on role, encounter and dramatic enactment, but both challenged the assumption that insight, confidence or emotional readiness must precede behaviour. Salter explained change through Pavlovian concepts of cortical excitation and inhibition; these ideas are historically important but are not established mechanisms within contemporary neuroscience.

Vygotsky, Moreno and Salter therefore provide different perspectives that can be brought into dialogue with a NeuroAffective-CBT® (NA-CBT) account of embodied rehearsal. They do not validate NA-CBT or establish its mechanisms. They help situate its central proposition within a longer history of understanding action, role and experience as mutually influential.

The Pendulum Beneath the Performance

The Pendulum-Effect Formulation identifies the protective pattern that restricts action; embodied rehearsal creates an opportunity to practise a different response; reflection and repetition allow that response gradually to become available within the Integrated-Self.

Figure 1. The Pendulum-Effect Formulation: Overcompensation, Avoidance and Capitulation represent different protective positions organised around a shared shame-based prediction. Embodied rehearsal, graded action, reflection and repetition provide an alternative agentic pathway through which a different response may gradually become available within the Integrated-Self.

In anticipation of shame, Anna moved towards Overcompensation: preparing excessively, mentally rehearsing every sentence and attempting to eliminate the possibility of error. When complete certainty remained unattainable, she shifted towards Avoidance: delaying her contribution, weakening what she wanted to say or remaining silent. After the meeting, she moved into Capitulation: attacking herself and treating her silence as proof that she was weak or incapable.

These apparently contradictory responses belonged to the same protective system. Overcompensation attempted to disprove the shame-based narrative. Avoidance prevented its anticipated exposure. Capitulation surrendered to it as though it were established fact. Each position offered some immediate regulation or certainty, but their repeated enactment maintained the shame-based understanding of the self.

The pendulum was expressed through the whole person. Overcompensation appeared as urgency, muscular tension, relentless preparation and vigilant monitoring of others. Avoidance appeared as restricted movement, a quieter voice, averted gaze and silence. Capitulation appeared as heaviness, reduced agency and repetitive self-attacking language. Thought, affect, attention, bodily organisation and behaviour reinforced one another.

Anna was not asked to argue her shame away or persuade herself that she was unquestionably competent. Instead, she was invited to test whether the internalised shame-based account represented the whole truth:

If the belief that I am inadequate were not allowed to make the entire decision, what would I do next?

If shame and self-doubt did not have the final say, what would I choose to do next?

These questions are consistent with Greenberger and Padesky’s use of acting as if, in which a person behaves experimentally in accordance with a more balanced alternative belief and observes the consequences (Greenberger and Padesky, 2016). Anna was not required to believe the alternative in advance; the action created an opportunity to gather information that her established shame-based belief and protective responses had previously restricted.

Asking one genuine question created a position that was neither overcompensating, avoidant nor capitulating. Anna participated without performing perfection. Her anxiety remained present, but it no longer determined the whole response.

In this application, acting as if did not require Anna to suppress her shame or convince herself that she was already confident, lovable or worthy. By enacting a valued response while shame remained active—and discovering that she could be visible, remain present and recover—Anna encountered embodied evidence that the shame-based prediction might not represent the whole truth about her. Through reflection and repetition, such experiences can gradually be incorporated into autobiographical identity and become increasingly available within the Integrated-Self.

The broader NA-CBT concept of the Integrated-Self has also been discussed in relation to NeuroAffective Narrative Reconsolidation, where experiences organised around threat and identity-disrupting meaning are revisited in the presence of regulation, agency and new autobiographical meaning (Mirea, 2026). The present article proposes a related, but not identical, process: embodied rehearsal may help the person discover that shame is an affective state accompanied by learned predictions, not an absolute description of identity.

The Pathway from Protective Pattern to Integrated-Self

The movement from a shame-organised protective pattern towards the Integrated-Self can be understood as an iterative sequence rather than a single technique. Although the stages are presented separately, therapy may move back and forth among them as experience generates new information.

1. Recognise the Pendulum movement

The Pendulum-Effect Formulation helps the person recognise how apparently different responses may be organised around the same affective threat. Attention is given not only to behaviour but also to affect, prediction, bodily organisation, attention and relational function.

The question shifts from What is wrong with me? to:

What is this response attempting to prevent, disprove or make certain?

For Anna, extensive preparation was not simply conscientiousness, silence was not simply passivity and self-attack was not simply low mood. Together, they formed a repeating attempt to manage anticipated shame. Overcompensation attempted to disprove inadequacy, avoidance prevented its anticipated exposure and capitulation treated the shame-based account as established fact.

2. Clarify an emerging value

Change requires more than moving away from anxiety or interrupting an unwanted behaviour. The person needs a direction in which they genuinely wish to move: participation, connection, curiosity, honesty, self-respect, courage or appropriate assertiveness.

A value should not become another idealised identity or perfectionistic standard. I want to relate with honesty is more workable than I must become a completely authentic person.

Anna’s emerging direction was participation. Her goal was not to appear impressive, eradicate anxiety or prove that she was competent. It was to contribute something genuine without abandoning herself. This direction provided a reason to act that did not depend upon feeling confident first.

3. Imagine the situation and its difficulties

Present-tense, multisensory imagery can evoke the anticipated situation before the person enters it (Hackmann, Bennett-Levy and Holmes, 2011; Holmes and Mathews, 2010). The image should include the Pendulum impulse, the values-consistent response, uncertain outcomes and recovery. Its purpose is to prepare for reality rather than script compulsory success.

Anna imagined entering the meeting, noticing people turning towards her and feeling the first signs of activation. She became aware of her lifted shoulders, tightened jaw, restricted breathing and urge to delay. She also noticed the familiar prediction: If I speak without complete certainty, I will expose my inadequacy.

The image was not changed into a fantasy in which Anna felt completely calm and everyone responded warmly. Instead, she imagined remaining activated while orienting towards the room, feeling the support of the chair and allowing a slower exhalation. She also imagined several possible outcomes, including interest, indifference, misunderstanding and disagreement.

Imagery made the shame-based prediction observable while creating a provisional model of how Anna might respond differently.

4. Embody and rehearse one observable response

The emerging value is translated into voice, movement, posture, attention and action. The person may rehearse a sentence, question, boundary, request, pause or other form of participation while noticing the protective impulses that arise.

Anna practised asking her question aloud. At first, her voice was quiet and apologetic. She surrounded the question with explanations intended to protect her from being wrong. Through rehearsal, she noticed these movements and experimented with saying the same words more simply.

The purpose was not to manufacture confidence or produce a flawless performance. It was to make participation behaviourally and bodily available. Regulation supported sufficient capacity for learning; it did not require Anna to become completely calm before speaking.

5. Enact it within the therapeutic relationship

Where relevant, the therapy relationship provides an immediate opportunity to practise honesty, disagreement, need, boundary or repair. The consulting room is not merely a protected place in which the person prepares for relationships elsewhere. It is itself a real relationship in which the Pendulum may become visible.

Anna noticed that she also tried to perform competence in therapy. She prepared detailed accounts, searched for the “right” insight and sometimes agreed with interpretations that did not entirely fit. She worried that disagreement would disappoint the therapist or make her appear resistant.

In imagery and rehearsal, Anna practised telling the therapist that a recent exercise had felt too structured and that she had felt less connected during it. She then expressed this in the session. She remained physiologically activated, but she did not overexplain, withdraw or surrender her experience.

The significance of this moment did not depend solely upon receiving reassurance. Anna discovered that she could express a difference and continue relating. The therapeutic relationship became a real site of embodied rehearsal, feedback and revision rather than another setting in which she had to perform correctly.

6. Test it in everyday life

Rehearsal becomes therapeutically meaningful when it is translated, where safe and appropriate, into graded action. The situation should matter enough to activate the existing prediction but remain sufficiently manageable to permit observation and recovery.

Anna’s first task was deliberately modest: to prepare one genuine question and ask it within the first ten minutes of a meeting. The task activated her fear of exposure without requiring her to dominate the discussion or deliver a flawless presentation.

When the moment arrived, Anna’s chest tightened and the familiar instruction returned: Wait until you are completely certain.

This time, she asked the question. Her anxiety remained present, but it no longer determined the whole response.

7. Reflect, adapt and repeat

The outcome is not classified simply as success or failure. The person compares what was predicted with what occurred, observes how activation changed and considers what supported presence and recovery. Difficult or ambiguous outcomes must be included rather than converted into a compulsory success narrative.

Anna’s question was answered and the meeting continued. She did not experience a sudden transformation, but neither did the humiliation she had predicted occur. Her body mobilised and then began to recover.

Anna had not proved that she would never be criticised. She had learned something more credible: she could speak without complete certainty, tolerate the activation and recover afterwards.

The response was subsequently adapted and tested in other situations. Anna expressed a preference about the direction of a project, declined an additional responsibility and practised contributing without producing an exhaustive defence. Repetition across varied contexts helped make the capacity more accessible without converting it into another rigid rule.

8. Consolidate authorship and expand authenticity

Reflection connects the action with a credible autobiographical understanding of the self. The person is invited to recognise:

A part of me anticipated shame, and I was also capable of acting according to what mattered.

Anna had not merely watched a rehearsed role ask the question. It was her body that tolerated the visibility, her voice that produced the words and her agency that remained present while doubt continued. Consolidating authorship allowed the experience to become part of her developing self-understanding without requiring her to claim permanent transformation.

Within this article, the Integrated-Self refers to an increasingly connected and flexible repertoire in which different affects, needs, values and action tendencies can be acknowledged without one protective position automatically controlling the whole response. Integration does not replace anxiety with permanent confidence or install a new idealised character. It expands what the person can recognise, tolerate, choose and enact.

Anna’s emerging understanding was therefore not:

I am always confident.

It was more credible:

I can notice the urge to prove, hide or surrender and still choose how I want to participate.

Why Action Can Precede Motivation and Confidence

People often wait not only for confidence but also for motivation. Yet motivation is not always a prerequisite for action; it can also be an outcome of action. Behavioural activation, exposure, skills rehearsal and behavioural experiments all make use of the principle that experience can generate information unavailable through reflection alone.

The mechanism is not repetition by itself. Repetition without awareness may consolidate an existing pattern. Useful rehearsal involves a meaningful prediction, tolerable activation, observable action, attention to the outcome, recovery and reflection. If the task overwhelms the person, it may reinforce the expectation that the situation is unmanageable. If it is effortless and emotionally irrelevant, little new learning may occur. Grading is therefore not a concession to weakness but part of the learning design.

Motivation may increase when the person experiences even a small degree of authorship: I did something that mattered while the old feeling was still present. This differs from waiting passively for an internal state to grant permission. It also differs from coercing action in the name of progress. The target must remain personally meaningful, collaboratively chosen and open to revision.

Bringing Embodied Rehearsal into Practice

In practice, embodied rehearsal is developed collaboratively around a personally meaningful and observable response. The therapist and client anticipate how the protective pattern may appear, rehearse the response while allowing manageable activation to remain present and, where appropriate, test it through graded action in everyday life. What was predicted is then compared with what occurred, including how the person responded, recovered and understood their own agency. The process is adapted and repeated across contexts, not to perfect a new performance, but to help a previously inhibited response become increasingly available within the Integrated-Self.

When ‘Acting as If’ Becomes Harmful

Embodied rehearsal is not universally helpful. It becomes clinically problematic when it asks a person to deny reality, conceal distress or perform beyond their capacity. Several distinctions are essential:

  • Rehearsal versus masking: rehearsal expands choice; masking demands a socially acceptable performance while hiding need, fatigue or neurodivergent difference.
  • Courage versus flooding: graded action permits activation and recovery; flooding overwhelms regulation and may reinforce danger.
  • Aspiration versus deception: practising a skill differs from claiming competence, qualifications or safety that do not exist.
  • Embodiment versus emotional invalidation: posture, breathing or voice work should not be used to tell a distressed person that their feelings are incorrect.
  • Agency versus coercion: the person chooses the target action and retains permission to pause, modify or stop.

Trauma survivors may have extensive experience of performing compliance while internally mobilised, frozen or dissociated. Inviting further performance without attending to consent, relational safety and bodily cues risks repeating the problem. Regulation is not merely a preliminary exercise before the ‘real’ intervention; it is part of the conditions under which action can remain chosen and learnable.

A Necessary Scientific Caution

The language of neuroplasticity is sometimes used as though naming it proves a specific intervention. Neuroplasticity is a general property of the nervous system, not evidence that every repeated performance produces therapeutic change. Claims about neurological ‘encoding’ require precision: which process was measured, in which population, under what conditions and with what durability?

Performed and lived experiences may overlap in perceptual, motor and affective processes, but they are not interchangeable. Context, consequences, relationships, agency and autobiographical meaning matter. Theatre, psychodrama and role rehearsal may offer bridges to new experience; real-world generalisation still requires testing, reflection and consolidation.

Moreno’s work provides an important clinical and historical foundation for embodied rehearsal, while contemporary research on embodied and grounded cognition offers a partially compatible scientific context. The traditions can be brought into productive dialogue, but Morenian concepts should not retrospectively be presented as neuroscientific discoveries. Their relationship is one of conceptual convergence and clinical compatibility, not proof that contemporary neuroscience has directly validated Morenian theory or NA-CBT.

NA-CBT therefore uses neuroscience to constrain and enrich formulation, not to decorate it. Where evidence is indirect, the language should remain conceptual and provisional.

Rehearse—Do Not Pretend

‘Fake it till you make it’ becomes clinically useful only when pretence is replaced by carefully formulated rehearsal. People do not need to counterfeit confidence or suppress authentic distress. They can practise behaviours that express an emerging value while acknowledging the body’s protective response.

The Pendulum-Effect Formulation helps identify how overcompensation, avoidance and capitulation restrict action around a shared affective threat. Embodied rehearsal then gives the person a protected opportunity to use their own voice and body differently. Graded action carries the experiment into lived experience; reflection, recovery and repetition help establish whether the response can become more available across contexts.

Anna did not become somebody else. She did not eliminate uncertainty or install a permanently confident identity. She discovered that the anxious, self-protective part of her did not have to make every decision. Speaking became less foreign, recovery became more familiar and participation became a credible part of what she could do.

From an NA-CBT perspective, the therapeutic question is therefore not, ‘How can I convincingly pretend to be someone else?’ It is:

What response needs to be practised so that it can become more available within my Integrated-Self?

References

Barsalou, L.W. (2008) ‘Grounded cognition’, Annual Review of Psychology, 59, pp. 617–645. https://doi.org/10.1146/annurev.psych.59.103006.093639

Berghs, M., Prick, A.J.C., Vissers, C. and van Hooren, S. (2022) ‘Drama therapy for children and adolescents with psychosocial problems: a systematic review on effects, means, therapeutic attitude, and supposed mechanisms of change’, Children, 9(9), 1358. https://doi.org/10.3390/children9091358

Coles, N.A., Larsen, J.T. and Lench, H.C. (2019) ‘A meta-analysis of the facial feedback literature: effects of facial feedback on emotional experience are small and variable’, Psychological Bulletin, 145(6), pp. 610–651. https://doi.org/10.1037/bul0000194

Coles, N.A. et al. (2022) ‘A multi-lab test of the facial feedback hypothesis by the Many Smiles Collaboration’, Nature Human Behaviour, 6, pp. 1731–1742. https://doi.org/10.1038/s41562-022-01458-9

Cruz, A., Sales, C.M.D., Alves, P. and Moita, G. (2018) ‘The core techniques of Morenian psychodrama: a systematic review of the literature’, Frontiers in Psychology, 9, 1263. https://doi.org/10.3389/fpsyg.2018.01263

Greenberger, D. and Padesky, C.A. (2016) Mind Over Mood: Change How You Feel by Changing the Way You Think. 2nd edn. New York: Guilford Press.

Hackmann, A., Bennett-Levy, J. and Holmes, E.A. (2011) Oxford Guide to Imagery in Cognitive Therapy. Oxford: Oxford University Press. https://doi.org/10.1093/med:psych/9780199234028.001.0001

Holmes, E.A. and Mathews, A. (2010) ‘Mental imagery in emotion and emotional disorders’, Clinical Psychology Review, 30(3), pp. 349–362. https://doi.org/10.1016/j.cpr.2010.01.001

Jiang, L., Alizadeh, F. and Cui, W. (2023) ‘Effectiveness of drama-based intervention in improving mental health and well-being: a systematic review and meta-analysis during the COVID-19 pandemic and post-pandemic period’, Healthcare, 11(6), 839. https://doi.org/10.3390/healthcare11060839

Mirea, D. (2026) ‘NeuroAffective Narrative Reconsolidation: Integrating Traumatic Memories and the Development of the Integrated-Self in NeuroAffective-CBT’, NeuroAffective-CBT Online Journal, 5 March. Available at: article webpage (Accessed: 3 September 2026)

Moreno, J.L. (1946) Psychodrama: First Volume. Beacon, NY: Beacon House.

Moreno, J.L. (1947) The Theatre of Spontaneity. Beacon, NY: Beacon House.

Moreno, J.L. (1955) ‘Theory of spontaneity-creativity’, Sociometry, 18(4), pp. 105–118. https://doi.org/10.2307/2785848

Moreno, J.L. (1961) ‘The role concept: a bridge between psychiatry and sociology’, American Journal of Psychiatry, 118(6), pp. 518–523.

Moreno, J.L. (1965) ‘Therapeutic vehicles and the concept of surplus reality’, Group Psychotherapy, 18, pp. 211–216. https://doi.org/10.12926/ek7xhv15

Niedenthal, P.M. (2007) ‘Embodying emotion’, Science, 316(5827), pp. 1002–1005. https://doi.org/10.1126/science.1136930

Salter, A. (1949) Conditioned Reflex Therapy. New York: Creative Age Press.

Vygotsky, L.S. (1999) ‘On the problem of the psychology of the actor’s creative work’, in Rieber, R.W. (ed.) The Collected Works of L. S. Vygotsky, Volume 6: Scientific Legacy. New York: Kluwer Academic/Plenum, pp. 237–244. (Original work published 1932.)

Author’s Note

This article presents a conceptual NeuroAffective-CBT formulation intended for professional discussion and psychoeducation. It does not claim that embodied rehearsal is a stand-alone treatment or that the mechanisms proposed here have been uniquely validated for NA-CBT. Interventions should be adapted to individual formulation, consent, clinical risk and professional scope of practice.

Continue reading: Developing Authenticity Through Values-Guided Behavioural Experiments explores the next stage of Anna’s clinical illustration—from embodied possibility towards values, authorship and authentic living.